How to reconstitute tirzepatide: concentration, worked examples and storage
Tirzepatide is a 39-amino-acid dual GIP and GLP-1 receptor agonist peptide (C20 fatty diacid at lysine 20) studied for glycemic control and body-weight reduction in the SURPASS and SURMOUNT trials. PrymaLab supplies lyophilized Tirzepatide 5mg, 10mg, 15mg and 20mg vials, and larger sizes to 100mg, for research use; each vial is dissolved in a suitable diluent before use.
- Sequence or size: 39 residues on a GIP backbone, two Aib substitutions, C20 fatty diacid at Lys20; about 4.8 kDa; CAS 2023788-19-2.
- Class: dual GIP and GLP-1 receptor agonist.
- Studied for: type 2 diabetes (SURPASS trials), chronic weight management (SURMOUNT trials) and diabetes prevention.
- Worked concentration example: a 10mg vial dissolved in 2 ml of diluent is 5 mg/ml.
- Trial results: mean body-weight change of 20.9% in the highest-dose arm of the 72-week SURMOUNT-1 trial.
- Storage: lyophilized vial at -20°C or 2 to 8°C, protected from light; reconstituted solution refrigerated at 2 to 8°C.
- Forms and sizes at PrymaLab: Tirzepatide 5mg, Tirzepatide 10mg, Tirzepatide 15mg, Tirzepatide 20mg and 30mg to 100mg vials.
| Vial | Diluent added | Concentration |
|---|---|---|
| 5mg vial | 1 ml | 5 mg/ml |
| 10mg vial | 2 ml | 5 mg/ml |
| 10mg vial | 1 ml | 10 mg/ml |
| 20mg vial | 2 ml | 10 mg/ml |
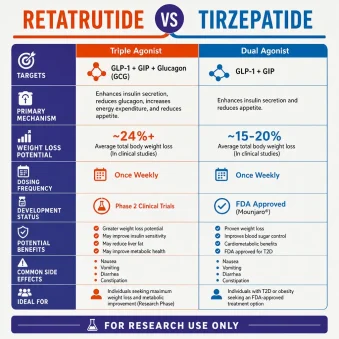
The peptide reconstitution calculator does the same arithmetic for any vial size and diluent volume; the retatrutide vs tirzepatide guide compares this molecule with the triple agonist that followed it.
Tirzepatide is a dual GIP and GLP-1 receptor agonist studied for glycemic control and weight reduction, with a mean body-weight change of 20.9% in the highest-dose arm of the 72-week SURMOUNT-1 trial. Research-grade tirzepatide ships as a lyophilized powder that is dissolved before use, so this guide works through the arithmetic of concentration (milligrams per milliliter for a given diluent volume) and how the solution is stored. It is written for research use only.
What Is Tirzepatide and How Does It Work?
Developed by Eli Lilly, tirzepatide represents a paradigm shift in body therapy because it targets two incretin hormone pathways simultaneously rather than one. Traditional GLP-1 receptor agonists like semaglutide start only the GLP-1 pathway, while tirzepatide engages both GIP and GLP-1 receptors in a mechanism researchers have termed "twincretin" therapy. The peptide is engineered with a 20-carbon fatty diacid moiety that binds to serum albumin in the bloodstream, extending its half-life to about five days. The size and fatty-acid modification of the molecule are also why gentle handling during reconstitution matters for preserving the peptide’s structural integrity [1].
The dual-receptor mechanism produces paired body effects that exceed those of either pathway alone. GLP-1 receptor start suppresses appetite through hypothalamic signaling, delays gastric emptying to promote satiety, and increases glucose-dependent insulin secretion from pancreatic beta cells. GIP receptor start enhances fat body function, improves insulin response in adipose tissue, and may add more appetite-suppressing effects through central nervous system pathways. Together, these mechanisms produce the large weight loss and glycemic gains saw across the SURPASS and SURMOUNT clinical trial programs [2,3].
Tirzepatide is marketed under two brand names: Mounjaro, which was approved by the FDA in May 2022 for improving glycemic control in adults with type 2 diabetes, and Zepbound, which got FDA approval in November 2023 for chronic weight care in adults with obesity or overweight with at least one weight-related comorbidity [5,7]. Both branded products come as pre-filled injection pens that need no mixing. Compounded and research-grade tirzepatide are supplied as a freeze-dried powder that is dissolved before use.
Why lyophilized tirzepatide is reconstituted
Compounded tirzepatide differs from brand-name Mounjaro and Zepbound in its form. The approved products are supplied as a liquid in pre-filled pens, while compounded and research-grade tirzepatide are supplied as a freeze-dried powder inside a sealed glass vial. Lyophilization, the process of freeze-drying, removes water from the peptide solution while preserving its structure and activity, and it extends the shelf life of the peptide at room temperature compared with a liquid form [1].
Reconstitution reverses lyophilization: a measured volume of a suitable sterile diluent is added to the powder, and the concentration of the resulting solution is the peptide mass divided by the volume added. Errors in the process, including using the wrong volume of diluent, shaking the vial or failing to keep the vial clean, give the wrong concentration, break down the peptide or contaminate the solution.
Essential Supplies for Tirzepatide Reconstitution
Before beginning the mixing process, gather all necessary supplies in a clean, well-lit workspace. Having everything prepared in advance minimizes the time the vial is exposed and reduces the risk of contamination. Reconstitution needs the lyophilized tirzepatide vial, a suitable sterile diluent, sterile equipment to measure and transfer the diluent, alcohol swabs for the vial stoppers and a puncture-resistant sharps container for disposal.
How to Reconstitute Tirzepatide: Step-by-Step Instructions
The following steps apply to freeze-dried tirzepatide vials. Following each step carefully gives an accurate concentration and a clean preparation.
Step 1: Prepare Your Workspace
Wash your hands thoroughly with soap and warm water for at least 20 seconds. Dry with a clean, lint-free towel. Clear a flat, stable surface and lay out all supplies. Ensure the area is free from dust, food debris, and other contaminants. If available, wear disposable nitrile gloves for an more layer of sterility.
Step 2: Sterilize the Vial Stoppers
Remove the plastic caps from both the tirzepatide vial and the sterile water vial to expose the rubber stoppers underneath. Wipe the top of each rubber stopper with a fresh alcohol swab using a firm, circular motion. Allow the alcohol to air-dry completely, which takes about 15 to 30 seconds. Do not blow on the stoppers or touch them after cleaning.
Step 3: Measure the diluent
Measure the planned volume of diluent with sterile equipment. The volume sets the final concentration of the reconstituted tirzepatide: adding 1 mL to a 10 mg vial gives 10 mg/mL, while adding 2 mL gives 5 mg/mL.
Step 4: Add the diluent to the vial
Add the diluent through the center of the tirzepatide vial’s rubber stopper, directed toward the inside wall of the vial rather than directly at the powder cake. Release it slowly down the glass wall so that it flows gently onto the powder, which helps prevent foaming and peptide breakdown.
Step 5: Mix Gently by Swirling
Once all the diluent has been added, pick up the vial and gently swirl it in slow, circular motions for 30 to 60 seconds. Do not shake the vial. Vigorous agitation can denature the peptide, breaking its cell-level structure and reducing its natural activity. If any undissolved powder remains after swirling, set the vial on a flat surface and wait two to three minutes, then swirl gently again. The solution should be completely clear and free of visible particles before use.
Step 6: Label and Store
Once the powder is fully dissolved, write the date of mixing on the vial with a permanent marker. Store the solution in the refrigerator at 2 to 8°C straight away and use it within 28 to 30 days.
Understanding Tirzepatide Concentration After Mixing
The concentration of reconstituted tirzepatide is expressed in milligrams per milliliter (mg/mL). It is calculated by dividing the total milligrams of tirzepatide in the vial by the total milliliters of diluent added.
| Vial Size | Diluent Added | Resulting Level |
|---|---|---|
| 5 mg | 1 mL | 5 mg/mL |
| 10 mg | 1 mL | 10 mg/mL |
| 10 mg | 2 mL | 5 mg/mL |
| 30 mg | 1.5 mL | 20 mg/mL |
| 30 mg | 3 mL | 10 mg/mL |
| 60 mg | 3 mL | 20 mg/mL |
| 60 mg | 6 mL | 10 mg/mL |
Tirzepatide Storage Guidelines Before and After Reconstitution
Proper tirzepatide storage is key for keeping peptide shelf life and keeping the peptide at full potency. Storage requirements differ greatly depending on whether the tirzepatide is in its unreconstituted powder form or has already been mixed into solution.
| Storage Condition | Before Mixing | After Mixing |
|---|---|---|
| Heat | Room heat 68–77°F (20–25°C) or refrigerated | Refrigerate at 36–46°F (2–8°C) |
| Shelf life | Per manufacturer label (often 12–24 months) | 28–30 days from mixing date |
| Freezing | Avoid freezing | Never freeze mixed solution |
| Light exposure | Store in original packaging away from light | Protect from direct sunlight; keep in refrigerator |
| Container | Keep in sealed sterile vial | Keep in original vial with stopper intact |
After mixing, the 28-to-30-day tirzepatide storage window begins regardless of how much solution remains in the vial. Even if solution remains, it is discarded after this period because the preservative in sterile water has a limited duration of antimicrobial effectiveness. Using tirzepatide beyond this window increases the risk of bacterial contamination and peptide breakdown, both of which can compromise safety and effect.
What Are the Side Effects of Tirzepatide?
Tirzepatide’s side effect profile has been extensively characterized across multiple clinical trials involving thousands of participants. Most adverse effects were gastrointestinal, more frequent at higher doses and most pronounced early in treatment; in the trials, these side effects diminished over several weeks [2,3,9].
Common Side Effects
| Side Effect | Frequency Range | Clinical Notes |
|---|---|---|
| Nausea | 12–33% | Most common; peaked during dose increases in the trials |
| Diarrhea | 12–21% | Usually mild to moderate |
| Vomiting | 5–13% | More common at higher doses |
| Constipation | 5–11% | Related to slowed gastric emptying |
| Abdominal pain | 5–8% | May accompany nausea; often transient during escalation |
| Dyspepsia | 3–8% | Indigestion and bloating |
| Administration-site reactions | 2–5% | Redness, itching or swelling where the drug was given |
| Hair loss (alopecia) | 3–6% | Linked with rapid weight loss rather than the drug itself |
| Fatigue | 2–4% | Usually transient in the trials |
Serious Side Effects (Rare)
Tirzepatide carries an FDA Boxed Warning for the risk of thyroid C-cell tumors based on findings in rodent studies, although this risk has not been confirmed in humans. More rare but serious adverse effects include acute pancreatitis, acute gallbladder disease including cholecystitis and cholelithiasis, acute kidney injury second to dehydration from severe gut effects, and serious hypersensitivity reactions. The label also lists diabetic retinopathy complications in patients with type 2 diabetes, and suicidal ideation remains under study [9].
Clinical Evidence: How Effective Is Tirzepatide?
The clinical evidence supporting tirzepatide’s effect is among the most robust in the history of body pharmacotherapy. Two major clinical trial programs, SURPASS for type 2 diabetes and SURMOUNT for obesity, have created full data across thousands of participants in randomized controlled trials published in the New England Journal of Medicine [2,3,4].
SURMOUNT-1: Weight Loss in Adults Without Diabetes
The landmark SURMOUNT-1 trial enrolled 2,539 adults with obesity or overweight and at least one weight-related comorbidity but without diabetes. Participants were randomized to one of three tirzepatide doses or placebo for 72 weeks in addition to lifestyle intervention. In the highest-dose arm, mean weight reduction was 20.9% of body weight, about 48 pounds on average, against 3.1% in the placebo group; in the middle and lowest arms, mean weight loss was 19.5% and 15.0%. In the highest-dose arm, 56.7% of participants lost 20% or more of their body weight [2].
Three-year follow-up data from SURMOUNT-1 showed that weight loss was largely sustained through 176 weeks, with a 19.7% reduction in body weight in the highest-dose group. Among participants with prediabetes at baseline, progression to type 2 diabetes was up to 93% lower than with placebo [4].
SURPASS-2: Tirzepatide vs Semaglutide in Type 2 Diabetes
The SURPASS-2 trial directly compared three doses of tirzepatide with semaglutide in 1,878 adults with type 2 diabetes on metformin over 40 weeks. Tirzepatide showed superiority at all three doses. In the highest-dose arm, HbA1c fell by 2.30% against 1.86% with semaglutide, and body weight fell by 11.2 kg against 5.7 kg with semaglutide (weight loss) [3].
Tirzepatide vs Semaglutide: How Do They Compare?
The comparison between tirzepatide and semaglutide represents one of the most clinically important questions in contemporary body medicine, as both drugs dominate the GLP-1 and incretin therapy space. Their basic difference lies in mechanism: tirzepatide starts both GIP and GLP-1 receptors while semaglutide starts GLP-1 receptors alone. This dual-receptor approach appears to confer superior effect for both weight loss and glycemic control across clinical trial data.
| Feature | Tirzepatide (Mounjaro/Zepbound) | Semaglutide (Ozempic/Wegovy) |
|---|---|---|
| Mechanism | Dual GIP + GLP-1 receptor agonist | Selective GLP-1 receptor agonist |
| FDA approval (T2DM) | Mounjaro — May 2022 | Ozempic — December 2017 |
| FDA approval (obesity) | Zepbound — November 2023 | Wegovy — June 2021 |
| Max weight loss (trials) | ~20.9% (SURMOUNT-1, 72 wk) | ~15.2% (STEP-1, 68 wk) |
| HbA1c reduction | Up to −2.30% (SURPASS-2) | Up to −1.86% (SURPASS-2) |
| Half-life | ~5 days | ~7 days |
| Common side effects | Nausea, diarrhea, vomiting (GI) | Nausea, diarrhea, vomiting (GI) |
| Head-to-head winner | Superior in SURPASS-2 and SURMOUNT-5 | Compared as active control |
In May 2025, the SURMOUNT-5 trial results published in the New England Journal of Medicine reported greater weight loss with tirzepatide than with semaglutide (Wegovy) in a direct head-to-head comparison among adults with obesity. Both drugs produced weight loss well beyond older pharmacotherapy options in the trials. Semaglutide has a longer track record and more extensive heart outcome data [3,8].
Compounded Tirzepatide vs Mounjaro and Zepbound
The distinction between compounded tirzepatide and FDA-approved brand-name products has become more important as the regulatory landscape has shifted since 2024. The two differ in quality oversight, cost and legal status.
| Factor | Compounded Tirzepatide | Mounjaro / Zepbound (Brand) |
|---|---|---|
| FDA approval | Not FDA-approved | FDA-approved (Mounjaro 2022, Zepbound 2023) |
| Form | Freeze-dried powder needing mixing | Pre-filled injection pen (ready to use) |
| Quality oversight | State pharmacy board control | FDA cGMP manufacturing standards |
| Batch testing | Varies by pharmacy | Every batch tested per FDA requirements |
| Mixing needed | Yes | No |
| Cost (typical) | Lower without insurance ($150–500/month) | Higher ($1,000+/month without insurance) |
| Insurance coverage | Rarely covered | Covered by many commercial plans |
Brand-name Mounjaro and Zepbound undergo rigorous FDA review for safety, effect, and manufacturing quality under current Good Manufacturing Practices (cGMP). Compounded tirzepatide does not undergo this review process. While many compounding pharmacies keep high quality standards, the FDA has warned about substandard compounded GLP-1 products, and the lack of batch-level control oversight means that potency, purity, and sterility can vary between pharmacies and even between batches from the same pharmacy. [6]
The cost differential between compounded and brand-name tirzepatide is often the main reason compounded forms are used. Without insurance coverage, branded Mounjaro or Zepbound can exceed one thousand dollars per month, while compounded tirzepatide often ranges from one hundred fifty to five hundred dollars per month depending on the pharmacy, dosage, and geographic location. Compounded products also need reconstitution and proper storage.
FDA Regulatory Status and Legal Considerations
The control status of compounded tirzepatide has undergone dramatic changes that directly impact patient access. Tirzepatide injection was placed on the FDA drug shortage list in 2022 due to overwhelming demand that exceeded Eli Lilly’s manufacturing capacity. During this shortage period, compounding pharmacies were permitted under sections 503A and 503B of the Federal Food, Drug, and Cosmetic Act to compound tirzepatide as a copy of the commercially unavailable product, creating a huge compounding market [6].
On October 2, 2024, the FDA declared the tirzepatide shortage resolved, meaning Lilly’s production capacity could meet national demand. This declaration triggered legal restrictions on compounding: under 503A, pharmacies cannot regularly compound drugs that are mainly copies of commercially available products, and under 503B, outsourcing facilities cannot compound tirzepatide unless it appears on the 503B bulks list or the shortage list. As of April 2026, tirzepatide appears on neither list [6].
The Outsourcing Facilities Association challenged the FDA’s shortage resolution in federal court, but the court denied the preliminary injunction in March 2025, and FDA enforcement timelines for 503A pharmacies have expired. The practical result is that compounding pharmacies face major legal restrictions on producing tirzepatide that is mainly identical to Mounjaro or Zepbound. Some pharmacies have tried to differentiate their products by combining tirzepatide with more ingredients such as vitamin B6, B12, or glycine, arguing these mix products are not "mainly copies" of the FDA-approved drug. The legality of this approach remains an evolving area of FDA enforcement.
Common Reconstitution Mistakes and How to Avoid Them
Errors during reconstitution change the concentration or damage the peptide. The following table lists the most common mistakes and the correct approach for each.
| Common Mistake | Why It Matters | Correct Approach |
|---|---|---|
| Shaking the vial vigorously | Denatures the peptide structure, reducing potency | Gently swirl in slow circular motions for 30–60 seconds |
| Using the wrong volume of diluent | Creates the wrong concentration | Measure the planned volume; double-check before adding it to the vial |
| Adding diluent directly onto powder | Causes too much foaming and possible peptide damage | Let the diluent run slowly down the vial wall |
| Not sterilizing rubber stoppers | Introduces bacteria into the sterile vial | Wipe both stoppers with alcohol swabs; allow to air-dry |
| Failing to label the vial with date | Cannot track the 28–30 day storage window | Write mixing date on vial immediately after mixing |
| Storing at room heat after mixing | Accelerates peptide breakdown and bacterial growth | Refrigerate immediately at 36–46°F (2–8°C) |
Rushing is a common source of error. Setting aside a quiet, well-lit space and allowing five to ten minutes for the complete process, from hand-washing through labeling, reduces mistakes.
What the tirzepatide trials measured
The SURPASS program measured glycemic control in type 2 diabetes and the SURMOUNT program measured body weight in obesity, each comparing three tirzepatide dose arms with placebo or an active comparator. The table lists what the main trials measured and reported. Drug labels for Mounjaro and Zepbound set out the approved use of those products; they describe the approved drugs, not research vials.
| Trial | Participants | Design | Reported result |
|---|---|---|---|
| SURMOUNT-1 (Jastreboff and colleagues, NEJM 2022) | 2,539 adults with obesity or overweight, without diabetes | Three tirzepatide dose arms versus placebo; 72 weeks | Mean weight change of 15.0%, 19.5% and 20.9% from the lowest to the highest arm versus 3.1% on placebo |
| SURPASS-2 (Frías and colleagues, NEJM 2021) | 1,879 adults with type 2 diabetes on metformin | Three tirzepatide dose arms versus semaglutide; 40 weeks | HbA1c fell by 2.01, 2.24 and 2.30 percentage points versus 1.86 for semaglutide; body weight fell 7.6, 9.3 and 11.2 kg versus 5.7 kg |
| SURMOUNT-1 three-year extension (Jastreboff and colleagues, NEJM 2025) | 1,032 of the SURMOUNT-1 participants who had prediabetes at baseline | Same three arms; 176 weeks | Type 2 diabetes was diagnosed in 1.3% on tirzepatide against 13.3% on placebo (hazard ratio 0.07); mean weight change of 12.3%, 18.7% and 19.7% versus 1.3% on placebo |
PrymaLab supplies Tirzepatide 5mg vial, Tirzepatide 10mg vial, Tirzepatide 15mg vial and Tirzepatide 20mg vial sizes for laboratory research only, and the retatrutide vs tirzepatide guide covers the triple agonist that followed tirzepatide into phase 3.
Frequently Asked Questions About Tirzepatide Reconstitution
How do you reconstitute tirzepatide?
A measured volume of a suitable sterile diluent is added slowly down the inside wall of the lyophilized vial, then the vial is swirled gently until the powder dissolves; shaking can denature the peptide. A 10 mg vial in 2 ml gives 5 mg/ml. The solution is labeled with the concentration and date and refrigerated at 2 to 8°C, protected from light.
How much diluent goes into a 10 mg tirzepatide vial?
It depends on the concentration wanted. Two milliliters in a 10 mg vial gives 5 mg/ml, and one milliliter gives 10 mg/ml.
What did the tirzepatide trials measure?
The SURPASS trials measured glycemic control in type 2 diabetes and the SURMOUNT trials measured body weight in obesity, each with three tirzepatide dose arms. In SURMOUNT-1, mean weight changes over 72 weeks were 15.0%, 19.5% and 20.9% across the three arms against 3.1% on placebo. These describe trial conditions, not a protocol for research material.
How is reconstituted tirzepatide stored?
Once mixed, the solution is kept refrigerated at 2 to 8°C, protected from light and never frozen, since freezing can aggregate the peptide. Unopened lyophilized powder keeps longer frozen. Any solution that turns cloudy or discolored is discarded.
Q: How much sterile water do I add to tirzepatide?
A: The amount depends on the concentration wanted. For a 10 mg vial, adding 1 mL creates a 10 mg/mL solution, adding 2 mL creates 5 mg/mL, and adding 0.5 mL creates 20 mg/mL.
Q: Can I shake the tirzepatide vial after adding water?
A: No, you should never shake a tirzepatide vial. Vigorous shaking can damage the peptide structure and reduce its effectiveness. Instead, gently swirl the vial in a circular motion until the powder fully dissolves into a clear solution.
Q: How long does mixed tirzepatide last?
A: Mixed compounded tirzepatide often remains stable for 28 to 30 days when stored properly in a refrigerator at 36 to 46 degrees Fahrenheit (2 to 8 degrees Celsius). Never freeze mixed tirzepatide, and discard it after 30 days or if the solution appears cloudy or discolored.
Q: What is the difference between compounded tirzepatide and Mounjaro?
A: Mounjaro is an FDA-approved brand-name product manufactured by Eli Lilly that comes in pre-filled injection pens needing no mixing. Compounded tirzepatide is prepared by compounding pharmacies, often as a freeze-dried powder that needs reconstitution before use. Compounded versions are not FDA-approved and do not undergo the same control review for safety and effect.
Q: Is compounded tirzepatide legal?
A: The legal status of compounded tirzepatide has changed greatly. The FDA declared the tirzepatide shortage resolved in December 2024, and as of 2025, compounding pharmacies face restrictions on producing tirzepatide that is mainly a copy of commercially available Mounjaro or Zepbound.
Key Takeaways
Reconstituting lyophilized tirzepatide rests on three points: gentle, clean technique when the diluent is added; the concentration, which is the peptide mass divided by the volume of diluent; and refrigerated storage of the solution at 2 to 8°C for no more than 28 to 30 days.
In the SURMOUNT-1 trial, mean body weight fell by up to 20.9% (weight loss), and the legal status of compounded tirzepatide continues to shift.
References and Clinical Sources
- Min T, Bain SC. The Role of Tirzepatide, Dual GIP and GLP-1 Receptor Agonist, in the Care of Type 2 Diabetes: The SURPASS Clinical Trials. Diabetes Ther. 2021;12(1):199–214. doi:10.1007/s13300-020-00981-0
- Jastreboff AM, Aronne LJ, Ahmed NN, et al. Tirzepatide Once Weekly for the Treatment of Obesity. N Engl J Med. 2022;387(3):205–216. doi:10.1056/NEJMoa2206038
- Frías JP, Davies MJ, Rosenstock J, et al. Tirzepatide versus Semaglutide Once Weekly in Patients with Type 2 Diabetes. N Engl J Med. 2021;385(6):503–515. doi:10.1056/NEJMoa2107519
- Jastreboff AM, le Roux CW, Stefanski A, et al. Tirzepatide for Obesity Treatment and Diabetes Prevention. N Engl J Med. 2024. doi:10.1056/NEJMoa2410819
- U.S. Food and Drug Use. FDA Approves New Medication for Chronic Weight Care. November 8, 2023. fda.gov
- U.S. Food and Drug Use. FDA Clarifies Policies for Compounders as National GLP-1 Supply Begins to Stabilize. Updated April 1, 2026. fda.gov
- Eli Lilly and Company. FDA Approves Lilly’s Mounjaro (tirzepatide) Injection for the Treatment of Adults with Type 2 Diabetes. May 13, 2022. investor.lilly.com
- Drugs.com. Zepbound (tirzepatide) FDA Approval History. Accessed 2025. drugs.com
- Zepbound (tirzepatide) Prescribing Data. Eli Lilly and Company. 2023. accessdata.fda.gov
- Eli Lilly and Company. FDA Approves Zepbound (tirzepatide) for Chronic Weight Care. November 2023. investor.lilly.com
- American College of Cardiology. SURMOUNT-1: Tirzepatide Once Weekly for the Treatment of Obesity. Updated December 2024. acc.org
- American College of Cardiology. SURPASS-2: Tirzepatide versus Semaglutide in Patients with Type 2 Diabetes. 2021. acc.org
Formats stocked for the compounds in this article
Tirzepatide: Tirzepatide 40mg, Tirzepatide 50mg, Tirzepatide 60mg, Tirzepatide 80mg and Tirzepatide 100mg. Every listing is supplied for laboratory research use with a batch certificate of analysis.