Peptides for weight loss: which ones have human trial evidence, which were tested and failed, and which have never been given to a person
"Peptides for weight loss" covers two different things that get sold under one phrase. The first is the incretin class: semaglutide, tirzepatide and liraglutide, which are FDA-approved for chronic weight management on the strength of multi-thousand-patient randomised trials, and the next generation behind them (retatrutide, survodutide, CagriSema, mazdutide) with completed phase 3 weight-loss trials. In the phase 3 trials these produced placebo-adjusted weight loss of about 5 to 21 percentage points, with gastrointestinal side effects in most participants and substantial regain after stopping. The second is a long tail of compounds marketed as "fat loss peptides" that either failed their trials (AOD-9604 missed its powered endpoint in 502 patients and development was terminated in 2007; CJC-1295's phase 2 was stopped after a death), were tested for something else (tesamorelin reduces visceral fat in HIV lipodystrophy and its own label calls it weight-neutral), or have never been given to a human being for any weight endpoint at all (ipamorelin, GHRP-2, GHRP-6, hexarelin, MOTS-c, 5-amino-1MQ, lipotropic injections). This article grades every one of them by what the human record contains. It carries no dosing protocol, and PrymaLab supplies several of the compounds mentioned here for laboratory research only.
- Approved for chronic weight management in general obesity (US, October 2026): liraglutide (Saxenda, 2014), semaglutide 2.4 mg (Wegovy, 2021) and 7.2 mg (March 2026), oral semaglutide 25 mg (December 2025), tirzepatide (Zepbound, 2023), and the non-peptide orforglipron (Foundayo, April 2026). Nothing else for general obesity; the peptide setmelanotide (Imcivree, 2020) is approved only for obesity caused by specific genetic deficiencies, Bardet-Biedl syndrome or hypothalamic injury.
- Phase 3 weight-loss trials complete, not approved in the US or EU: retatrutide (US filing planned Q1 2027), survodutide (no filing date announced), CagriSema (NDA filed December 2025, decision pending), mazdutide (approved in China only, June 2025).
- Phase 3 placebo-adjusted results: STEP 1 semaglutide −12.4 points at 68 weeks; SURMOUNT-1 tirzepatide (highest dose) −17.8 points at 72 weeks; TRIUMPH-1 retatrutide (highest dose) −21.0 points at 80 weeks; REDEFINE 1 CagriSema −17.3 points at 68 weeks; SYNCHRONIZE-1 survodutide (higher dose) −7.6 points at 76 weeks; GLORY-2 mazdutide −15.2 points at 60 weeks; SCALE liraglutide −5.6 kg at 56 weeks.
- Regain: one year after stopping semaglutide, participants had regained two-thirds of what they lost (STEP 1 extension). After switching tirzepatide to placebo, +14.0% in a year (SURMOUNT-4). Pooled across agents, about 7% of body weight comes back.
- Tested and failed: AOD-9604, the hGH fragment analogue with the largest weight-loss trial programme of any "fat loss peptide" outside the incretin class, missed its primary endpoint in its 502-patient phase 2b trial, the largest it ever ran; its sponsor terminated obesity development on 21 February 2007; an FDA advisory committee voted 0 to 12 against it in December 2024.
- Never tested for weight in humans: ipamorelin (its one published trial, in post-surgical ileus, missed its endpoint; a second 320-patient ileus trial finished in 2014 and was never reported), GHRP-2 (which increased food intake by 35.9% in the one human feeding study), GHRP-6, hexarelin, MOTS-c (FDA briefing document, July 2026 meeting: no human exposure data by any route), 5-amino-1MQ (a small molecule, not a peptide, with zero registered human studies), and lipotropic "Lipo-C" injections (no controlled trial found).
| Evidence tier | What is in it | Key human weight trial | Status |
|---|---|---|---|
| 1. Approved, multiple phase 3 trials, cardiovascular outcome data | Semaglutide, tirzepatide, liraglutide | STEP 1, 1,961 (semaglutide; plus SELECT, 17,604, for cardiovascular outcomes); SURMOUNT-1, 2,539 (tirzepatide); SCALE, 3,731 (liraglutide) | FDA and EMA approved for chronic weight management |
| 2. Phase 3 weight-loss trial complete, not approved in US or EU | Retatrutide, survodutide, CagriSema, mazdutide | TRIUMPH-1, 2,339; SYNCHRONIZE-1, 725; REDEFINE 1, 3,417; GLORY-2, 461 | Investigational (mazdutide approved in China) |
| 3. Phase 2 only | Cagrilintide alone, maridebart cafraglutide, amycretin, eloralintide | Cagrilintide phase 2, 706; MariTide phase 2, 592 | Investigational; phase 3 programmes running |
| 4. Tested for weight and failed, or stopped | AOD-9604, CJC-1295 DAC | METAOD006, 502 randomised, endpoint missed; ConjuChem phase 2 terminated after a death | No approval anywhere; FDA 503A committee votes of 0 to 12 and 0 to 13 against |
| 5. Approved for something else, weight-neutral | Tesamorelin | Two phase 3 trials, 806 patients with HIV lipodystrophy, endpoint visceral fat | FDA approved for HIV lipodystrophy; label states a weight-neutral effect |
| 6. No human weight data at all | Ipamorelin, GHRP-2, GHRP-6, hexarelin, sermorelin, MOTS-c, hGH 176-191, 5-amino-1MQ, lipotropic injections | None | Unapproved; most prohibited in sport under WADA S2 |
See the semaglutide reference, the tirzepatide reference, the retatrutide reference and the dual and triple agonist comparison for the compound-level detail, the AOD-9604 reference for the failed programme, the cagrilintide reference for the amylin arm, and the purity testing guide for what an identity test can establish on material that is not the approved drug.
Also known as: weight loss peptides, fat loss peptides, peptides for fat loss, fat burning peptides, GLP-1 peptides, incretin peptides, GLP-1 receptor agonists, GIP/GLP-1 dual agonists, GLP-1/glucagon dual agonists, triple agonists, amylin analogues. The incretin drugs are semaglutide (Wegovy, Ozempic, Rybelsus), tirzepatide (Zepbound, Mounjaro), liraglutide (Saxenda, Victoza), retatrutide (LY3437943), survodutide (BI 456906) and mazdutide (IBI362); the amylin analogues are cagrilintide and the cagrilintide half of CagriSema. The non-incretin compounds are AOD-9604 (a 16-residue hGH 177-191 analogue, not hGH fragment 176-191), tesamorelin (Egrifta), CJC-1295, ipamorelin, sermorelin, GHRP-2, GHRP-6, hexarelin, MOTS-c, and 5-amino-1MQ and tesofensine, which are not peptides.
The version of this page that stood here from March 2026 was called "Top 5 fat loss peptides that actually work". It ranked on page six, got one click in three months out of five thousand impressions, and I understand why: it read like every other page for the same search. Five categories, mechanisms for each, a comparison table with no numbers in it, and a line about dosing protocols in the excerpt. I wrote it, and it was not good enough. This version starts from a different question: which of these has ever been given to a person in a trial with a weight endpoint, and what happened? Asked that way, the list sorts itself. Three compounds have general-obesity approvals and tens of thousands of trial participants between them. Four more have finished phase 3. One failed a 502-patient trial nearly twenty years ago and is still sold on the strength of a paper that reports no efficacy data. And most of the rest, including several I sell, have never been tested for weight in a human at all. The numbers are below, with the trials they came from.
Research-use-only disclaimer: This article is an evidence review of published clinical trials of pharmaceutical products conducted under medical supervision, and of the absence of such trials for other compounds. PrymaLab supplies research-grade peptides for laboratory use only; they are not Wegovy, Zepbound, Saxenda or any other approved drug, and nothing here describes or supports any use of them in people. Where trial doses appear, they are reported as study-design facts in the way a methods section reports them. This version removes the dosing language the earlier version of this page carried. Nothing here is medical advice, and nothing here is a reason to start, stop or change any medicine.

TL;DR
Three peptides are approved for weight management in general obesity and backed by phase 3 trials: semaglutide (−14.9% vs −2.4% at 68 weeks in STEP 1), tirzepatide (−20.9% vs −3.1% at 72 weeks in SURMOUNT-1) and liraglutide (−8.4 vs −2.8 kg at 56 weeks in SCALE). Four more have finished phase 3 without US approval: retatrutide (−25.0% vs −3.9% at 80 weeks), CagriSema (−20.4% vs −3.0%), mazdutide (−16.7% vs −1.5%, approved in China) and survodutide (−13.0% vs −5.4%). All of them cause gastrointestinal events in most participants, and most of the weight comes back within a year of stopping. Outside that class the record collapses: AOD-9604 failed its 502-patient trial in 2007, CJC-1295's phase 2 ended with a death, tesamorelin is approved only for HIV lipodystrophy and is weight-neutral by its own label, and ipamorelin, GHRP-2, GHRP-6, hexarelin, MOTS-c, 5-amino-1MQ and Lipo-C have no human weight trial of any kind. FDA has told sellers that "research use only" labels do not change what these products are. Research use only.
Approved: semaglutide, tirzepatide, liraglutide (peptides) and orforglipron (a small molecule) are FDA-approved for chronic weight management in general obesity; setmelanotide is approved only for rare genetic and hypothalamic forms. Retatrutide, survodutide, CagriSema, mazdutide, cagrilintide, amycretin and MariTide are not approved in the US or EU as of October 2026.
Effect sizes: placebo-adjusted loss in the phase 3 trials runs from 5.6 kg (liraglutide, 56 weeks) through 12.4 points (semaglutide, 68 weeks) and 17.8 points (tirzepatide, highest dose, 72 weeks) to 21.0 points (retatrutide, highest dose, 80 weeks). Head to head, tirzepatide beat semaglutide by 6.5 points (SURMOUNT-5) and semaglutide beat liraglutide by 9.4 points (STEP 8).
Regain: two-thirds of the loss returned within a year of stopping semaglutide; +14.0% within a year of switching tirzepatide to placebo; pooled regain about 7% of body weight.
Lean mass: about 25% of the weight lost on tirzepatide was lean mass in the SURMOUNT-1 DXA substudy, the same proportion as placebo; a 2026 systematic review found no trial measured physical function.
Failed: AOD-9604's 502-patient trial missed its endpoint and the sponsor terminated development in 2007. CJC-1295 DAC's phase 2 was terminated after a fatal myocardial infarction and never published. Ipamorelin's only published trial was in post-operative ileus and missed; a second ileus trial was never reported.
Never tested for weight in humans: GHRP-2, GHRP-6, hexarelin, MOTS-c, 5-amino-1MQ, hGH 176-191, Lipo-C. Tesamorelin reduced visceral fat without changing weight; MK-677 raised lean mass and weight without changing fat.
Regulatory: FDA warning letters of December 2024, March 2026 and August 2026 state that "research use only" labelling does not change the status of GLP-1 products sold with weight-loss claims. No GLP-1 drug is on the WADA 2026 or 2027 Prohibited Lists; every GH-axis peptide above is prohibited at all times.
Status: research use only.
What are fat loss peptides, and why does the phrase cover two different things?
A "fat loss peptide" is any short chain of amino acids sold with a weight-loss claim. The phrase lumps together approved drugs with the largest trial programmes in modern pharmacology and research compounds with no human data at all, because both are peptides and both are sold online. The word "peptide" tells you about the chemistry. It tells you nothing about the evidence.
Semaglutide is a 31-residue analogue of the gut hormone GLP-1, and it has been given to tens of thousands of people in randomised trials, including 17,604 in a single cardiovascular outcomes study.[1] AOD-9604 is a 16-residue analogue of the C-terminal fragment of human growth hormone, and the only peer-reviewed human publication about it reports safety and tolerability with no weight-loss results.[2] MOTS-c is a 16-residue peptide encoded in mitochondrial DNA, and in its briefing document for a July 2026 advisory committee meeting the FDA could identify no "clinical studies or human exposure data for MOTS-c via any route of administration".[3] All three are peptides. All three appear on lists of "best peptides for weight loss". One of them has an answer to the question of whether it works.
So this article sorts by evidence rather than by chemistry. Tier 1 is drugs approved for general obesity with multiple phase 3 trials and cardiovascular outcome data. Tier 2 is completed phase 3 weight-loss trials without US or EU approval. Tier 3 is phase 2 only. Tier 4 is compounds that were tested for weight and failed, or whose programmes were stopped. Tier 5 is compounds approved for something else and shown not to reduce weight. Tier 6 is compounds that have never been given to a person with a weight or fat-mass endpoint. The last tier is the longest, and it contains most of what is sold under this phrase.
How do peptides for weight loss work?
The compounds with evidence work on the gut-brain hormones that regulate appetite: GLP-1, GIP, glucagon and amylin. They slow gastric emptying and reduce food intake, and in trials people eat less and lose weight. The compounds without evidence are mostly claimed to work on growth hormone or mitochondrial pathways, and the claim has not been tested against a scale.
GLP-1 receptor agonists (liraglutide, semaglutide) mimic the incretin hormone released after meals; GIP/GLP-1 dual agonists (tirzepatide) add the second incretin receptor; GLP-1/glucagon dual agonists (survodutide, mazdutide) add a receptor that raises energy expenditure and liver fat oxidation; the triple agonist retatrutide hits all three; and amylin analogues (cagrilintide, the cagrilintide half of CagriSema) act on a separate satiety hormone from the pancreas.[4][5][6][7][8] The mechanism is not the point of this article, because mechanism is where most "fat loss peptide" marketing lives and it is the part that cannot be checked by a reader. What can be checked is the trial. A compound with a plausible mechanism and no trial is a hypothesis. GHRP-2 has a plausible mechanism for fat loss through growth hormone release, and when seven lean men were infused with it before a buffet, they ate 35.9% more.[9]
The growth-hormone-axis story deserves one more sentence because it carries most of the non-incretin market. The idea is that raising GH or IGF-1 shifts the body toward fat oxidation. The one well-designed body-composition trial of a GH secretagogue, the oral non-peptide MK-677 given to 65 older adults in a two-year trial with one-year primary endpoints, increased fat-free mass by 1.1 kg and found that "no significant differences were observed in abdominal visceral fat or total fat mass", with body weight up 2.7 kg against 0.8 kg on placebo and increased appetite as the commonest side effect.[10] That is the best human result the GH-secretagogue mechanism has produced, and it is a weight gain.
Which peptides have the strongest human evidence for weight loss?
Tirzepatide, semaglutide and liraglutide, in that order of effect size, are the only peptides with approvals, multiple phase 3 trials and cardiovascular outcome trials. Retatrutide, CagriSema, mazdutide and survodutide have completed phase 3 with large effects but no US or EU approval. Everything else sold as a fat-loss peptide is phase 2 at best, and most of it has no human weight data.
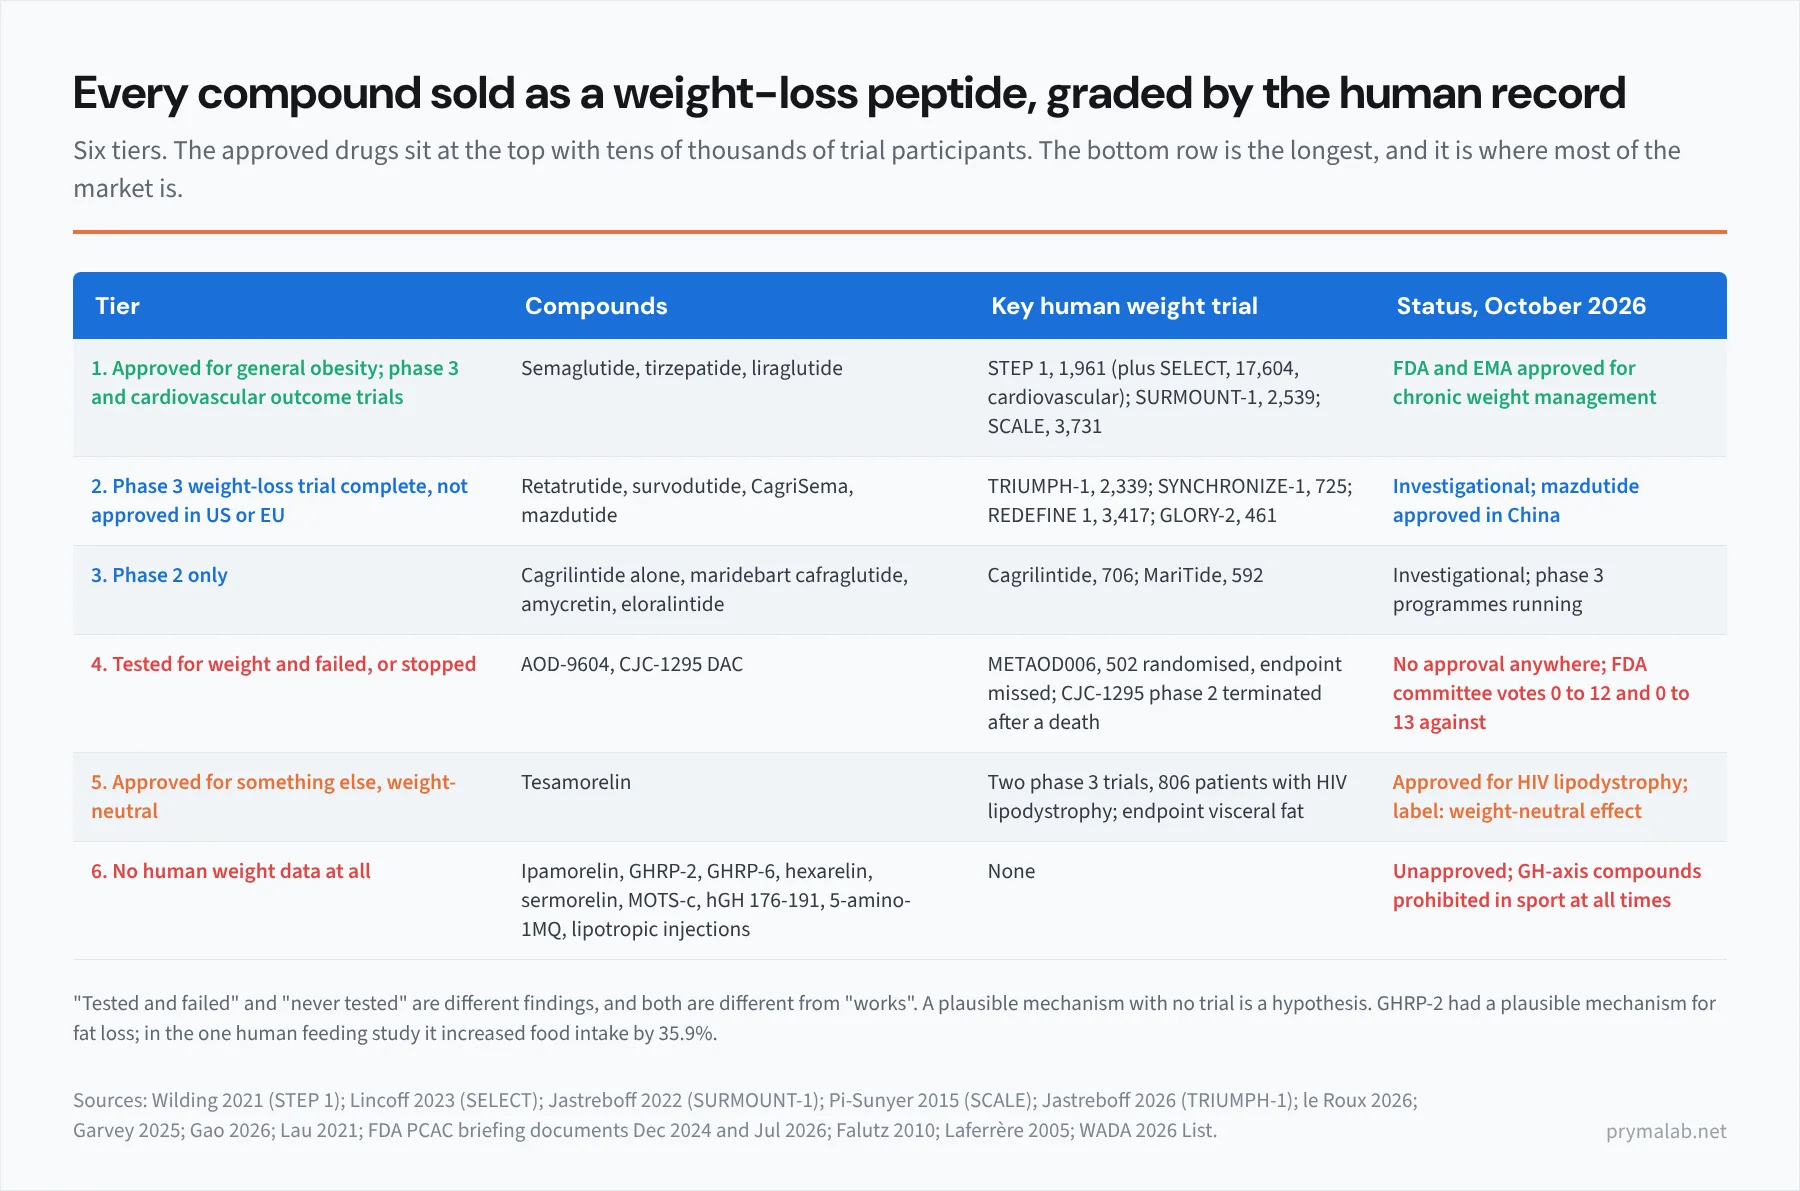
Tier 1. Semaglutide: STEP 1 randomised 1,961 adults without diabetes two-to-one against placebo for 68 weeks and found −14.9% against −2.4%, a treatment difference of −12.4 percentage points, with 50.5% of semaglutide participants losing at least 15% of their weight against 4.9% on placebo.[4] SELECT then randomised 17,604 people with cardiovascular disease and overweight, without diabetes, and found a 20% relative reduction in major adverse cardiovascular events (6.5% against 8.0%, hazard ratio 0.80).[1] Tirzepatide: SURMOUNT-1 randomised 2,539 adults across three doses and placebo for 72 weeks and found −15.0%, −19.5% and −20.9% in the three dose arms against −3.1%, with 57% of the highest-dose group losing at least 20%.[5] Liraglutide: SCALE randomised 3,731 adults for 56 weeks and found −8.4 against −2.8 kg, a difference of 5.6 kg, with 63.2% against 27.1% losing at least 5%.[11]
Tier 2. Retatrutide: TRIUMPH-1 randomised 2,339 adults with obesity for 80 weeks and reported −17.6%, −23.7% and −25.0% in the three dose arms against −3.9%, published in September 2026; Lilly says it plans a US filing in the first quarter of 2027.[7][12] CagriSema: REDEFINE 1 randomised 3,417 adults for 68 weeks and found −20.4% against −3.0%, a difference of 17.3 points; Novo Nordisk filed an NDA on 18 December 2025 and no decision had been announced by 9 October 2026.[13][14] Mazdutide: GLORY-2 randomised 461 Chinese adults two-to-one to mazdutide or placebo for 60 weeks and found −16.65% against −1.50%; China's regulator approved it for weight management in June 2025.[15][16] Survodutide: SYNCHRONIZE-1 randomised 725 adults for 76 weeks and found −12.2% and −13.0% in the two dose arms against −5.4%, a smaller margin than the others, with gastrointestinal events in 89.7% of the high-dose group.[6]
Tier 3. Cagrilintide alone, the long-acting amylin analogue, produced 10.8% loss at its top dose against 3.0% on placebo over 26 weeks in a 706-person phase 2 trial, and beat liraglutide by 1.8 points; phase 3 began in November 2025.[8][17] Maridebart cafraglutide, an antibody-peptide conjugate, produced 12.3% to 16.2% loss against 2.5% in a 592-person phase 2 trial.[18] Amycretin's phase 1b/2a reported up to 24.3% at 36 weeks, but at a single site with heavy dropout, and its phase 3 programme only started in February 2026.[19][20] These are real signals from real trials. They are not approvals, and the gap between a phase 2 effect and an approved label is where a lot of compounds have died.
Tiers 4 to 6 are the subject of their own section below, because the compounds in them are what most people searching this phrase will actually be offered.
What did the phase 3 trials measure?
Weight change against placebo over 56 to 80 weeks in adults with obesity, plus the proportions reaching 5%, 10%, 15% and 20% thresholds, discontinuation and adverse events. The table reports each trial's own figures and estimand by trial and agent, without dose arms, and nothing in it translates to anything outside those trials.
| Trial (agent) | n, duration | Weight change, drug vs placebo | Responders | Tolerability |
|---|---|---|---|---|
| SCALE (liraglutide)[11] | 3,731; 56 weeks | −8.4 vs −2.8 kg (difference −5.6 kg) | ≥5%: 63.2% vs 27.1%; >10%: 33.1% vs 10.6% | Serious events 6.2% vs 5.0%; nausea and diarrhoea most common |
| STEP 1 (semaglutide)[4] | 1,961; 68 weeks | −14.9% vs −2.4% (−12.4 points) | ≥10%: 69.1% vs 12.0%; ≥15%: 50.5% vs 4.9% | Discontinuation for GI events 4.5% vs 0.8% |
| SURMOUNT-1 (tirzepatide, highest dose)[5] | 2,539; 72 weeks | −20.9% vs −3.1% (−17.8 points) | ≥5%: 91% vs 35%; ≥20%: 57% vs 3% | AE-related discontinuation 6.2% vs 2.6% |
| TRIUMPH-1 (retatrutide, highest dose)[7][21] | 2,339; 80 weeks | −25.0% vs −3.9% (−21.0 points) | Reported in the company's efficacy estimand: ≥25% 62.5% vs 2.2% | AE discontinuation 11.3% vs 4.9% at the highest dose (company data) |
| REDEFINE 1 (CagriSema)[13][14] | 3,417; 68 weeks | −20.4% vs −3.0% (−17.3 points) | ≥5%: 91.9% vs 31.5% (company data) | GI adverse events 79.6% vs 39.9% |
| GLORY-2 (mazdutide)[15] | 461; 60 weeks | −16.65% vs −1.50% (−15.15 points) | ≥5%: 84.3% vs 33.1% | Vomiting 53.1% vs 1.3%; AE discontinuation 2.9% vs 0% |
| SYNCHRONIZE-1 (survodutide, higher dose)[6] | 725; 76 weeks | −13.0% vs −5.4% (−7.6 points) | ≥5%: 71.9% vs 46.3% | GI adverse events 89.7% vs 47.9% |
| Cagrilintide phase 2 (top dose)[8] | 706; 26 weeks | −10.8% vs −3.0% (−7.8 points) | Beat liraglutide by 1.8 points | GI adverse events 41% to 63% vs 32% |
| METAOD006 "OPTIONS" (AOD-9604, oral)[22] | 502 randomised; 24 weeks | No significant difference from placebo | Not reported | Sponsor terminated obesity development, 21 February 2007 |
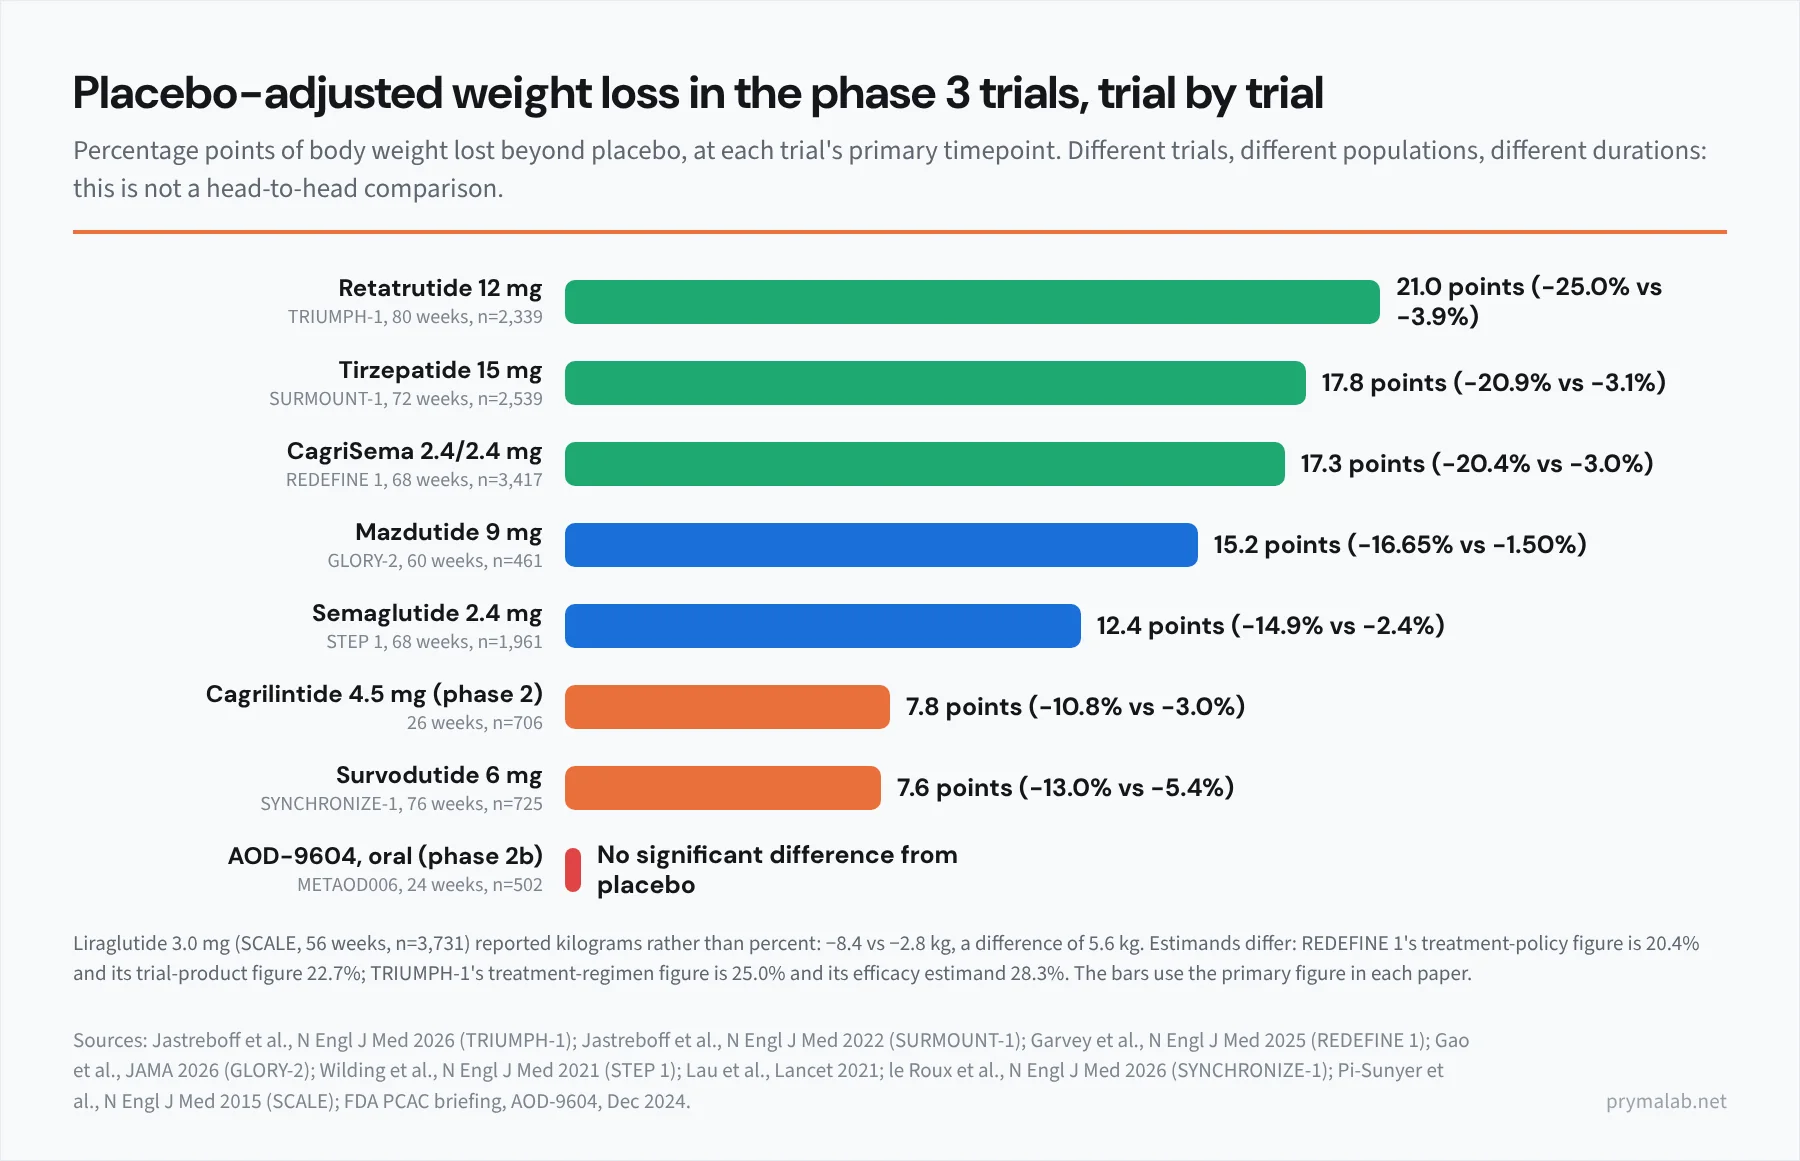
Two cautions on reading the table. First, estimands differ. REDEFINE 1's 20.4% is a treatment-policy figure that counts people who stopped the drug; Novo Nordisk's trial-product figure for the same trial is 22.7%.[13][14] TRIUMPH-1's 25.0% is the treatment-regimen figure; Lilly's efficacy estimand is 28.3%.[7][21] A page that quotes the larger number without saying which it is has made a choice for you. Second, the populations differ: GLORY-2 enrolled Chinese adults with a mean BMI of 34, SURMOUNT-1 a mean of 38, and the glucagon-containing agents were tested at different durations. The bars in Figure 2 are each trial against its own placebo, not against each other. The head-to-head trials are the next section.
How do the approved agents compare head to head?
In the only randomised comparison of the two market leaders at weight-management doses in people without diabetes, tirzepatide beat semaglutide 2.4 mg by 6.5 percentage points over 72 weeks. Semaglutide beat liraglutide by 9.4 points in STEP 8. CagriSema failed to show non-inferiority to tirzepatide in REDEFINE 4. No randomised trial has compared retatrutide with semaglutide or tirzepatide (its only active comparator so far is dulaglutide, in a phase 2 diabetes trial), so its apparent lead rests on cross-trial comparison.[23]
SURMOUNT-5 randomised 751 adults with obesity and without diabetes to maximum-tolerated-dose tirzepatide or semaglutide for 72 weeks, open-label: least-squares mean change −20.2% against −13.7%, waist circumference −18.4 against −13.0 cm, both p<0.001.[24] STEP 8 randomised 338 adults to semaglutide, liraglutide or matching placebo for 68 weeks (126 and 127 in the active arms), with the active comparison open-label: −15.8% against −6.4%, a difference of 9.4 points, with 55.6% against 12.0% losing at least 15%, and 27.6% of liraglutide participants discontinuing treatment against 13.5%.[25] REDEFINE 4 compared CagriSema with tirzepatide over 84 weeks in 809 people and, by Novo Nordisk's own filing, "did not achieve its primary endpoint of demonstrating non-inferiority on weight loss", with 20.2% against 23.6% on the treatment-regimen estimand.[26]
Three things follow. The order among the approved peptides is tirzepatide, then semaglutide, then liraglutide, and it comes from randomised trials rather than from comparing press releases. CagriSema sits between semaglutide and tirzepatide: it beat semaglutide 2.4 mg by 6.5 points in REDEFINE 5 (−18.4% against −11.9% over 68 weeks in 331 East Asian adults) and lost to tirzepatide in REDEFINE 4.[27][26] And every obesity head-to-head trial so far has been open-label, which is a limitation worth knowing even if it is unlikely to reverse a 6.5-point difference.
What happens when treatment stops, and what happens to muscle?
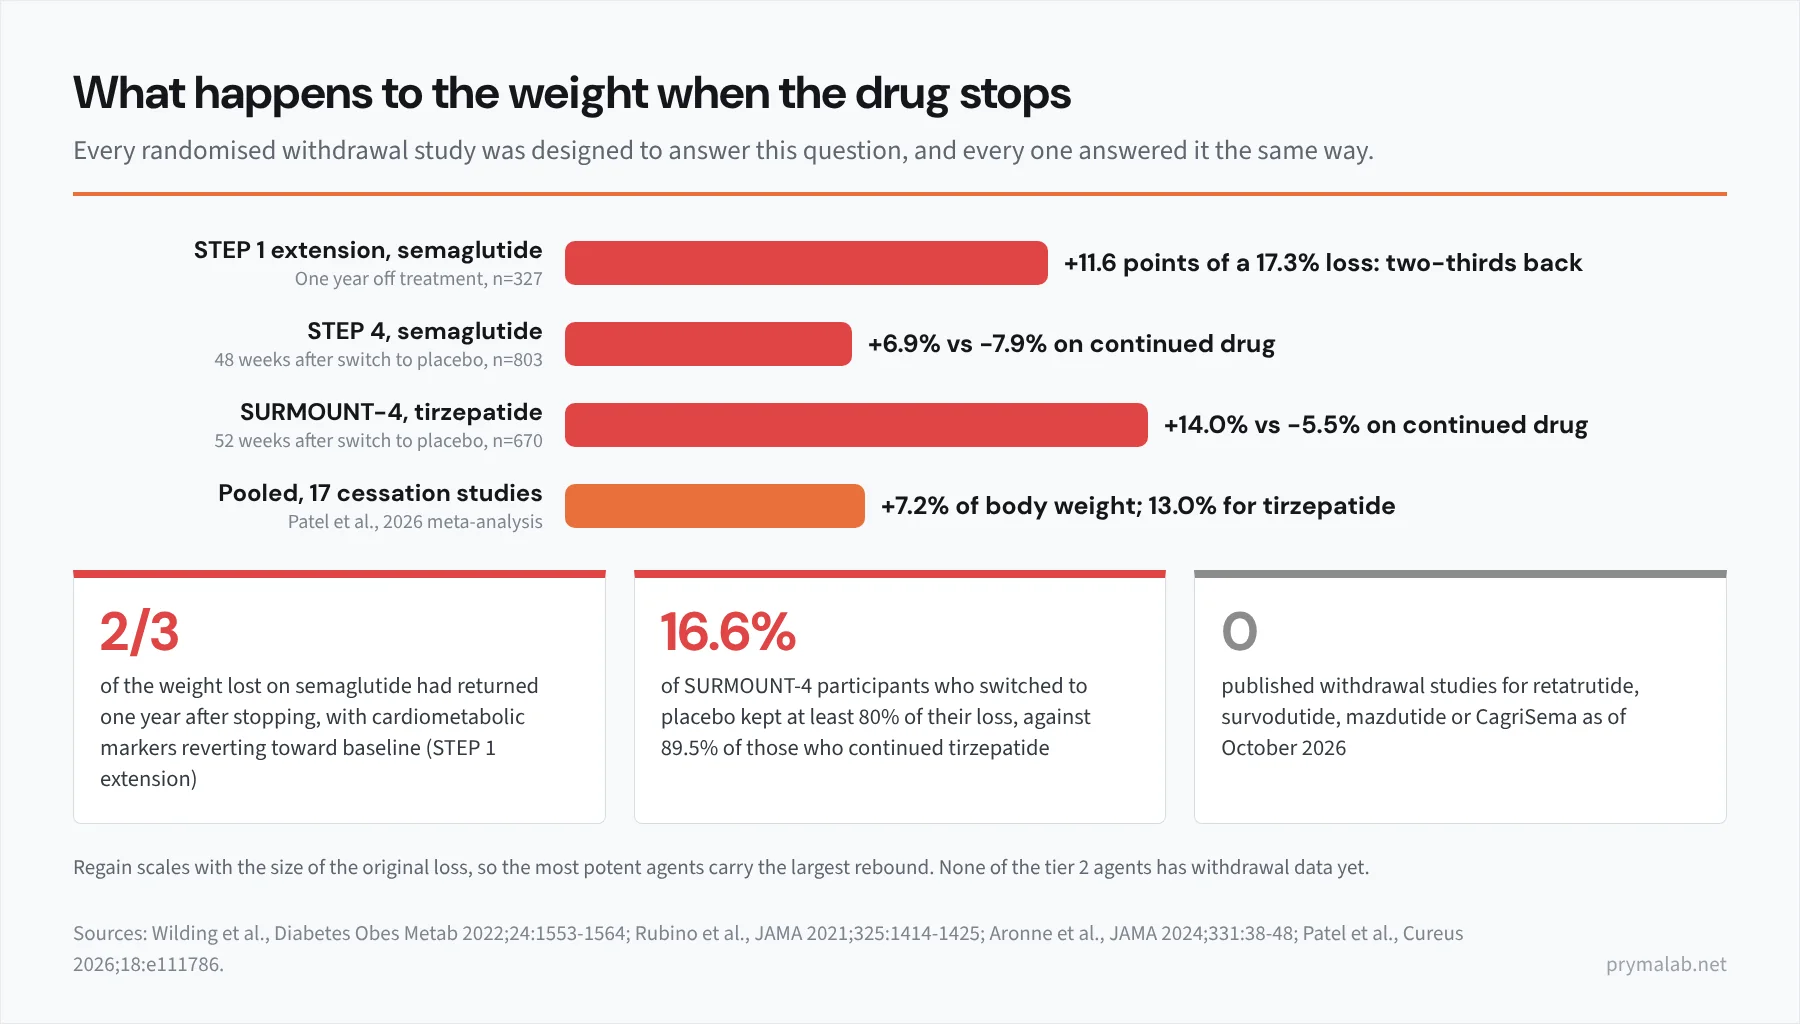
Most of the weight comes back. One year after semaglutide was withdrawn in the STEP 1 extension, participants had regained two-thirds of their loss. After tirzepatide was switched to placebo in SURMOUNT-4, weight rose 14.0% in 52 weeks. About a quarter of the weight lost is lean mass, the same proportion as with placebo, and no trial has measured whether that matters for function.
The withdrawal data are consistent across agents. In the STEP 1 extension, 327 participants were followed for a year after stopping semaglutide and the lifestyle programme: loss at week 68 was 17.3%, regain by week 120 was 11.6 points, net loss 5.6%, and "cardiometabolic improvements seen from week 0 to week 68 with semaglutide reverted towards baseline".[28] In STEP 4, after a 20-week run-in, 803 people were randomised to continue semaglutide or switch to placebo for 48 weeks: −7.9% against +6.9%, a 14.8-point gap.[29] In SURMOUNT-4, after 36 weeks of tirzepatide (−20.9%), 670 people were randomised to continue or switch to placebo for 52 weeks: −5.5% against +14.0%, and 89.5% of those who continued kept at least 80% of their loss against 16.6% of those who stopped.[30] A 2026 meta-analysis of 17 cessation studies put pooled regain at 7.2% of body weight: 7.19% for semaglutide, 4.83% for liraglutide, 13.04% for tirzepatide.[31] Regain scales with how much was lost, which means the most potent agents carry the largest rebound, and none of the tier 2 agents has published withdrawal data yet.
On muscle, the SURMOUNT-1 DXA substudy of 160 participants found body weight −21.3%, fat mass −33.9% and lean mass −10.9% with tirzepatide at 72 weeks, against −5.3%, −8.2% and −2.6% on placebo; "of the body weight lost, approximately 75% was fat mass and 25% was lean mass for both tirzepatide and placebo".[32] The STEP 1 DXA substudy, reported as a congress abstract rather than a paper, gave lean body mass −9.7% with semaglutide and a rising lean-to-fat ratio.[33] A network meta-analysis of 22 trials estimated lean mass loss at 0.86 kg, "approximately 25% of the total weight loss".[34] The 2026 Annals systematic review of 35 trials found the proportion of loss from muscle-related measures exceeded the 25% benchmark in about two-thirds of incretin trials and that "no study reported objective physical function outcomes".[35] So in the SURMOUNT-1 substudy the lean fraction matched placebo, although Batsis's review found incretin arms above the 25% benchmark in about 65% of cases; the absolute lean loss is larger because the total loss is larger, and whether any of it changes what a person can do has not been measured.
What are the risks?
For the incretin class: gastrointestinal events in most participants, gallbladder disease at roughly double the placebo rate, a small pancreatitis signal, and the regain described above. For products bought outside a pharmacy, the one published assay found purity of 7.7% to 14.37% against a 99% claim and endotoxin in every vial. The non-incretin compounds have their own, mostly unmeasured, safety records.
The approved labels carry the pooled numbers. Wegovy: 6.8% of semaglutide 2.4 mg patients discontinued for adverse reactions against 3.2% on placebo; cholelithiasis 1.6% against 0.7%; cholecystitis 0.6% against 0.2%; adjudicated acute pancreatitis in 4 semaglutide patients against 1.[36] Zepbound: gastrointestinal adverse events in 56% at every dose against 30%; cholecystitis 0.7% against 0.2%; acute pancreatitis 0.2% in both arms.[37] Saxenda: gastrointestinal disorders in 68% against 39%; cholelithiasis 2.2% against 0.8%; acute pancreatitis 0.3% against 0.1%.[38] A meta-analysis of 76 randomised trials put the relative risk of gallbladder or biliary disease at 1.37 overall and 2.29 in weight-loss trials.[39] A 2025 meta-analysis of 21 cardiovascular outcome trials in 99,599 patients found gallbladder events up 26% and gastrointestinal events up 63%, with no difference in pancreatitis.[40] The higher-potency agents are less tolerable: discontinuation for adverse events reached 11.3% at the highest retatrutide dose in TRIUMPH-1 by Lilly's figures, and dysaesthesia, an unusual skin-sensation side effect, affected 12.5% at that dose and 22.9% in the higher-dose semaglutide arm of STEP UP.[21][41]
The risk that is specific to the market this page is read from is the product itself. Ashraf and colleagues bought semaglutide from online sellers without a prescription. Three of six orders never arrived. The three vials that did contained 28.56% to 38.69% more semaglutide than the label stated, had purity of 7.7% to 14.37% against a claimed 99%, and all three contained endotoxin at 2.1645 to 8.9511 EU/mg; the authors classed every vial as "probable substandard and falsified".[42] In FAERS, reports involving compounded GLP-1 products carried adjusted reporting odds of 48.92 for preparation errors and 19.00 for contamination relative to the approved products.[43] The FDA's own page, current to 1 October 2026, logs 990 adverse-event reports for compounded semaglutide and more than 730 for compounded tirzepatide, including dosing errors "some requiring hospitalization".[44] None of that is a property of the molecule. All of it is a property of where it came from.
What about the compounds sold as fat-loss peptides outside the incretin class?
They sort into three groups: compounds that were tested for weight and failed or were stopped, compounds that were tested for something else and turned out weight-neutral, and compounds that have never been given to a person with a weight endpoint. The last group is the largest and includes most of what the phrase "fat loss peptides" is used to sell.

AOD-9604: the largest weight-loss programme, and the clearest failure
AOD-9604 is a 16-residue synthetic analogue of residues 177 to 191 of human growth hormone with an added N-terminal tyrosine, developed by Metabolic Pharmaceuticals in Melbourne on the premise that the lipolytic region of GH could be separated from its effects on growth and glucose.[2][45] It is not the same molecule as hGH fragment 176-191, which WADA lists separately and for which no human trial of any kind exists.[46] Between 2001 and 2006 the sponsor ran six randomised trials in 893 people, the two largest registered in Australia rather than on ClinicalTrials.gov.[2]
What the record shows is best read from the FDA's 2024 review, because the efficacy data were never published in a journal. The only peer-reviewed human paper, Stier and colleagues 2013, reports safety and tolerability across the six trials and no weight results at all; its line that the profile was "indistinguishable from placebo" is a safety statement that gets quoted as if it were efficacy.[2][22] The decisive trial, METAOD006, a phase 2b study, randomised 502 adults with BMI 30 to 45 to three oral doses or placebo for 24 weeks alongside a supervised diet and exercise programme, powered for an 80% chance of detecting a 1.8 kg placebo-subtracted difference. It did not find one. On 21 February 2007 the company announced that the results "do not support the commercial viability of the drug as a treatment for obesity. Development of the drug for this condition is terminated."[22] FDA's summary: "In most of the studies we identified, AOD-9604 failed to show benefit for weight reduction when compared to placebo."[22] The agency also found no human data for the injectable or transdermal routes that are actually sold, flagged bone-health signals in rats, possible liver toxicity in monkeys and equivocal genotoxicity, and found no US or foreign regulatory recognition of the compound; the "GRAS" status that vendors repeat traces to a food-ingredient expert panel described in Stier's paper, not to any FDA action.[22][2] On 4 December 2024 the Pharmacy Compounding Advisory Committee voted 0 to 12 against adding it to the 503A list.[47] The AOD-9604 reference covers the molecule in detail.
The growth hormone secretagogues
CJC-1295 DAC, a GHRH analogue that binds albumin, raised GH and IGF-1 for days in healthy volunteers.[48] That and two further hormone-response studies in healthy adults are the whole of its published human pharmacology. Its phase 2 in HIV lipodystrophy was terminated in 2006 after a participant died of a myocardial infarction, and "the data from that study has not been published"; FDA counts 63 healthy adults as the total human exposure, most dosed once.[49][50] The committee voted 0 to 13 against listing four of the five CJC-1295 substances nominated, and 1 to 12 against the fifth.[47] Ipamorelin's only published randomised trial was in post-operative ileus after bowel resection, where it missed its endpoint (time to first tolerated meal 25.3 against 32.6 hours, p=0.15), with two deaths in the ipamorelin arm; a second 320-patient ileus trial was completed in 2014 and has never reported results; FDA found no human study that measured weight or body composition.[51][52][53] GHRP-2, in the one human feeding study, increased food intake by 35.9%.[9] GHRP-6 and hexarelin have no registered trials.[54] The only "body composition" report for a GHRP combination is a chart review of 14 compliant men on testosterone therapy whose IGF-1 rose; nobody measured their weight or fat.[55] Tesamorelin, the one currently approved GHRH analogue, reduced visceral fat by 15.4% against placebo in 806 patients with HIV lipodystrophy while leaving subcutaneous fat unchanged, and its 2025 label states that it "is not indicated for weight loss management as it has a weight-neutral effect".[56][57] MK-677, the oral non-peptide secretagogue, is the contrast case already described: lean mass up, fat unchanged, weight up, and a hip-fracture trial stopped for a heart-failure signal.[10][58]
MOTS-c, 5-amino-1MQ and Lipo-C
MOTS-c reduced diet-induced obesity in mice. In humans, the FDA wrote in its briefing document for the July 2026 compounding committee meeting, "the nomination did not include, and FDA has not identified, any clinical studies or human exposure data for MOTS-c via any route of administration", and it noted that MOTS-c is rapidly hydrolysed in human blood in vitro, which raises the question of whether it can reach an active concentration in the body at all.[3] The compound sometimes cited as MOTS-c's human trial is CB4211, a modified analogue made by CohBar, whose phase 1b in 20 people with fatty liver found liver fat falling about equally on drug and placebo (−5.03% against −4.88%); CohBar then merged into an oncology company.[59][60][61] The first registered trial of MOTS-c itself started in China in February 2026 with insulin sensitivity, not weight, as its endpoint.[62] 5-amino-1MQ is a small-molecule inhibitor of the enzyme NNMT, not a peptide; it reduced fat mass in mice, has rat-only pharmacokinetics, and has zero registered human studies.[63][64][54] Lipotropic injections (methionine, inositol, choline, B12, sometimes carnitine) are compounded preparations; a PubMed search for controlled human weight-loss trials of injectable lipotropics returned none.[65]
Two non-peptides that get listed anyway
Tesofensine is a triple monoamine reuptake inhibitor, not a peptide. Its phase 2 produced weight loss 9.2 and 10.6 percentage points greater than diet and placebo in the two higher-dose arms over 24 weeks in 203 patients, in a paper that now carries a 2013 expression of concern.[66] The Mexican phase 3 that is often cited was never published or registered, and on 6 November 2024 the licensor announced that the Mexican regulator had not approved it; the February 2023 event sometimes described as an approval was a committee opinion.[67] It is not approved anywhere this review could find. The tesofensine reference has the rest. MK-677 is covered above.
Which weight-loss peptides are approved, and what is the status of the rest?
Liraglutide, semaglutide and tirzepatide are approved by the FDA and EMA for chronic weight management in general obesity. Retatrutide, survodutide, CagriSema, cagrilintide, amycretin and MariTide are investigational in the US and EU; mazdutide is approved in China. Every non-incretin compound above is unapproved for weight loss, and the FDA has stated in writing that "research use only" labels do not change what a product sold with weight-loss claims is.
| Compound | FDA | EMA | FDA 503A compounding list | WADA 2026 |
|---|---|---|---|---|
| Liraglutide | Saxenda approved 23 Dec 2014 | Approved 23 Mar 2015 | Approved drug; shortage-based compounding ended | Not prohibited |
| Semaglutide | Wegovy 4 Jun 2021; 7.2 mg 19 Mar 2026; tablets 22 Dec 2025 | Approved 6 Jan 2022; 7.2 mg Feb 2026; tablets Jul 2026 | Shortage resolved 21 Feb 2025; discretion ended Apr to May 2025 | Not prohibited; markers in the 2026 Monitoring Program |
| Tirzepatide | Zepbound 8 Nov 2023 | Mounjaro approved 15 Sep 2022 (diabetes); weight-management indication added later | Shortage resolved 2 Oct 2024, reaffirmed 19 Dec 2024 | Not prohibited; markers monitored |
| Retatrutide | Not approved; filing planned Q1 2027 | Not approved | "Cannot be used in compounding under federal law" (FDA) | Not prohibited |
| CagriSema | NDA filed 18 Dec 2025; pending | Not approved | Cagrilintide: cannot be used in compounding (FDA) | Not prohibited |
| Survodutide; mazdutide | Not approved | Not approved | Named in FDA warning letters as falsely labelled "for research" | Not prohibited |
| AOD-9604 | Not approved; PCAC 0 to 12 against (Dec 2024) | Not approved | In no category as of 14 May 2026 (nomination withdrawn) | Prohibited at all times, S2.2.3, named |
| CJC-1295; ipamorelin; sermorelin | Not approved (sermorelin's Geref approval withdrawn 2009) | Not approved | In no category as of 14 May 2026 | Prohibited at all times, S2.2.3 |
| GHRP-2; GHRP-6; hexarelin | Not approved | Not approved | GHRP-2 and GHRP-6 in Category 3 (nominated without adequate support) | Prohibited at all times, S2.2.3 |
| Tesamorelin | Egrifta approved 2010 for HIV lipodystrophy; Egrifta WR 25 Mar 2025 | Not approved | Approved drug; named in an August 2026 warning letter when sold as a research peptide | Prohibited at all times, S2.2.3 |
| MOTS-c | Not approved; no human data (FDA briefing, Jul 2026 meeting) | Not approved | Removed from Category 2 in April 2026; not thereby compoundable | Prohibited at all times, S4.4.1 |
| 5-amino-1MQ; tesofensine | Not approved | Not approved | Not listed | Not named; tesofensine prohibited in competition, S6.B |
The FDA's position on research-labelled GLP-1 products is now stated in three warning letters that use nearly identical language. To Summit Research Peptides, 10 December 2024: "Despite statements on your product labeling marketing your products as 'RESEARCH USE ONLY' and 'INTENDED AS A RESEARCH CHEMICAL ONLY,' evidence obtained from your websites establish that your products are intended to be drugs for human use."[68] To Pink Pony Peptides, 31 March 2026, the same finding, with the claims "Reduce appetite and increase satiety" and "three times the fat-fighting horsepower" quoted back as evidence of intent.[69] To Tex Peptides, 24 August 2026, the same again, adding that selling bacteriostatic water alongside the vials provides "the means to prepare an injectable drug for human administration".[70] The agency's standing page states that "FDA has warned companies that have illegally sold unapproved drugs containing semaglutide, tirzepatide, retatrutide, survodutide or mazdutide that are falsely labeled 'for research purposes' or 'not for human consumption'".[44] The 2026 compounding picture for the non-incretin peptides is different and more confusing: in April 2026 the FDA removed twelve peptides, including MOTS-c, from its Category 2 "significant safety risk" list, which the market has read as rehabilitation; the agency's position is that removal "does not make these substances eligible for 503A compounding", and that they remain unapproved new drugs when marketed for a therapeutic use.[71][72]
On sport: no GLP-1 drug appears on the WADA 2026 Prohibited List, semaglutide and tirzepatide markers are in the 2026 Monitoring Program, and the 2027 List approved in September 2026 again leaves them permitted.[73][74][75] Every growth-hormone-axis peptide on this page is prohibited at all times under S2.2.3, which names AOD-9604 and hGH 176-191 as examples of GH fragments, CJC-1295, sermorelin and tesamorelin as GHRH analogues, ipamorelin and ibutamoren as secretagogues, and hexarelin, GHRP-2 and GHRP-6 as GHRPs; MOTS-c is named under S4.4.1 as an AMPK activator.[46] The efficacy question and the eligibility question are independent, and for an athlete the second one is settled.
Where PrymaLab fits
PrymaLab supplies research-grade peptides, including semaglutide, tirzepatide, retatrutide and several of the non-incretin compounds discussed above, for laboratory use only, through the metabolic peptide catalogue, alongside identity and purity testing listings for laboratories verifying the material they hold. None of it is Wegovy, Zepbound or Saxenda, and this page exists so that anyone comparing the compounds can see which of them has a human record and which does not, including the ones in the catalogue that do not.
One analytical point follows from the Ashraf data. The approved drugs are characterised to pharmaceutical standards: identity by mass spectrometry against a reference standard, purity by HPLC with impurities identified, endotoxin by LAL assay, content by validated assay. A vial from an unknown source has none of that behind it, and a "99%" on a label is a claim, not a measurement, until a certificate of analysis for that lot shows it. PrymaLab tests every lot in its own laboratory (RP-HPLC for purity, LC-MS for identity); check that the certificate matches the lot number on your vial and can be verified at https://prymalab.net/testing/verify/. Under PrymaLab's third-party testing guarantee, if any independent laboratory finds the wrong compound or less than the stated purity or amount, the order is refunded and the test reimbursed. The purity testing guide covers what HPLC, mass spectrometry and endotoxin testing can each establish, and what a certificate has to show before a purity figure means anything.
What this article does not settle
- Whether any tier 2 agent will be approved, or when. CagriSema's decision is pending; retatrutide's filing is a plan; survodutide has no announced filing date; REDEFINE 4 missed non-inferiority against tirzepatide.[14][12][26]
- Whether retatrutide beats tirzepatide. No randomised comparison exists; the apparent 3- to 4-point lead is cross-trial.[7][5]
- Whether the lean-mass loss matters. The proportion matches placebo; no trial has measured function.[32][35]
- Regain after the tier 2 agents. No withdrawal data have been published for retatrutide, survodutide, mazdutide or CagriSema.[31]
- AOD-9604's exact per-arm numbers. METAOD006 was never published; the figures above come from FDA's reconstruction of company filings.[22]
- The CJC-1295 death. The attending physician attributed it to undiagnosed coronary disease; the data were never published and the registry and secondary reports disagree on enrolment (120 against 192).[49][50]
- The July 2026 compounding committee votes. Secondary reports say six peptides were recommended for the 503A list; FDA minutes were not posted at the time of writing.[72]
GLP-1, GIP, glucagon, amylin and the rest: what the names mean
GLP-1 (glucagon-like peptide-1) is a gut incretin hormone; GLP-1 receptor agonists are liraglutide, semaglutide and the non-peptide orforglipron. GIP is the other incretin; tirzepatide is a GIP/GLP-1 dual agonist. Glucagon receptor agonism is the second half of survodutide and mazdutide and one third of the triple agonist retatrutide. Amylin is a pancreatic satiety hormone; cagrilintide is its long-acting analogue, and CagriSema is cagrilintide plus semaglutide in one injection. Maridebart cafraglutide (MariTide) is an antibody carrying a GLP-1 agonist peptide and blocking GIP. Wegovy, Ozempic and Rybelsus are semaglutide; Zepbound and Mounjaro are tirzepatide; Saxenda and Victoza are liraglutide; Foundayo is orforglipron. Vendor codes such as "GLP-2" for tirzepatide and "GLP-3" for retatrutide are not scientific names; GLP-2 is a real and different gut hormone and there is no GLP-3. AOD-9604 is a 16-residue hGH 177-191 analogue and is not hGH fragment 176-191. Tesamorelin, sermorelin and CJC-1295 are GHRH analogues; ipamorelin, GHRP-2, GHRP-6 and hexarelin are growth hormone secretagogues; MK-677 is a non-peptide secretagogue. MOTS-c is a mitochondrial-derived peptide. 5-amino-1MQ and tesofensine are small molecules, not peptides, however they are listed.
Frequently asked questions
Which peptides are FDA approved for weight loss?
For general obesity, three peptides: liraglutide (Saxenda, December 2014), semaglutide (Wegovy injection, June 2021; 7.2 mg dose March 2026; tablets December 2025) and tirzepatide (Zepbound, November 2023). The non-peptide orforglipron (Foundayo) was approved in April 2026. A fourth peptide, setmelanotide (Imcivree, 2020), is approved only for obesity due to specific genetic deficiencies, Bardet-Biedl syndrome or hypothalamic injury. Retatrutide, survodutide, CagriSema, cagrilintide, amycretin and maridebart cafraglutide are not approved in the United States as of October 2026.
What is the most effective peptide for weight loss in trials?
Among approved drugs, tirzepatide: it beat semaglutide 2.4 mg by 6.5 percentage points in the randomised SURMOUNT-5 trial (−20.2% against −13.7% at 72 weeks). Among investigational agents, retatrutide produced the largest placebo-adjusted loss in a phase 3 trial, 21.0 points at the highest dose over 80 weeks in TRIUMPH-1, but no trial has compared it directly with tirzepatide.
Do fat loss peptides work?
The incretin-class peptides do, in randomised trials of thousands of people, with placebo-adjusted weight loss of roughly 5 to 21 percentage points depending on the agent. Most compounds marketed as "fat loss peptides" outside that class do not have that evidence: AOD-9604 failed its 502-patient trial, CJC-1295's phase 2 was terminated, tesamorelin is weight-neutral by its label, and ipamorelin, GHRP-2, GHRP-6, hexarelin, MOTS-c, 5-amino-1MQ and lipotropic injections have no human weight trial at all.
Is AOD-9604 effective for weight loss?
No trial has shown that it is. Its 502-patient phase 2b trial missed its primary endpoint, the sponsor terminated obesity development on 21 February 2007, and the FDA concluded in 2024 that "in most of the studies we identified, AOD-9604 failed to show benefit for weight reduction when compared to placebo". The only peer-reviewed human paper reports safety data and no weight results. An FDA advisory committee voted 0 to 12 against adding it to the compounding list in December 2024.
Does ipamorelin or CJC-1295 cause fat loss?
No human trial has tested either for weight or fat mass. Ipamorelin's only published randomised trial was in post-operative ileus and missed its endpoint; a second 320-patient ileus trial was completed in 2014 and never reported. CJC-1295 DAC's published human data are hormone measurements in 63 healthy volunteers; its phase 2 trial was terminated after a participant's death and never published. Both are prohibited at all times under the WADA 2026 list.
Does the weight come back after stopping GLP-1 peptides?
Most of it, within a year. In the STEP 1 extension, participants regained two-thirds of their loss in the year after stopping semaglutide. In SURMOUNT-4, switching tirzepatide to placebo led to +14.0% over 52 weeks against −5.5% on continued treatment. A 2026 meta-analysis of 17 cessation studies put pooled regain at 7.2% of body weight.
Do weight-loss peptides cause muscle loss?
About a quarter of the weight lost is lean mass. In the SURMOUNT-1 DXA substudy, lean mass fell 10.9% with tirzepatide against 2.6% on placebo, but "approximately 75% was fat mass and 25% was lean mass for both tirzepatide and placebo". A 2026 systematic review of 35 trials found no study measured physical function, so whether the lean loss matters for strength or mobility is unknown.
What are the side effects of weight-loss peptides?
Gastrointestinal events are the most common: 56% of tirzepatide patients in the Zepbound label trials, 68% of liraglutide patients in the Saxenda trials, and up to 89.7% at the high dose of survodutide. Gallbladder disease occurs at roughly double the placebo rate in weight-loss trials. Discontinuation for adverse events ran from about 4% to 7% for semaglutide and tirzepatide to 11.3% at the top retatrutide dose. The non-incretin compounds have little or no human safety data.
Is retatrutide approved?
No. TRIUMPH-1 was published in September 2026 and Lilly says it plans to file for US approval in the first quarter of 2027. The FDA's page on unapproved GLP-1 drugs states that retatrutide "cannot be used in compounding under federal law" and that the agency has warned companies selling it labelled "for research purposes".
Are GLP-1 peptides banned in sport?
No. No GLP-1 drug appears on the WADA 2026 Prohibited List; markers of semaglutide and tirzepatide are in the 2026 Monitoring Program, and the 2027 list approved in September 2026 keeps them permitted. Every growth-hormone-axis peptide sold for fat loss, including AOD-9604, CJC-1295, ipamorelin, sermorelin, tesamorelin, GHRP-2, GHRP-6 and hexarelin, is prohibited at all times under S2.2.3, and MOTS-c under S4.4.1.
What does "research use only" mean for weight-loss peptides?
It means the product is sold as a laboratory reagent, not as a drug. The FDA has stated in warning letters of December 2024, March 2026 and August 2026 that such labelling does not change a product's status when a seller's website shows it is intended for human use, and its standing page says it has warned companies selling semaglutide, tirzepatide, retatrutide, survodutide and mazdutide "falsely labeled 'for research purposes'". The one published assay of online-sourced semaglutide found purity of 7.7% to 14.37% against a 99% claim and endotoxin in every vial.
Is MOTS-c a weight-loss peptide?
In mice it reduced diet-induced obesity. In humans there is no data: the FDA wrote in its briefing document for a July 2026 advisory committee meeting that it had identified no clinical studies or human exposure data for MOTS-c by any route. A related analogue, CB4211, was tested in 20 people with fatty liver and liver fat fell about equally on drug and placebo. The first registered trial of MOTS-c itself began in February 2026 with insulin sensitivity, not weight, as its endpoint.
References
- Lincoff AM, Brown-Frandsen K, Colhoun HM, et al. Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes. N Engl J Med. 2023;389(24):2221-2232. SELECT: 17,604 adults with cardiovascular disease and overweight or obesity, median follow-up 39.8 months. PMID 37952131
- Stier H, Vos E, Kenley D. Safety and tolerability of the hexadecapeptide AOD9604 in humans. J Endocrinol Metab. 2013;3(1-2):7-15. Pooled safety analysis of six trials in 893 participants; reports no efficacy outcomes. Journal of Endocrinology and Metabolism
- US Food and Drug Administration. Pharmacy Compounding Advisory Committee briefing document: MOTS-c-related bulk drug substances, meeting of 23 and 24 July 2026. States that the nomination did not include, and FDA has not identified, any clinical studies or human exposure data for MOTS-c via any route of administration, and notes rapid hydrolysis in human blood in vitro. FDA (PDF)
- Wilding JPH, Batterham RL, Calanna S, et al. Once-Weekly Semaglutide in Adults with Overweight or Obesity. N Engl J Med. 2021;384(11):989-1002. STEP 1: 1,961 adults, 68 weeks, semaglutide versus placebo. PMID 33567185
- Jastreboff AM, Aronne LJ, Ahmad NN, et al. Tirzepatide Once Weekly for the Treatment of Obesity. N Engl J Med. 2022;387(3):205-216. SURMOUNT-1: 2,539 adults, 72 weeks, three tirzepatide doses versus placebo. PMID 35658024
- le Roux CW, Wharton S, Startseva E, et al. Survodutide Once Weekly for the Treatment of Adults with Obesity. N Engl J Med. 2026;395(8):776-787. SYNCHRONIZE-1: 725 adults, 76 weeks, two survodutide doses versus placebo. PMID 42253238
- Jastreboff AM, Kaplan LM, Davies MJ, et al. Retatrutide, a Triple Hormone Receptor Agonist, for Treatment of Obesity. N Engl J Med. 2026. TRIUMPH-1: 2,339 adults with obesity, 80 weeks, three retatrutide doses versus placebo. Published online September 2026. PMID 42814954
- Lau DCW, Erichsen L, Francisco AM, et al. Once-weekly cagrilintide for weight management in people with overweight and obesity: a multicentre, randomised, double-blind, placebo-controlled and active-controlled, dose-finding phase 2 trial. Lancet. 2021;398(10317):2160-2172. Cagrilintide phase 2: 706 participants, 26 weeks, five doses versus placebo and an active liraglutide 3.0 mg arm. PMID 34798060
- Laferrère B, Abraham C, Russell CD, et al. Growth hormone releasing peptide-2 (GHRP-2), like ghrelin, increases food intake in healthy men. J Clin Endocrinol Metab. 2005;90(2):611-4. Seven healthy lean men, crossover; GHRP-2 infusion increased buffet intake by 35.9%. PMID 15699539
- Nass R, Pezzoli SS, Oliveri MC, et al. Effects of an oral ghrelin mimetic on body composition and clinical outcomes in healthy older adults: a randomized trial. Ann Intern Med. 2008;149(9):601-11. MK-677 (ibutamoren) versus placebo in 65 healthy older adults, two-year trial with primary endpoints at 12 months; fat-free mass +1.1 kg, no change in total or visceral fat, body weight +2.7 kg versus +0.8 kg. PMID 18981485
- Pi-Sunyer X, Astrup A, Fujioka K, et al. A Randomized, Controlled Trial of 3.0 mg of Liraglutide in Weight Management. N Engl J Med. 2015;373(1):11-22. SCALE Obesity and Prediabetes: 3,731 adults, 56 weeks, liraglutide versus placebo. PMID 26132939
- Eli Lilly and Company. Lilly's triple agonist retatrutide successful in two additional phase 3 obesity trials (TRIUMPH-2 and TRIUMPH-3 topline), press release, 23 July 2026; states the plan to submit retatrutide to the FDA in the first quarter of 2027. BioSpace
- Garvey WT, Blüher M, Osorto Contreras CK, et al. Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity. N Engl J Med. 2025;393(7):635-647. REDEFINE 1: 3,417 adults, 68 weeks, CagriSema versus cagrilintide alone, semaglutide alone and placebo; primary figures use the treatment-policy estimand. PMID 40544433
- Novo Nordisk A/S. Novo Nordisk submits New Drug Application to the US FDA for CagriSema for weight management (company announcement, 18 December 2025). Reports 22.7% trial-product-estimand weight loss and 91.9% of participants reaching 5% in REDEFINE 1. Novo Nordisk
- Gao L, Jiang H, Cai H, et al. Treatment With 9-mg Mazdutide for Weight Reduction in Chinese Adults With Obesity: The GLORY-2 Randomized Clinical Trial. JAMA. 2026;336(5):377-388. GLORY-2: 461 Chinese adults with obesity, 60 weeks, mazdutide versus placebo. PMID 42251595
- Innovent Biologics. Mazdutide, the first dual GCG/GLP-1 receptor agonist, received approval from China's NMPA for chronic weight management (press release, 27 June 2025). BioSpace
- ClinicalTrials.gov NCT07220642. Novo Nordisk: RENEW 1, phase 3 trial of cagrilintide in adults with overweight or obesity; start 5 November 2025. ClinicalTrials.gov
- Jastreboff AM, Ryan DH, Bays HE, et al. Once-Monthly Maridebart Cafraglutide for the Treatment of Obesity - A Phase 2 Trial. N Engl J Med. 2025;393(9):843-857. Maridebart cafraglutide phase 2: 592 participants, 52 weeks. PMID 40549887
- Dahl K, Toubro S, Dey S, et al. Amycretin, a novel, unimolecular GLP-1 and amylin receptor agonist administered subcutaneously: results from a phase 1b/2a randomised controlled study. Lancet. 2025;406(10499):149-162. Subcutaneous amycretin phase 1b/2a, single site; up to 36 weeks. PMID 40550231
- ClinicalTrials.gov NCT07339423. Novo Nordisk: AMAZE 1, phase 3 trial of amycretin in adults with overweight or obesity; start 24 February 2026. ClinicalTrials.gov
- Eli Lilly and Company. Lilly's triple agonist retatrutide delivered powerful weight loss in TRIUMPH-1 (press release, 21 May 2026): efficacy-estimand weight change 28.3% at 12 mg, adverse-event discontinuation 11.3% versus 4.9%, dysaesthesia 12.5% at 12 mg. Lilly investor relations
- US Food and Drug Administration. Pharmacy Compounding Advisory Committee briefing document: AOD-9604-related bulk drug substances, meeting of 4 December 2024. Summarises the sponsor's six trials including METAOD006 (502 randomised, 24 weeks, primary endpoint not met), the 21 February 2007 termination announcement and the non-clinical findings; records no US or foreign regulatory recognition of the compound. FDA (PDF)
- Rosenstock J, Frias J, Jastreboff AM, et al. Retatrutide, a GIP, GLP-1 and glucagon receptor agonist, for people with type 2 diabetes: a randomised, double-blind, placebo and active-controlled, parallel-group, phase 2 trial conducted in the USA. Lancet. 2023;402(10401):529-544. Phase 2 in type 2 diabetes, 281 participants, with a dulaglutide 1.5 mg active arm; body weight a secondary endpoint. PMID 37385280
- Aronne LJ, Horn DB, le Roux CW, et al. Tirzepatide as Compared with Semaglutide for the Treatment of Obesity. N Engl J Med. 2025;393(1):26-36. SURMOUNT-5: open-label head-to-head of tirzepatide and semaglutide, 751 participants, 72 weeks. PMID 40353578
- Rubino DM, Greenway FL, Khalid U, et al. Effect of Weekly Subcutaneous Semaglutide vs Daily Liraglutide on Body Weight in Adults With Overweight or Obesity Without Diabetes: The STEP 8 Randomized Clinical Trial. JAMA. 2022;327(2):138-150. STEP 8: open-label head-to-head of semaglutide 2.4 mg and liraglutide 3.0 mg, 338 participants. PMID 35015037
- Novo Nordisk A/S. Form 6-K filed with the US Securities and Exchange Commission, 23 February 2026: REDEFINE 4 topline, CagriSema versus tirzepatide 15 mg over 84 weeks in 809 participants, 20.2% versus 23.6% on the treatment-regimen estimand; primary non-inferiority endpoint not achieved. SEC EDGAR
- Yamauchi T, Becker NP, Hagemann CA, et al. Efficacy and safety of co-administered cagrilintide and semaglutide versus semaglutide alone in adults with overweight or obesity with or without type 2 diabetes in Japan and Taiwan (REDEFINE 5): a multicentre, randomised, active-controlled, phase 3a trial. Lancet Diabetes Endocrinol. 2026;14(6):450-462. REDEFINE 5: CagriSema versus semaglutide 2.4 mg in 331 adults in Japan and Taiwan, 68 weeks; treatment difference −6.5 percentage points. PMID 42009015
- Wilding JPH, Batterham RL, Davies M, et al. Weight regain and cardiometabolic effects after withdrawal of semaglutide: The STEP 1 trial extension. Diabetes Obes Metab. 2022;24(8):1553-1564. One-year off-treatment follow-up of 327 STEP 1 participants. PMID 35441470
- Rubino D, Abrahamsson N, Davies M, et al. Effect of Continued Weekly Subcutaneous Semaglutide vs Placebo on Weight Loss Maintenance in Adults With Overweight or Obesity: The STEP 4 Randomized Clinical Trial. JAMA. 2021;325(14):1414-1425. STEP 4: randomised withdrawal after a 20-week run-in, 803 participants. PMID 33755728
- Aronne LJ, Sattar N, Horn DB, et al. Continued Treatment With Tirzepatide for Maintenance of Weight Reduction in Adults With Obesity: The SURMOUNT-4 Randomized Clinical Trial. JAMA. 2024;331(1):38-48. SURMOUNT-4: 36-week open-label lead-in then 52-week randomised withdrawal, 670 participants. PMID 38078870
- Patel H, Babli SA, Shah S, et al. Post-cessation Weight Regain After Weight Management Medications: A Systematic Review and Meta-Analysis. Cureus. 2026;18(6):e111786. Seventeen cessation studies; pooled regain 7.2% of body weight. PMID 42534203
- Look M, Dunn JP, Kushner RF, et al. Body composition changes during weight reduction with tirzepatide in the SURMOUNT-1 study of adults with obesity or overweight. Diabetes Obes Metab. 2025;27(5):2720-2729. DXA substudy of 160 SURMOUNT-1 participants. PMID 39996356
- Wilding JPH, Batterham RL, Calanna S, et al. Impact of semaglutide on body composition in adults with overweight or obesity: exploratory analysis of the STEP 1 study (congress abstract, 2021). Lean body mass change −9.7% with semaglutide in the 140-participant DXA subset. Abstract PDF
- Karakasis P, Patoulias D, Fragakis N, et al. Effect of glucagon-like peptide-1 receptor agonists and co-agonists on body composition: Systematic review and network meta-analysis. Metabolism. 2025;164:156113. Network meta-analysis of 22 randomised trials. PMID 39719170
- Batsis JA, Gavras A, Gross DC, et al. Effect of Incretin-Based and Nonpharmacologic Weight Loss on Body Composition : A Systematic Review. Ann Intern Med. 2026;179(7):996-1013. Systematic review of 35 trials of incretin-based and non-pharmacological weight loss. PMID 41996180
- Wegovy (semaglutide) injection, prescribing information. Novo Nordisk. Pooled placebo-controlled trial data: discontinuation for adverse reactions 6.8% versus 3.2%; cholelithiasis 1.6% versus 0.7%; cholecystitis 0.6% versus 0.2%; adjudicated acute pancreatitis 4 versus 1 cases. Retrieved through the openFDA label API, 9 October 2026. Drugs@FDA, NDA 215256
- Zepbound (tirzepatide) injection, prescribing information. Eli Lilly and Company. SURMOUNT-1 and SURMOUNT-2 pooled data: gastrointestinal adverse reactions 56% at each dose versus 30%; cholecystitis 0.7% versus 0.2%; acute pancreatitis 0.2% in both arms. Label effective 28 August 2026, retrieved through the openFDA label API. Drugs@FDA, NDA 217806
- Saxenda (liraglutide) injection, prescribing information. Novo Nordisk. Gastrointestinal disorders 68% versus 39%; cholelithiasis 2.2% versus 0.8%; acute pancreatitis 0.3% versus 0.1%. Label effective 25 February 2026, retrieved through the openFDA label API. Drugs@FDA, NDA 206321
- He L, Wang J, Ping F, et al. Association of Glucagon-Like Peptide-1 Receptor Agonist Use With Risk of Gallbladder and Biliary Diseases: A Systematic Review and Meta-analysis of Randomized Clinical Trials. JAMA Intern Med. 2022;182(5):513-519. Meta-analysis of 76 randomised trials, 103,371 patients. PMID 35344001
- Galli M, Benenati S, Laudani C, et al. Cardiovascular Effects and Tolerability of GLP-1 Receptor Agonists: A Systematic Review and Meta-Analysis of 99,599 Patients. J Am Coll Cardiol. 2025;86(20):1805-1819. Meta-analysis of 21 cardiovascular outcome trials, 99,599 patients. PMID 40892610
- Wharton S, Freitas P, Hjelmesæth J, et al. Once-weekly semaglutide 7·2 mg in adults with obesity (STEP UP): a randomised, controlled, phase 3b trial. Lancet Diabetes Endocrinol. 2025;13(11):949-963. STEP UP: semaglutide 7.2 mg versus 2.4 mg versus placebo, 1,407 participants, 72 weeks. PMID 40961952
- Ashraf AR, Mackey TK, Vida RG, et al. Multifactor Quality and Safety Analysis of Semaglutide Products Sold by Online Sellers Without a Prescription: Market Surveillance, Content Analysis, and Product Purchase Evaluation Study. J Med Internet Res. 2024;26:e65440. Six test purchases from online sellers; three vials received and analysed for identity, content, purity and endotoxin. PMID 39509151
- McCall KL, Mastro Dwyer KA, Casey RT, et al. Safety analysis of compounded GLP-1 receptor agonists: a pharmacovigilance study using the FDA adverse event reporting system. Expert Opin Drug Saf. 2026;25(3):581-588. FAERS disproportionality analysis of compounded versus approved GLP-1 receptor agonist reports. PMID 40285721
- US Food and Drug Administration. FDA's concerns with unapproved GLP-1 drugs used for weight loss. Content current as of 1 October 2026. Includes the adverse-event counts for compounded semaglutide (990) and tirzepatide (more than 730) as of 31 May 2026 and the statement on products falsely labelled "for research purposes". FDA
- Cox HD, Smeal SJ, Hughes CM, et al. Detection and in vitro metabolism of AOD9604. Drug Test Anal. 2015;7(1):31-8. Describes AOD9604 as a 16-residue analogue of hGH 177-191 with an N-terminal tyrosine, and its in vitro metabolism. PMID 25208511
- World Anti-Doping Agency. The 2026 Prohibited List, section S2.2.3 (growth hormone fragments including AOD-9604 and hGH 176-191; growth hormone releasing hormone analogues including CJC-1295, sermorelin and tesamorelin; growth hormone secretagogues including ipamorelin and ibutamoren; growth hormone-releasing peptides including hexarelin, GHRP-2 and GHRP-6), section S4.4.1 (AMPK activators including MOTS-c) and section S6.B (tesofensine). WADA
- US Food and Drug Administration. Final summary minutes, Pharmacy Compounding Advisory Committee, 4 December 2024. Votes against placing AOD-9604 (0 yes, 12 no) and the CJC-1295 substances (0 yes, 13 no for four of the five nominated; 1 yes, 12 no for the acetate) on the 503A bulks list. FDA (PDF)
- Teichman SL, Neale A, Lawrence B, et al. Prolonged stimulation of growth hormone (GH) and insulin-like growth factor I secretion by CJC-1295, a long-acting analog of GH-releasing hormone, in healthy adults. J Clin Endocrinol Metab. 2006;91(3):799-805. Healthy adults 21 to 61 years; single and repeated doses; no body-composition endpoint. PMID 16352683
- US Food and Drug Administration. Pharmacy Compounding Advisory Committee briefing document: CJC-1295-related bulk drug substances, meeting of 4 December 2024. Records 63 healthy adults as total published human exposure, the 2006 phase 2 termination after a fatal myocardial infarction, and that the trial data have not been published. FDA (PDF)
- ClinicalTrials.gov NCT00267527. ConjuChem Biotechnologies: CJC-1295 in HIV-associated visceral adiposity, phase 2; status terminated. Enrolment 120 listed on the registry record. ClinicalTrials.gov
- Beck DE, Sweeney WB, McCarter MD, et al. Prospective, randomized, controlled, proof-of-concept study of the Ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients. Int J Colorectal Dis. 2014;29(12):1527-34. Ipamorelin after partial bowel resection, 117 enrolled and 114 analysed; time to first tolerated meal 25.3 versus 32.6 hours, p = 0.15; two deaths in the ipamorelin arm. PMID 25331030
- ClinicalTrials.gov NCT01280344. Phase 2 trial of ipamorelin in post-operative ileus after bowel resection, 320 participants, completed May 2014; no results posted and no publication identified as of 9 October 2026. ClinicalTrials.gov
- US Food and Drug Administration. Pharmacy Compounding Advisory Committee briefing document: ipamorelin, meeting of 29 October 2024. Identifies no human study with a weight or body-composition endpoint. FDA (PDF)
- ClinicalTrials.gov API v2, intervention and term queries run 9 October 2026: AOD-9604, 0 studies; 5-amino-1MQ, 0; hexarelin, 0; GHRP-6, 0; CJC-1295, 1 (terminated); ipamorelin, 3 (none with a weight endpoint). ClinicalTrials.gov
- Sigalos JT, Pastuszak AW, Allison A, et al. Growth Hormone Secretagogue Treatment in Hypogonadal Men Raises Serum Insulin-Like Growth Factor-1 Levels. Am J Mens Health. 2017;11(6):1752-1757. Retrospective chart review of 14 compliant men on testosterone therapy; serum IGF-1 only. PMID 28830317
- Falutz J, Mamputu JC, Potvin D, et al. Effects of tesamorelin (TH9507), a growth hormone-releasing factor analog, in human immunodeficiency virus-infected patients with excess abdominal fat: a pooled analysis of two multicenter, double-blind placebo-controlled phase 3 trials with safety extension data. J Clin Endocrinol Metab. 2010;95(9):4291-304. Pooled analysis of the two phase 3 tesamorelin trials in HIV-associated abdominal fat accumulation, 806 patients; visceral adipose tissue −15.4% versus placebo at 26 weeks, subcutaneous adipose tissue unchanged. PMID 20554713
- Theratechnologies Inc. Theratechnologies receives FDA approval of EGRIFTA WR (tesamorelin for injection), press release, 25 March 2025. The approved prescribing information states that tesamorelin is not indicated for weight loss management because it has a weight-neutral effect. Theratechnologies
- US Food and Drug Administration. Pharmacy Compounding Advisory Committee briefing document: ibutamoren mesylate, meeting of 29 October 2024. Notes the hip-fracture trial stopped for an excess of congestive heart failure. FDA (PDF)
- CohBar Inc. CohBar announces positive topline results from the phase 1a/1b study of CB4211 under development for NASH and obesity, press release, 10 August 2021. Liver fat change −5.03% on CB4211 versus −4.88% on placebo in 20 participants. BioSpace
- ClinicalTrials.gov NCT03998514. CohBar: phase 1a/1b study of CB4211 in healthy volunteers and subjects with non-alcoholic fatty liver disease and obesity. ClinicalTrials.gov
- Fierce Biotech. Two small biotechs morph work in oncology together: CohBar and Morphogenesis merger to form TuHURA Biosciences, 23 May 2023. Fierce Biotech
- ClinicalTrials.gov NCT07505745. Hudson Biotech: phase 2a study of MOTS-c, first registered human trial of the peptide itself; start February 2026; primary endpoint insulin sensitivity. ClinicalTrials.gov
- Neelakantan H, Vance V, Wetzel MD, et al. Selective and membrane-permeable small molecule inhibitors of nicotinamide N-methyltransferase reverse high fat diet-induced obesity in mice. Biochem Pharmacol. 2018;147:141-152. Discovery paper for 5-amino-1MQ as a selective NNMT inhibitor; diet-induced obese mice. PMID 29155147
- Babula JJ, Bui D, Stevenson HL, et al. Nicotinamide N-methyltransferase inhibition mitigates obesity-related metabolic dysfunction. Diabetes Obes Metab. 2024;26(11):5272-5282. Mouse efficacy and rat pharmacokinetics of 5-amino-1MQ; no human data. PMID 39161060
- PubMed searches run 9 October 2026: "lipotropic[TIAB] AND (obesity OR weight loss)" returned 16 records, none a controlled human trial of an injectable lipotropic preparation; "choline[Title] AND methionine[Title] AND (weight loss OR obesity) AND randomized" returned one record, a rat study. PubMed
- Astrup A, Madsbad S, Breum L, et al. Effect of tesofensine on bodyweight loss, body composition, and quality of life in obese patients: a randomised, double-blind, placebo-controlled trial. Lancet. 2008;372(9653):1906-1913. Tesofensine phase 2 (TIPO-1), 203 patients, 24 weeks. An expression of concern was published in Lancet 2013;381:1167. PMID 18950853
- Saniona AB. Mexican application for tesofensine not yet approved, company announcement, 6 November 2024. Inderes (Saniona release)
- US Food and Drug Administration. Warning letter to Summit Research Peptides, reference 695607, 10 December 2024. FDA
- US Food and Drug Administration. Warning letter to Lovega LLC dba Pink Pony Peptides, reference 721088, 31 March 2026. FDA
- US Food and Drug Administration. Warning letter to TXP Innovations LLC dba Tex Peptides, reference 735067, 24 August 2026. FDA
- Frier Levitt. FDA to remove 12 popular peptides from the Category 2 "do not compound" list, 16 April 2026. Frier Levitt
- Sheppard Mullin. FDA balances peptide policy with enforcement against unlawful peptide sellers, 2026. Reports the July 2026 advisory committee outcomes and FDA's statement that Category 2 removal does not make a substance eligible for 503A compounding. Sheppard Mullin
- World Anti-Doping Agency. The 2026 Prohibited List, International Standard, effective 1 January 2026. No GLP-1 receptor agonist appears in any section. WADA (PDF)
- World Anti-Doping Agency. The 2026 Monitoring Program, effective 1 January 2026. Item 6 reads "Markers of Semaglutide and Tirzepatide: In and Out-of-Competition". WADA (PDF)
- World Anti-Doping Agency. 2027 Prohibited List approved by the WADA Executive Committee, September 2026, effective 1 January 2027; GLP-1 receptor agonists remain outside the List. As reported by Athletics Illustrated, 28 September 2026. Athletics Illustrated
Final disclaimer: This article is an educational research reference describing published clinical trials, regulatory records and the absence of trials for certain compounds. The approved drugs discussed are prescription medicines used under medical supervision; research-grade peptides are not those drugs. PrymaLab supplies peptides for laboratory research only. Statements have not been evaluated by the FDA. Nothing here is medical advice, no dosing or administration guidance is given or implied, and nothing here is a reason to start, stop or change any medicine.
Research-grade material is not a pharmaceutical product and none of the trial findings above describe or support any use of it in people. Always verify the legal status of any research compound in your jurisdiction before purchase or use.
Formats stocked for the compounds in this article
Pryma Lipo-C: Pryma Lipo-C (FAT BLASTER). L-Carnitine: L-Carnitine 500mg. AOD9604: AOD9604 5MG, AOD-9604 6mg preloaded 3ml pen and AOD9604 10mg Nasal Spray. Semaglutide: Semaglutide 5mg, Semaglutide 10mg, Semaglutide 15mg, Semaglutide 20mg and Semaglutide 30mg. Every listing is supplied for laboratory research use with a batch certificate of analysis.