

Description
PrymaLab · Research use only
ARA-290 10mg
Cibinetide, the 11-residue erythropoietin helix-B surface peptide, 10 mg freeze-dried
ARA-290, also called cibinetide, is an 11-residue peptide modelled on the face of erythropoietin’s helix B that points into the surrounding water when the hormone sits on its receptor. This listing is a single 10 mg vial of freeze-dried powder. Research on the peptide has asked whether erythropoietin’s tissue-protective effects can be separated from red-cell production, first in rodent injury models and then in small trials in people with small nerve fibre loss.
Specifications
| Property | Value |
|---|---|
| Compound | ARA-290 Cibinetide; erythropoietin helix-B surface peptide |
| CAS number | 1208243-50-8 |
| Molecular formula | C51H84N16O21 |
| Theoretical mass | 1257.3 Da |
| Sequence / structure | pGlu-EQLERALNSS-OH (11 residues; N-terminal pyroglutamate; free C-terminus) |
| Label claim | 10 mg/vial |
| Form | Lyophilized (freeze-dried) powder or cake in a sealed glass vial with a rubber stopper and aluminium crimp cap |
| Storage, sealed | −20 °C, desiccated, dark |
| Purity specification | 99.0% or higher by RP-HPLC |
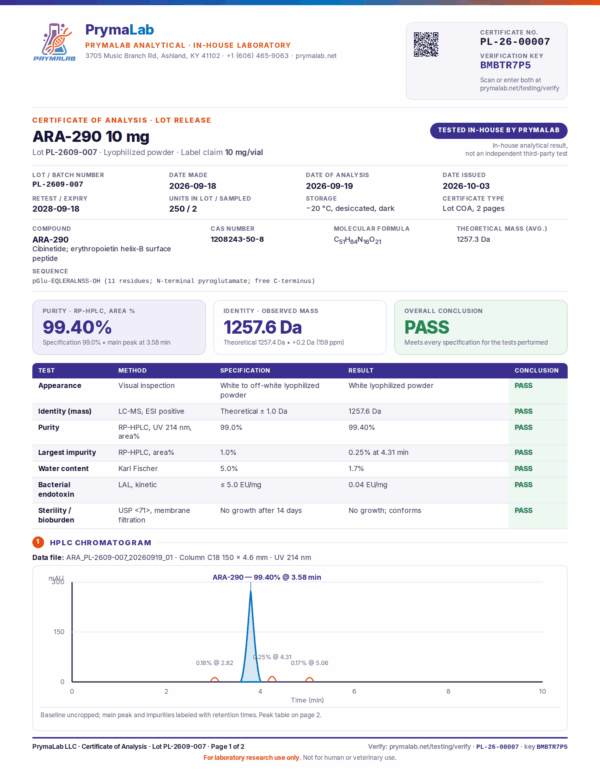
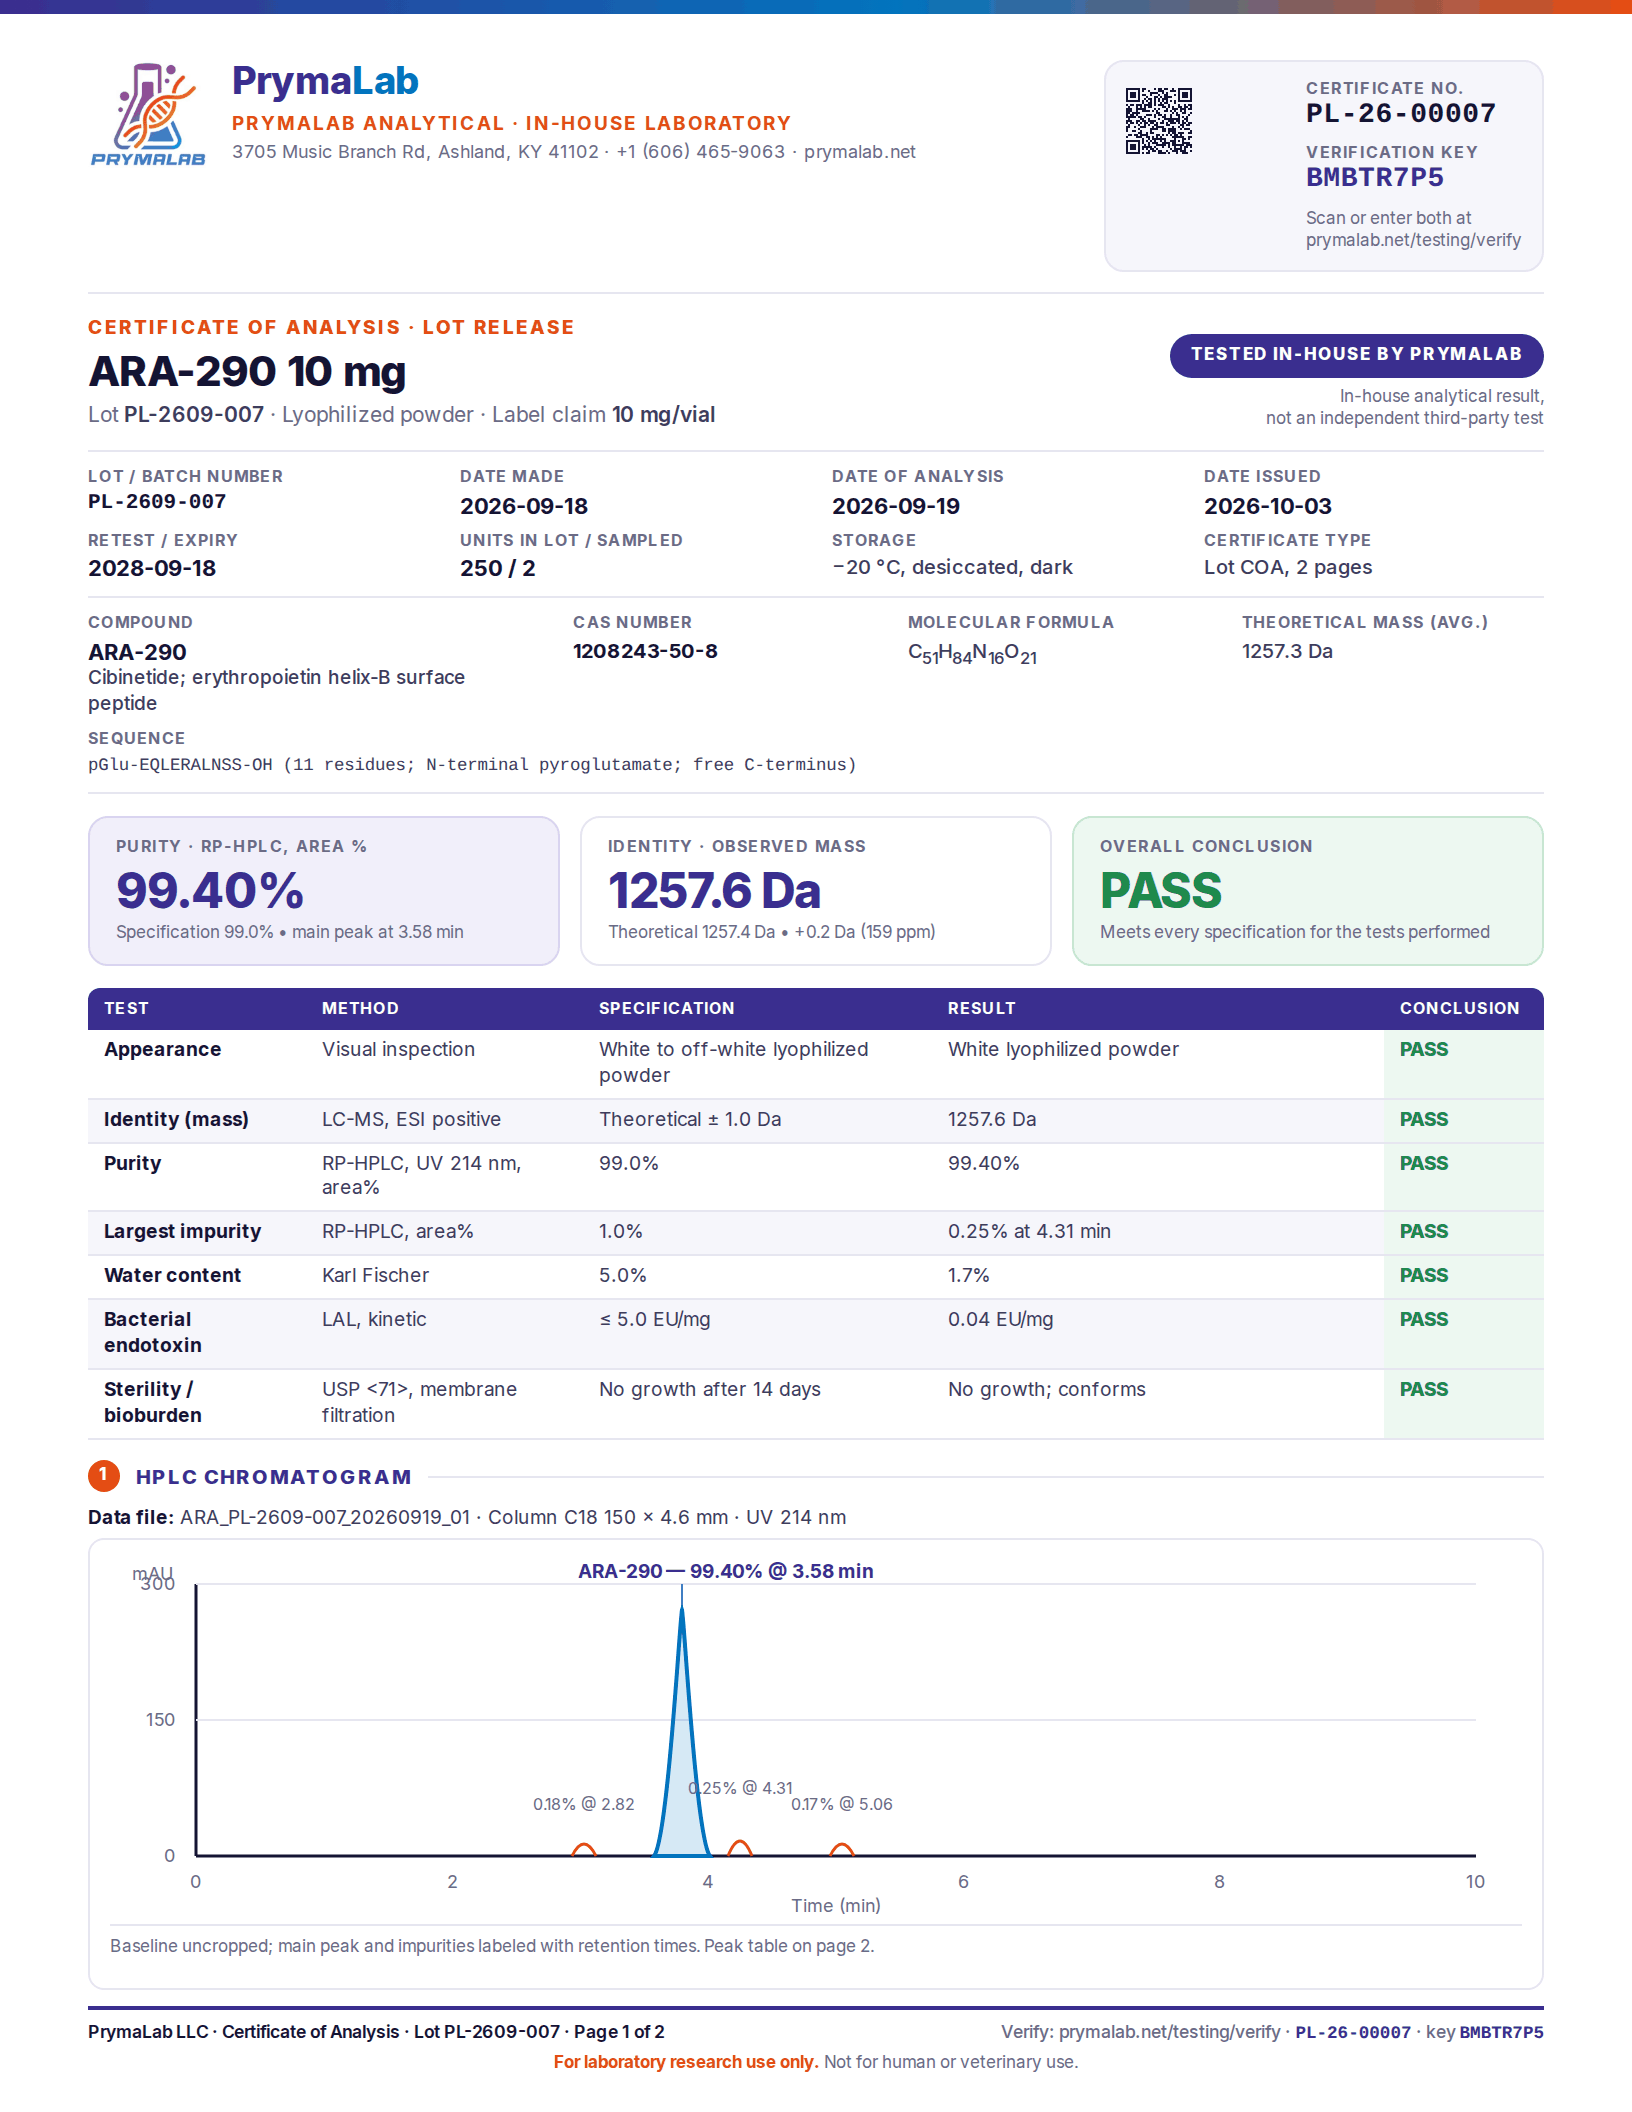
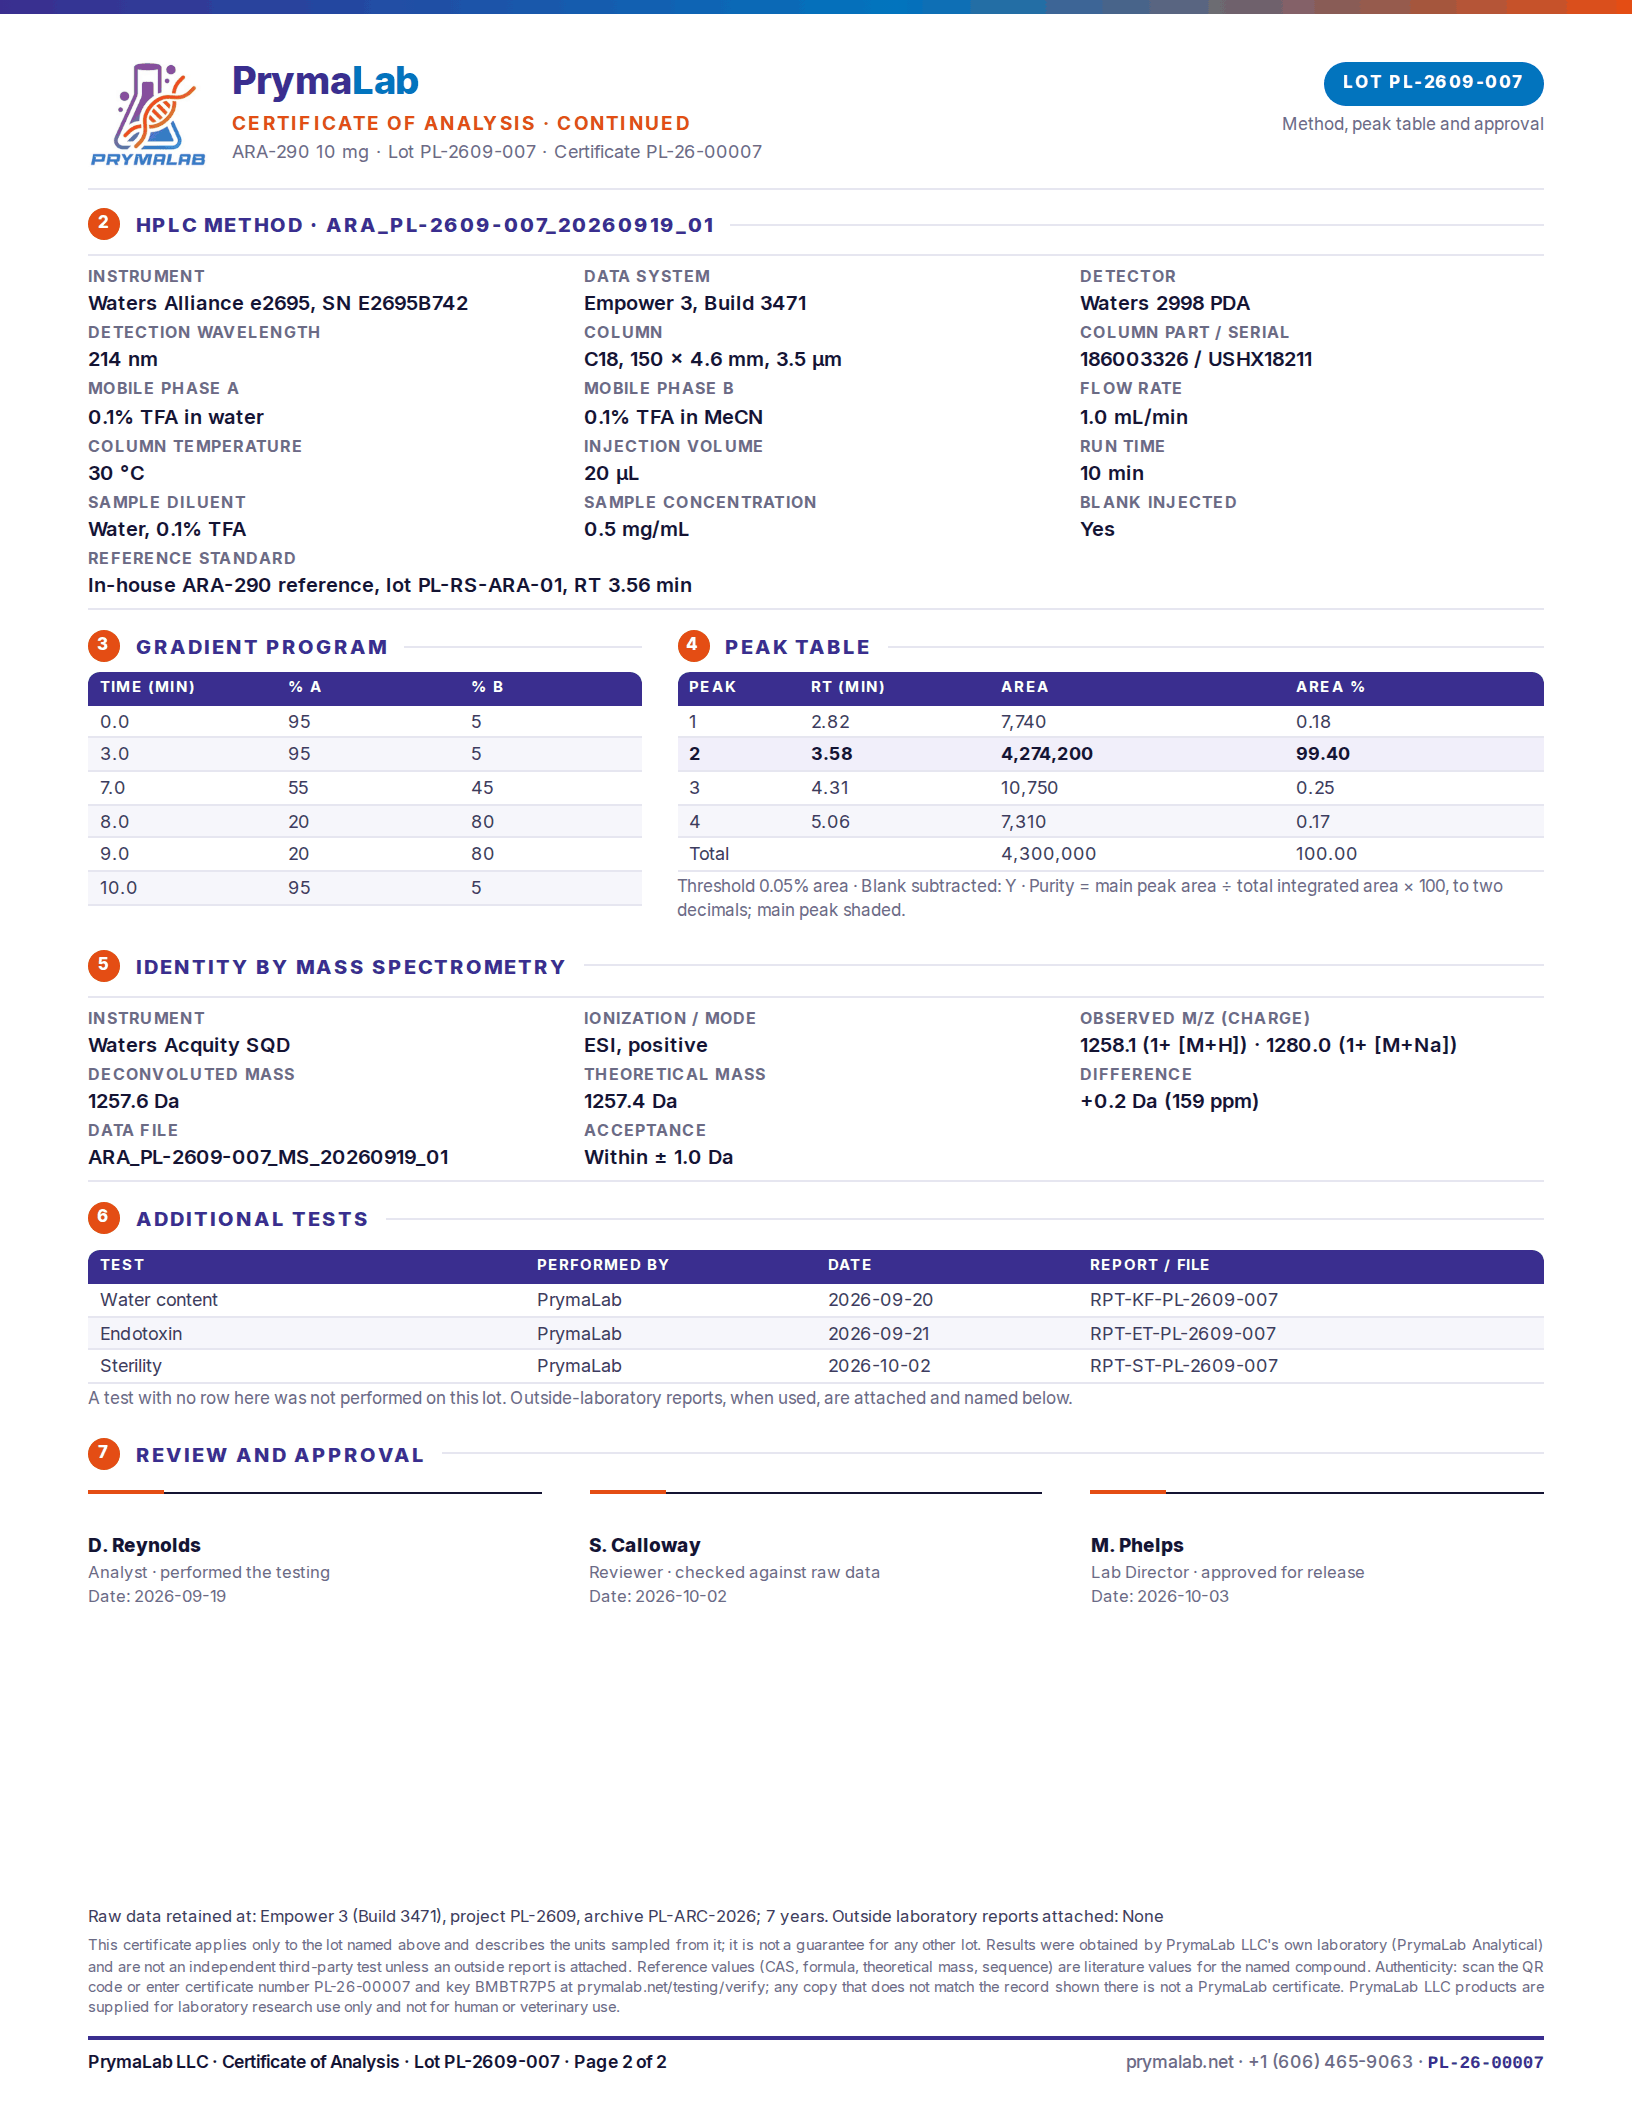
| Lot certificate | Results for the lot now shipping are in the certificate panel on this page |
| Safety data sheet | PL-SDS-015 |
Sequence and amount in the vial
The certificate gives the sequence as pGlu-EQLERALNSS-OH: eleven residues, starting with an N-terminal pyroglutamate and ending in a free C-terminus. The formula is C51H84N16O21 and the theoretical mass 1257.3 Da, the figure to compare with the LC-MS identity result on the lot certificate. In molar terms the 10 mg fill is about 8.0 µmol, slightly less once the certificate’s water content is allowed for.
The same peptide is sold already dissolved, as an ARA-290 preloaded pen holding 10 mg in 3 mL and an ARA-290 nasal spray holding 10 mg per bottle.
What the research covers
Two receptors for one hormone
Erythropoietin (EPO) controls red-cell production as a circulating hormone, and it also acts locally, in a paracrine and autocrine way, to protect many tissues from injury1. Brines and colleagues argued that the two jobs use different receptors: red-cell production goes through a homodimer of the EPO receptor, tissue protection through a complex of the EPO receptor with CD131, the beta common receptor subunit shared with the GM-CSF, IL-3 and IL-5 receptors1,2. Their 2004 evidence was biochemical and genetic. Membrane proteins from rat brain, heart, liver and kidney passed over EPO columns came out enriched in EPO receptor bound in a complex with CD131, antibodies to the EPO receptor pulled down CD131 from neuronal-like P-19 cells, and in CD131 knockout mice neither EPO nor carbamylated EPO, a derivative that does not stimulate red-cell production, was active in cardiomyocyte or spinal cord injury models2.
Why this mattered was set out in a 2008 review by Brines and Cerami: protecting tissue with recombinant EPO needs more of it than red-cell production does, with a risk of serious adverse effects, and a separate tissue-protective receptor made it possible to design derivatives, including peptides that mimic EPO’s tertiary structure, without the haematopoietic action3.
The helix B peptide
In 2008 the same group narrowed the protective region to helix B of EPO, residues 58 to 82, which faces the aqueous medium when EPO is bound to the receptor homodimer1. Helix B was neuroprotective in cell culture and protective in animal models of ischaemic stroke, diabetes-induced retinal oedema and peripheral nerve trauma1. An 11-amino-acid peptide built from the adjacent residues that form helix B’s aqueous face was also protective, in models of stroke and renal ischaemia-reperfusion, and it sped wound healing and improved cognitive function in rodents1. Neither helix B nor the 11-residue peptide stimulated red-cell production in vitro or in vivo1. The clinical papers call this peptide ARA 290 or cibinetide4,5.
Small trials in neuropathy
Most of the human work is in sarcoidosis complicated by small nerve fibre loss. A double-blind, placebo-controlled pilot in 22 people with sarcoidosis and symptoms of small fibre neuropathy raised no safety concerns over four weeks. The ARA 290 group improved more than placebo on a small fibre neuropathy screening score and changed significantly from baseline on the SF-36 pain and physical functioning scales, while pain inventory and fatigue scores improved equally in both groups6. A blinded 28-day trial in sarcoidosis-associated small nerve fibre loss reported better neuropathic symptoms, higher corneal small nerve fibre density, changes in skin temperature sensitivity and a longer six-minute walk7. In a phase 2 study in type 2 diabetes with painful neuropathy, HbA1c and lipid profiles improved over a 56-day observation period, PainDetect scores improved, and corneal nerve fibre density rose in participants whose baseline was more than one standard deviation from normal4.
The largest trial, a phase 2b study, randomised 64 people with sarcoidosis-associated small nerve fibre loss and neuropathic pain to one of three cibinetide arms or placebo for 28 days5. On the primary endpoint, change in corneal nerve fibre area, one of the three active arms differed significantly from placebo (placebo-corrected change 697 µm², 95% CI 159 to 1,236); that arm also showed more regenerating GAP-43-positive fibres in the skin, and changes in corneal fibre area tracked changes in those fibres and in six-minute walk distance5. Pain improved significantly in all groups5.
What is not established
Every trial here ran for about a month, the two that report their size enrolled 22 and 64 people, and the corneal measurements are surrogate markers rather than clinical outcomes, a use the phase 2b authors argued for in their conclusions5. Placebo groups improved on some symptom measures too6,5.The receptor model comes mainly from one group, Brines and Cerami’s, and rests on co-precipitation and knockout experiments rather than a structure of the complex2,3; Brines is also an author of the type 2 diabetes trial4. None of these studies used PrymaLab material. The guide to peptides for inflammation research compares cibinetide with KPV and other anti-inflammatory peptides.
How each lot is tested
Every lot is tested in PrymaLab’s own laboratory in Ashland, Kentucky before release: RP-HPLC for purity, LC-MS for identity, Karl Fischer titration for water, LAL for endotoxin and USP <71> for sterility. The results for the lot now shipping are in the certificate panel on this page, and the certificate number, key and QR code can be checked on the verify page. These are in-house results from PrymaLab Analytical, not an independent test, and the lab is not accredited to ISO 17025. The third-party testing guarantee on this page still applies: if any independent laboratory finds the wrong compound, or less than the stated purity or amount, the order is refunded and the cost of the test is reimbursed.
Frequently asked questions
Is ARA-290 the same as erythropoietin?
No. It is an 11-residue peptide modelled on one surface of erythropoietin's helix B, far smaller than the hormone. In the studies that defined it, neither helix B nor the peptide stimulated red-cell production in cells or animals.
What is in the vial?
10 mg of cibinetide as freeze-dried powder: sequence pGlu-EQLERALNSS-OH, formula C51H84N16O21, theoretical mass 1257.3 Da. The certificate panel on this page shows the results for the lot now shipping.
How should the vial be stored?
Sealed, at −20 °C, desiccated and away from light. Let it reach room temperature before opening so moisture does not condense inside. Once reconstituted, keep the solution at 2 to 8 °C, protected from light, for no longer than your laboratory's established period.
How does the vial differ from the pen and the spray?
All three contain the same peptide. The vial holds 10 mg of dry powder that is dissolved when needed. The pen holds 10 mg already dissolved in 3 mL of bacteriostatic water, and the spray holds 10 mg in solution in a spray bottle; both are kept cold, not frozen.
What have the human trials shown?
Small trials of about a month, mostly in sarcoidosis with small nerve fibre loss, reported gains on neuropathy scores and corneal nerve fibre measures and raised no safety concerns. Results were mixed across endpoints, placebo groups improved on some measures, and no larger outcome trial is among the papers cited here.
Is ARA-290 for human use?
No. PrymaLab sells it only for laboratory research. This vial is not a drug, is not approved for use in people or animals, and must not be given to either.
References
- Brines M, Patel NS, Villa P, et al. Nonerythropoietic, tissue-protective peptides derived from the tertiary structure of erythropoietin. Proc Natl Acad Sci U S A. 2008;105(31):10925-30. DOI · PubMed
- Brines M, Grasso G, Fiordaliso F, et al. Erythropoietin mediates tissue protection through an erythropoietin and common beta-subunit heteroreceptor. Proc Natl Acad Sci U S A. 2004;101(41):14907-12. DOI · PubMed
- Brines M, Cerami A. Erythropoietin-mediated tissue protection: reducing collateral damage from the primary injury response. J Intern Med. 2008;264(5):405-32. DOI · PubMed
- Brines M, Dunne AN, van Velzen M, et al. ARA 290, a nonerythropoietic peptide engineered from erythropoietin, improves metabolic control and neuropathic symptoms in patients with type 2 diabetes. Mol Med. 2015;20(1):658-66. DOI · PubMed
- Culver DA, Dahan A, Bajorunas D, et al. Cibinetide Improves Corneal Nerve Fiber Abundance in Patients With Sarcoidosis-Associated Small Nerve Fiber Loss and Neuropathic Pain. Invest Ophthalmol Vis Sci. 2017;58(6):BIO52-BIO60. DOI · PubMed
- Heij L, Niesters M, Swartjes M, et al. Safety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study. Mol Med. 2012;18(1):1430-6. DOI · PubMed
- Dahan A, Dunne A, Swartjes M, et al. ARA 290 improves symptoms in patients with sarcoidosis-associated small nerve fiber loss and increases corneal nerve fiber density. Mol Med. 2013;19(1):334-45. DOI · PubMed
Research use only
For laboratory research use only. ARA-290 10mg is not a drug, food, cosmetic or dietary supplement, is not approved by the FDA or any comparable authority for human or veterinary use, and must not be given to people or animals. It is sold to qualified researchers and institutions, and the buyer is responsible for lawful handling and disposal.













Reviews
There are no reviews yet.