Cartalax (T-31) bioregulator peptide: cartilage research and safety
Cartalax (T-31) is a Khavinson bioregulator tripeptide (Ala-Glu-Asp, AED) studied for cartilage and connective-tissue regulation, fibroblast senescence markers and renal epithelial aging in cell culture. PrymaLab supplies it as a Cartalax 20mg vial and a Cartalax 20mg autoinjector pen for research use only.
- Sequence: Ala-Glu-Asp (AED); Epitalon (AEDG) and Cardiogen (AEDR) share the same first three residues.
- Class: Khavinson short peptide bioregulator, developed at the St. Petersburg Institute of Bioregulation and Gerontology.
- Studied for: Cartilage and connective-tissue gene expression, fibroblast senescence markers (p16, p21, p53), SIRT-6 and renal epithelial aging.
- Findings in the literature: Lower p16, p21 and p53, higher SIRT-6 in aged cell cultures; human data are sparse.
- Storage: Lyophilised powder kept cold and dark; reconstituted solution refrigerated and used within its stability window.
- Related bioregulator: Sigumir is the natural cartilage peptide complex from the same program; Cartalax is the synthetic version.
- Forms at PrymaLab: Cartalax 20mg Peptide vial and the Preloaded Autoinjector | Cartalax | 3ml Pen | 20mg.
| Property | Cartalax (T-31) | Sigumir | Epitalon |
|---|---|---|---|
| Form | Synthetic tripeptide, Ala-Glu-Asp | Natural peptide complex extracted from cartilage | Synthetic tetrapeptide, Ala-Glu-Asp-Gly |
| Tissue studied | Cartilage, connective tissue, aged fibroblasts | Cartilage and joints | Pineal gland, telomerase in cell culture |
| Composition | Single defined sequence, verifiable by mass spectrometry | Mixture; composition varies by extract | Single defined sequence |
| At PrymaLab | 20mg vial and preloaded pen | Not stocked | 10mg and 50mg vials, 10mg nasal spray, pen |
Related: the KLOW guide for the four-peptide repair blend, the Epitalon guide, the bioregulator peptides category, and the peptide reconstitution calculator.
Also known as: T-31, AED peptide (Ala-Glu-Asp)
Cartalax is the trade name for T-31, the synthetic tripeptide Ala-Glu-Asp developed in Vladimir Khavinson's bioregulator program in St. Petersburg. It is studied as a cartilage and connective-tissue bioregulator, and in aged cell cultures it is reported to lower the senescence markers p16, p21 and p53, raise SIRT-6, reduce apoptosis and shift fibroblasts and renal epithelium toward renewal. This research-use-only reference covers that cell-culture evidence, how Cartalax compares with Sigumir and Epitalon, what the literature does and does not say about dosage, and how to read a certificate of analysis for the Cartalax 20mg vial.
Research-use-only disclaimer: T-31 (Cartalax) is intended strictly for in-vitro and laboratory research use. It is not a drug, supplement, or anti-aging peptide therapy, and it is not intended for human or veterinary use. Every finding below is drawn from cell-culture or animal-derived tissue models and is described in hedged, mechanistic terms. Nothing here is medical advice.

TL;DR
T-31 (Ala-Glu-Asp / Cartalax) is a Khavinson short peptide studied as a chromatin-level bioregulator. In aged fibroblast and renal cell cultures, research links it to lower p16, p21, p53, higher SIRT-6 and Ki-67, lower caspase-3 and MMP-9, and IGF1 gene upregulation (reported 3.5–5.6-fold in stem-cell models). Proposed mechanism: sequence-selective binding to A/T-rich DNA. Research use only.
Identity: AED tripeptide (Cartalax), one of the Khavinson short-peptide bioregulators.
Senescence: reported reductions in p16, p21, and p53 (~1.33-fold p53) with increased SIRT-6 in aged renal cultures.
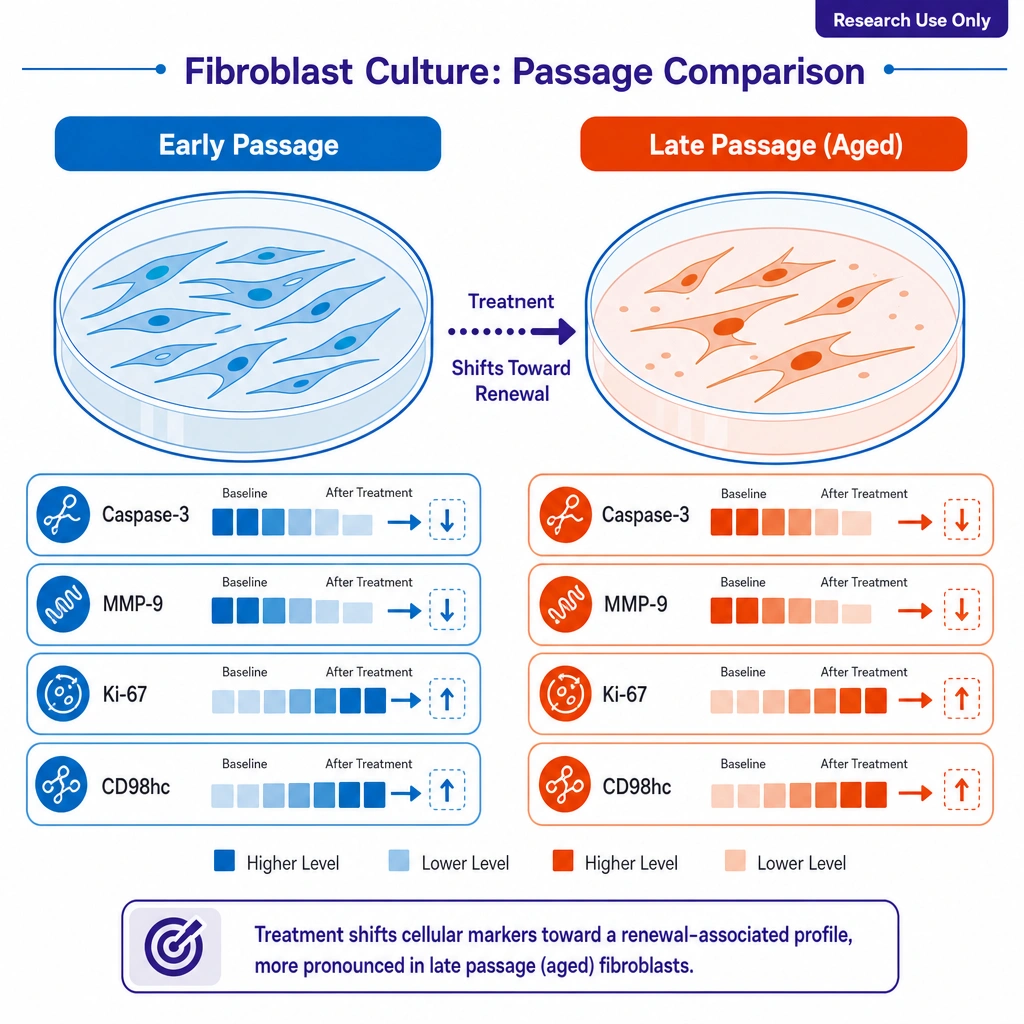
Fibroblasts: higher Ki-67 and CD98hc, lower caspase-3 and MMP-9 — a renewal-oriented profile.
Gene regulation: IGF1 up ~3.5–5.6-fold in MSC aging cultures; modulation of TNKS2, plus FOXO1/TERT/NF-κB examined.
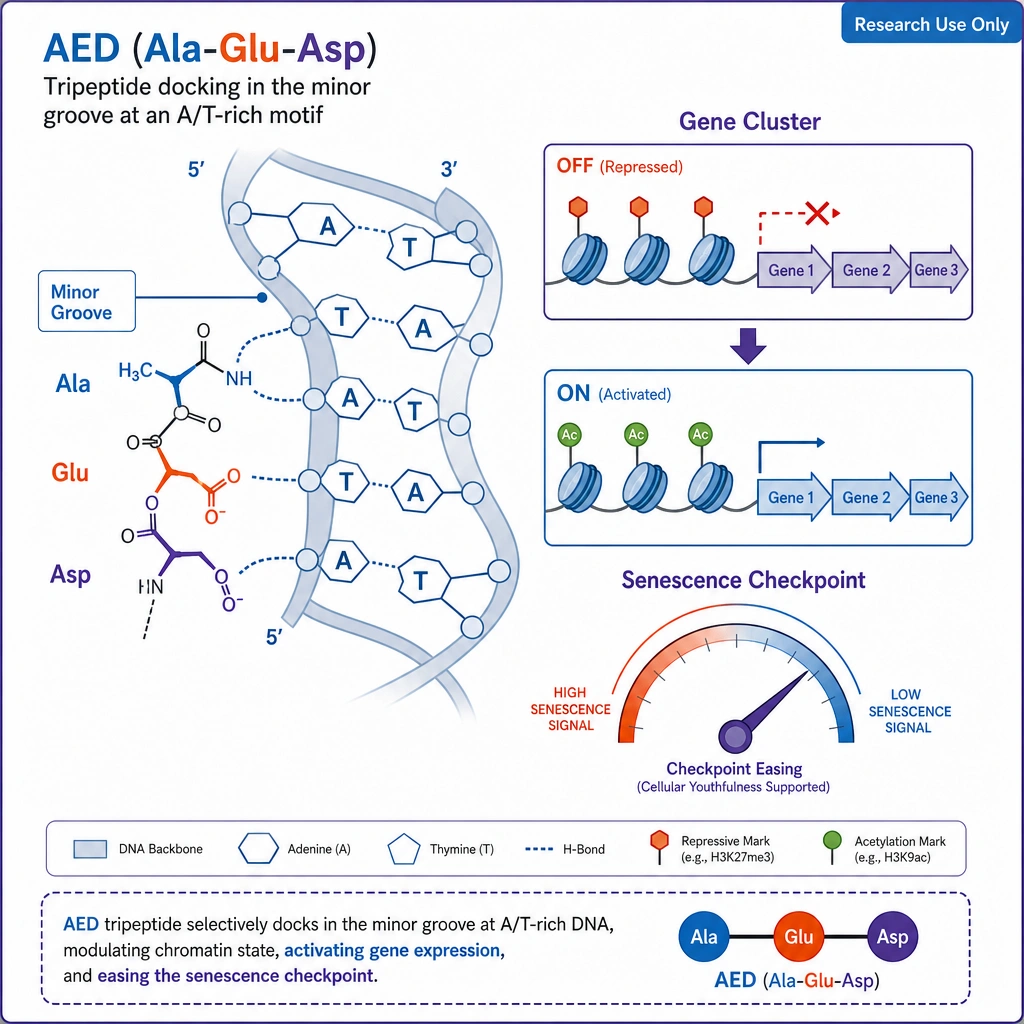
Mechanism: proposed sequence-selective binding to A/T-rich DNA motifs (chromatin-level, not receptor-mediated).
What Is T-31 (Cartalax) and What Family Does It Belong To?
T-31 is a synthetic tripeptide of the sequence Ala-Glu-Asp (AED), commonly called Cartalax. Structurally it belongs to the family of Khavinson short peptides — oligopeptides that some investigators describe as peptide bioregulators on the basis that they may interact with chromatin and modulate transcription of specific gene clusters.
The unifying hypothesis for this family, articulated by Khavinson et al. (2016), is that very short peptides can enter cells and the nucleus and bind DNA at defined motifs. In that work, spatial models of DNA–peptide complexes were built for 19 short peptides; notably, AED-type sequences were associated with binding to specific short DNA motifs (e.g., "acct"-type and A/T-rich sequences), distinguishing its mechanism from mitochondrial peptides like elamipretide (Bendavia), also known as the ss-31 peptide, which is often studied in the context of Barth syndrome. This DNA-binding framing is what lets researchers treat T-31 as a transcription-level tool rather than a classical receptor ligand or a mitochondrial-targeted peptide targeting the inner mitochondrial membrane.
That confusion is common enough to settle outright: T-31 is not SS-31. The two share a number and nothing else. SS-31, better known as elamipretide and also catalogued as MTP-131 and Bendavia, is a synthetic tetrapeptide that concentrates in mitochondria and binds cardiolipin, the signature phospholipid of the inner mitochondrial membrane. Cardiolipin binding stabilizes cristae architecture, keeps cytochrome c associated with the membrane, and preserves electron transport chain supercomplexes, with reported gains in complex IV (cytochrome c oxidase) activity. The knock-on effects run through mitochondrial membrane potential, ATP production, and the oxidative stress that accompanies inefficient electron flow, measured as reactive oxygen species (ROS) leak. SS-31 has also been reported to raise the threshold for opening the mitochondrial permeability transition pore.
That mechanism gives SS-31 a very different research footprint. It is the mitochondria-targeted peptide behind the Barth syndrome program, where a phase 2/3 crossover trial missed both primary endpoints before improving during open-label extension, and it has been examined in primary mitochondrial myopathy, heart failure (where cardiomyocyte energetics are the proposed target), ischemia-reperfusion injury, age-related macular degeneration, and diabetic nephropathy with serum creatinine and chronic kidney disease endpoints. Reported plasma half-life after subcutaneous dosing is roughly four hours, with intravenous infusion protocols run over comparable windows; the gap between that half-life and its longer pharmacodynamic effect is attributed to mitochondrial retention rather than to systemic bioavailability. Downstream literatures cover traumatic brain injury, ischemic brain injury, stroke, exercise tolerance and exercise capacity, muscle function, and oxygen utilization.
None of that describes T-31. T-31 does not target the inner mitochondrial membrane, does not bind cardiolipin, and has no reported effect on the mitochondrial permeability transition pore or on MPTP-dependent cell death. Where a supplier or a search result puts the two together, the listing is wrong. SS-31 work on traumatic brain injury and T-31 work on senescence answer different questions. What the two genuinely share is the longevity literature they get cited in, where mitochondrial dysfunction and oxidative stress sit alongside senescence signaling as parallel hallmarks rather than as one mechanism.
The same catalogue problem affects T-31's other neighbors. Epitalon is the Khavinson tetrapeptide most often paired with it and the closest genuine relative. Semax, CJC-1295, BPC-157, and retatrutide share shelf space and nothing mechanistic: they are respectively a melanocortin fragment, a GHRH analog, a gastric pentadecapeptide, and a triple incretin agonist. GHK-Cu is a copper-binding tripeptide with its own matrix literature. Each is a synthetic peptide marketed into the same longevity conversation, and that shared marketing is the only through-line.
How Does T-31 Affect Fibroblast Aging?
Fibroblasts cultured to different passage numbers are a standard model of cellular aging, and this is where much of the T-31 data begins. Work by Lin'kova et al. (2016) examined AED across early- and late-passage skin fibroblasts.
The reported pattern points toward renewal rather than decline. T-31 was associated with elevated Ki-67 (a proliferation marker) and CD98hc (a glycoprotein involved in amino-acid transport and integrin-linked signaling), alongside reduced executioner caspase-3 in both young and aged cultures — leading the authors to state that the peptide "reduced the level of apoptosis in young and aged cell cultures." In late-passage cells, MMP-9 (a protease tied to excessive matrix breakdown in aged tissue) was also decreased. Taken together, reduced caspase-3 and MMP-9 with elevated Ki-67 and CD98hc were interpreted as a less catabolic, more renewal-oriented fibroblast phenotype.
What Does T-31 Do in Renal Epithelial Aging?
The renal system is the other major model, though some bioregulators are also explored in tissues relevant to heart failure, primary mitochondrial myopathy, or models of neuroprotection, such as Alzheimer’s research. Studies by Khavinson et al. (2014) exposed in-vitro-aged primary kidney cultures to T-31 alongside a calf-kidney polypeptide complex, tracking Ki-67, p53, MMP-14, and IL-8 by immunocytochemistry.
Complementary observations by Chalisova et al. (2015) in kidney tissue cultures from young and old animals were consistent — increased Ki-67 signal and decreased p53 in aged renal cultures. The authors interpret this less as T-31 forcing proliferation and more as it dampening pro-apoptotic signaling, with the magnitude varying by culture system and donor age.
How Does T-31 Influence p16, p21, and SIRT-6?
Beyond p53, T-31 has been linked to canonical senescence markers. Further renal work by Khavinson et al. (2014, Adv Gerontol) reported reductions in the cyclin-dependent kinase inhibitors p16 and p21 — both commonly used to define a senescent state — consistent with a partial release of the senescence checkpoint in aged renal cultures.
In parallel, the same group reported an increase in SIRT-6 transcript and protein. SIRT-6 is a chromatin-associated enzyme implicated in DNA repair, telomeric chromatin maintenance, and metabolic regulation, and its decline is associated with cellular senescence. It is an NAD-dependent deacetylase, so its activity is bounded by cellular NAD availability, and its role in the DNA damage response is the clearest link between the T-31 marker set and genome maintenance. An apparent T-31-linked rise in SIRT-6, set against falling p16/p21 and potentially lower ROS levels, is read as a potential counter-senescent signature. Mechanistically, the authors tie these effects back to the DNA-binding hypothesis — proposing that AED forms energetically favorable complexes with A/T-rich motifs such as d(ATATATATAT)2, modulating local chromatin accessibility rather than acting through a surface receptor.
Does T-31 Regulate Genes and Stem-Cell Differentiation?
Gene-expression studies give the sharpest numbers. Ashapkin et al. (2020) tested AED (and related peptides KED and KE) on human mesenchymal stem-cell (MSC) aging cultures, measuring IGF1, FOXO1, TERT, TNKS2, and NF-κB.
T-31 also intersects with stem-cell differentiation. Work by Linkova et al. (2023) in a chondrogenic model reported that AED modulates TNKS2 (tankyrase 2), a gene involved in telomere maintenance, Wnt signaling, and mitotic regulation. In differentiation assays, AED at an effective concentration near 200 ng/mL increased chondrocyte numbers by roughly 1.4–1.8× in young cultures and 1.6–2.1× in older cultures versus control — suggesting the peptide can bias fate decisions in mesenchymal cells, with the direction and magnitude depending on passage and protocol.
| Marker | Reported direction | Model | Role |
|---|---|---|---|
| p53 | ↓ ~1.33× | Aged renal epithelium | Pro-apoptotic |
| p16 / p21 | ↓ | Aged renal epithelium | Senescence checkpoint |
| SIRT-6 | ↑ | Aged renal epithelium | Counter-senescent |
| Ki-67 | ↑ (~2× proliferation) | Fibroblast / renal | Proliferation |
| Caspase-3 | ↓ | Fibroblasts | Apoptosis |
| MMP-9 | ↓ | Late-passage fibroblasts | Matrix breakdown |
| IGF1 (gene) | ↑ ~3.5–5.6× | MSC aging cultures | Growth/renewal |
| Chondrocyte number | ↑ ~1.4–2.1× | Chondrogenic model | Differentiation |
What About Cellular Stress Resistance?
The renewal-oriented profile ties into stress resistance, potentially aiding cells in managing oxidative stress, ATP synthesis, energy production, and mitochondrial dysfunction, similar to the metabolic regulation studied with mots-c. Because SIRT-6 participates in DNA repair and telomeric chromatin maintenance, and TNKS2 is linked to telomere stability and Wnt-dependent fate decisions, an AED-associated rise in these factors is interpreted as compatible with better-supported genome maintenance, mitochondrial health, mitochondrial respiration, and stable ATP production in aged cultures. Likewise, reduced caspase-3 and MMP-9 suggest a cellular environment less primed for apoptosis—often triggered by the oxidation of the phospholipid cardiolipin and subsequent release of cytochrome c by reactive oxygen species—and matrix catabolism under the strain of replicative aging.
Importantly, these are correlative, model-dependent observations. The proposed chromatin-binding mechanism remains a hypothesis, and the magnitude of every effect varies with the specific aging protocol, passage number, and donor tissue — unlike direct interventions on the electron transport chain—which is why T-31 is best understood as a research probe of age-associated transcriptional programs, not a demonstrated intervention.
Two boundaries are worth stating outright. The first is scope: T-31 has been examined in fibroblast, renal, and chondrogenic cultures. It has not been tested against cognitive function, brain health, neurodegeneration, neuroinflammation, Parkinson's disease, heart disease, type 2 diabetes, metabolic syndrome, or long COVID, all of which appear in searches that land on pages like this one. The second is mechanism: nothing in the T-31 dataset measures mitochondrial biogenesis, mitochondrial activity, or cellular energy production directly, so descriptions of the peptide as mitochondrial optimization are extrapolation from the marker list rather than readings off it. Traumatic brain injury and the other acute-injury models belong to the SS-31 literature. What the longevity field can take from T-31 is a transcriptional hypothesis, which is a narrower thing than it usually gets sold as.
How is research-grade T-31 characterized?
Because AED is a very short peptide, identity confirmation and purity are the meaningful quality questions for reproducible transcriptional assays. Research-grade T-31 is typically verified by reversed-phase HPLC for purity and mass spectrometry for identity, shipped as a lyophilized powder, handled cold, and supplied for laboratory use only. Reconstitution medium is worth recording alongside the result: bacteriostatic water and plain sterile water behave differently across long assays, and benzyl alcohol is not inert in every cell system. Where a protocol challenges cells with an inflammatory stimulus such as LPS, the vehicle needs a control arm of its own. At PrymaLab, every lot is tested in its own laboratory by RP-HPLC for purity and LC-MS for identity, and the certificates can be checked at prymalab.net/testing/verify. No specific lot data are asserted in this general reference.
What the science says about Cartalax and cartilage
Cartalax was designed in the Khavinson program as the cartilage and connective-tissue member of a family of short synthetic peptides, each paired with a natural peptide complex extracted from the same tissue. The design principle is tissue specificity: a short sequence that enters the nucleus, binds DNA at specific sites, and shifts the expression of genes that the source tissue depends on. For Cartalax the proposed targets are the genes chondrocytes and fibroblasts use to build and maintain extracellular matrix, the same collagen and proteoglycan machinery that declines with age.
The direct evidence is the cell-culture work described above: in aged fibroblast and renal epithelial cultures, the AED tripeptide is reported to lower p16, p21 and p53, raise SIRT-6, reduce apoptosis and restore proliferation. What that literature does not contain is a controlled study of Cartalax in a joint, an animal model of osteoarthritis, or a human trial with a cartilage endpoint. The cartilage claim rests on the tissue-specificity principle and on the older Russian bioregulator series, most of it published outside indexed journals. A reader should treat it as a hypothesis with supporting mechanism data, not as a demonstrated effect on cartilage.
Cartalax vs Sigumir
Sigumir is the natural cartilage peptide complex from the same program, an extract of animal cartilage that contains a mixture of short peptides. Cartalax is the synthetic counterpart: a single defined tripeptide with a known sequence, which is why it can be characterised by mass spectrometry and HPLC in a way an extract cannot. The two are studied for the same tissue, but only Cartalax has a fixed composition that a certificate of analysis can confirm. PrymaLab stocks Cartalax as a Cartalax 20mg vial and a preloaded 20mg pen; Sigumir is not stocked.
Peptide bioregulators compared with joint supplements
Glucosamine and chondroitin are building blocks: they supply substrate for glycosaminoglycan synthesis and are taken in gram quantities. A bioregulator peptide is a signal, studied in microgram quantities for what it does to gene expression rather than for the mass it adds. The two are not competing versions of the same idea, and evidence for either in human joints is mixed. In a research setting the distinction decides the endpoint: matrix content and cell proliferation for a bioregulator, substrate incorporation for a supplement.
What the Cartalax studies measured
| Study or model | Subject | Amount reported | Route | Duration |
|---|---|---|---|---|
| Skin fibroblast aging in vitro (Lin'kova et al., Bull Exp Biol Med 2016;161(1):175-178) | Human skin fibroblasts aged in culture | Not stated in the report | In vitro | Across culture passages |
| Kidney tissue culture (Chalisova et al., Bull Exp Biol Med 2015;159(1):124-127) | Organotypic kidney explants from young and old rats | Not stated in the report | In vitro | Days in culture |
| Human trial with a cartilage endpoint | None published for Cartalax alone | Not established | Not established | Not established |
The milligram figures that circulate for Cartalax capsules and injections come from vendor and practitioner material, not from a published trial, and this page does not repeat them as if they were. For a research solution, the concentration is the mass of peptide divided by the volume of diluent: 20 mg in 2 mL gives 10 mg per mL.
Sourcing Cartalax for research
Because Cartalax is a defined tripeptide, a lot-specific certificate of analysis can confirm it: an observed mass matching Ala-Glu-Asp, an HPLC purity figure with the chromatogram attached, and a lot number that matches the vial. The Cartalax 20mg Peptide is supplied lyophilised for research use only, and the same peptide is available as the Preloaded Autoinjector | Cartalax | 3ml Pen | 20mg for protocols that want a fixed concentration without a reconstitution step. Related Khavinson peptides, including Epitalon and Thymogen, are grouped in the bioregulator peptides category.
Frequently Asked Questions
What is Cartalax bioregulator?
Cartalax is a synthetic tripeptide, Ala-Glu-Asp, from the Khavinson bioregulator program in St. Petersburg, where it is the cartilage and connective-tissue member of the short-peptide family. In aged cell cultures it is reported to lower senescence markers such as p16 and p21 and raise SIRT-6. It is supplied for research use only, as a lyophilised 20 mg vial or a preloaded pen.
Is Cartalax the same as T-31?
Yes. T-31 is the code name used in the Khavinson literature for the tripeptide alanine-glutamate-aspartate (AED), and Cartalax is the trade name for the same sequence. Papers on fibroblast aging and renal epithelial senescence use T-31 or AED; supplier listings use Cartalax. The compound, the sequence and the research findings are identical under either name.
What is the difference between Cartalax and Sigumir?
Both come from the same program and target cartilage, but Sigumir is a natural peptide complex extracted from animal cartilage, a mixture whose composition depends on the extract, while Cartalax is a single synthetic tripeptide with a defined sequence. That definition is what lets a certificate of analysis confirm identity and purity for Cartalax by mass spectrometry and HPLC.
What does Cartalax do to cartilage?
The published data are cell-culture findings: in aged fibroblast and renal epithelial cultures, the AED tripeptide is reported to lower p16, p21 and p53, raise SIRT-6, reduce apoptosis and restore proliferation. No controlled study of Cartalax in a joint, an osteoarthritis animal model or a human trial with a cartilage endpoint has been published, so the cartilage effect remains a mechanism-based hypothesis.
How is Cartalax reconstituted for research?
The 20 mg lyophilised vial is reconstituted with bacteriostatic water added slowly down the glass wall, then swirled rather than shaken until the solution is clear. The volume added sets the concentration: 2 mL gives 10 mg per mL. The reconstituted solution is refrigerated and protected from light. The concentration is the mass of peptide divided by the volume of diluent.
What is T-31 (Cartalax)?
T-31 is the tripeptide Ala-Glu-Asp (AED), also called Cartalax, a Khavinson short peptide studied as a chromatin-level bioregulator in aging cell cultures. It is for research use only.
How does T-31 affect senescence markers?
In aged renal cultures it reportedly lowers p16, p21, and p53 (~1.33-fold p53) and raises SIRT-6 — a pattern interpreted as counter-senescent in these models.
Does T-31 regulate gene expression?
Yes. Ashapkin et al. (2020) reported IGF1 gene expression up ~3.5–5.6-fold in MSC aging cultures, with FOXO1, TERT, TNKS2, and NF-κB also examined; AED is proposed to bind A/T-rich DNA motifs.
What does T-31 do in fibroblasts?
Lin'kova et al. (2016) reported higher Ki-67 and CD98hc and lower caspase-3 and MMP-9 — a renewal-oriented, less catabolic fibroblast phenotype.
Does T-31 influence stem-cell differentiation?
In a chondrogenic model, AED at ~200 ng/mL increased chondrocyte numbers ~1.4–1.8× (young) and ~1.6–2.1× (old) versus control and modulated TNKS2.
Is T-31 approved for human use?
No. T-31 (Cartalax) is research-use-only, studied only in cell and tissue models, and is not intended for human or veterinary use. Nothing in the longevity literature changes that.
References
- Lin'kova NS, Drobintseva AO, Orlova OA, et al. Peptide Regulation of Skin Fibroblast Functions during Their Aging In Vitro. Bull Exp Biol Med. 2016;161(1):175–178. PMID:27259496
- Khavinson VKh, Lin'kova NS, Polyakova VO, et al. Peptides regulate the expression of signaling molecules in kidney cell cultures during in vitro aging. Bull Exp Biol Med. 2014;157(2):261–264. PMID:24958378
- Chalisova NI, Lin'kova NS, Nichik TE, et al. Peptide Regulation of Cell Renewal Processes in Kidney Tissue Cultures from Young and Old Animals. Bull Exp Biol Med. 2015;159(1):124–127. PMID:26033601
- Khavinson VKh, Tarnovskaia SI, Lin'kova NS, et al. Tripeptides slow down the aging process in renal cell culture. Adv Gerontol. 2014;27(4):651–656. PMID:25946838
- Linkova N, Khavinson V, Diatlova A, et al. Peptide Regulation of Chondrogenic Stem Cell Differentiation. Int J Mol Sci. 2023;24(9):8415. PMC10179481
- Ashapkin V, Khavinson V, Shilovsky G, Linkova N, Vanyushin B. Gene expression in human mesenchymal stem cell aging cultures: modulation by short peptides. Mol Biol Rep. 2020;47(6):4323–4329. doi:10.1007/s11033-020-05506-3
- Khavinson VK, Lin'kova NS, Tarnovskaya SI. Short Peptides Regulate Gene Expression. Bull Exp Biol Med. 2016;162(2):288–292. PMID:27909961
Final disclaimer: This article is an educational research reference. T-31 (Cartalax) is sold and studied for laboratory research use only, is not approved by any regulatory authority, and is not intended for human or veterinary use. Statements about T-31 have not been evaluated by the FDA. Nothing here should be interpreted as medical or anti-aging advice.
Mechanistic descriptions are hypotheses and observations from in-vitro and animal-derived tissue models; the proposed DNA-binding mechanism is unconfirmed and effects may not generalize. Always verify the legal status of any research compound in your jurisdiction before purchase or use.