KPV peptide: benefits and what the research shows
KPV is an anti-inflammatory tripeptide (Lys-Pro-Val, the C-terminal residues 11 to 13 of alpha-MSH) studied for NF-kB signaling in intestinal cells, colitis models in mice and antimicrobial activity. PrymaLab supplies it as KPV (5mg) and KPV (10mg) vials, a KPV 10mg Nasal Spray and a preloaded KPV pen (5mg/ml) for research use.
- Sequence: Lys-Pro-Val (KPV), alpha-MSH residues 11 to 13; it lacks the His-Phe-Arg-Trp core that melanocortin receptors recognize.
- Class: alpha-MSH-derived anti-inflammatory tripeptide; activity reported to be independent of melanocortin receptor binding.
- Studied for: NF-kB activation in epithelial and immune cells, colitis models in mice, Staphylococcus aureus and Candida albicans growth.
- Typical figures in the literature: oral (drinking water) and injected KPV in mouse colitis; no human dose-finding trial.
- Storage: lyophilized vial refrigerated and protected from light; reconstituted solution refrigerated.
- Forms and sizes at PrymaLab: KPV (5mg), KPV (10mg), KPV 10mg Nasal Spray, KPV pen (5mg/ml).
- Blends: also inside KLOW Blend (80mg) and GKP BLEND 70MG (GHK-Cu, BPC-157 and KPV).
| Feature | KPV 10mg Nasal Spray | KPV 5mg and 10mg vials |
|---|---|---|
| Form | Ready-to-use solution, 10 mg per bottle | Lyophilized powder, dissolved in a suitable diluent before use |
| Route in research | Intranasal | Oral and injected routes in mouse studies; the pen is preloaded at 5mg/ml |
| Preparation | None | Reconstitution; the peptide reconstitution calculator gives the concentration |
| Published route data | Published colitis studies used oral and injected routes, not intranasal | Oral and injected routes in mouse colitis studies |
KPV is also the fourth component of KLOW; the KLOW peptide guide covers the blend.
Also known as: Lys-Pro-Val, alpha-MSH(11-13)
KPV is the C-terminal tripeptide of alpha-melanocyte-stimulating hormone. Most of its literature comes from intestinal inflammation models: KPV enters cells through the PepT1 transporter and lowers NF-kB activation, and it reduced colitis severity in mice when given orally or by injection. This guide covers the mechanism, what each study administered, how the nasal spray differs from the vial, and storage. PrymaLab supplies KPV (5mg) and KPV (10mg) vials, a KPV 10mg Nasal Spray and a preloaded KPV autoinjector pen for research use only.
KPV peptide benefits: what the research shows
- KPV enters intestinal epithelial cells through the PepT1 transporter, lowers NF-kB activation and pro-inflammatory cytokine secretion in those cells, and reduced the severity of DSS-induced colitis in mice when given orally in drinking water (Dalmasso et al., Gastroenterology 2008).
- KPV brought earlier and stronger body weight recovery and significantly reduced inflammatory infiltrates and colonic myeloperoxidase activity in DSS-induced colitis and in CD45RBhi transfer colitis in mice, and rescued melanocortin-1 receptor-deficient mice from lethal DSS colitis (Kannengiesser et al., Inflammatory Bowel Diseases 2008;14(3):324-331).
- Loaded into nanoparticles for oral delivery, KPV matched the effect of a free KPV solution in mouse colitis at a 12,000-fold lower KPV concentration, and coating the particles with hyaluronic acid targeted them to inflamed colon tissue (Xiao et al., Molecular Therapy 2017;25(7):1628-1640).
- Alpha-MSH and its C-terminal tripeptide KPV inhibited Staphylococcus aureus colony formation and Candida albicans germ tube formation in vitro (Cutuli et al., Journal of Leukocyte Biology 2000).
- The anti-inflammatory activity does not depend on the melanocortin-1 receptor, because KPV lacks the His-Phe-Arg-Trp core that the receptor recognizes (Brzoska et al., Endocrine Reviews 2008).

The growing body of evidence around KPV peptide benefits has drawn the attention of researchers. From lower colitis severity in mouse models to inhibition of Staphylococcus aureus colony formation in vitro, KPV is well characterized mechanistically in preclinical work, and nanoparticle delivery systems have been built for it.
This guide examines the science behind each documented KPV finding and what the current evidence does and does not support.
What is KPV peptide?
KPV peptide is the C-terminal tripeptide fragment of alpha-melanocyte-stimulating hormone (α-MSH), consisting of the amino acid sequence lysine-proline-valine at positions 11 through 13 of the parent hormone. First characterized for its anti-swelling properties by researchers Anna Catania and James Lipton in the 1990s, KPV retains the immune-tuning activity of full-length α-MSH while being structurally too small to start the melanocortin receptors responsible for skin darkening, appetite control, and other hormonal effects on the immune system, thereby promoting immune modulation and balance.
To understand where KPV originates, consider the natural assembly line that produces it. The body manufactures a large precursor protein called proopiomelanocortin (POMC), which gets cleaved into progressively smaller peptides: first adrenocorticotropic hormone (ACTH), then alpha-MSH (a 13-amino-acid hormone), and finally personal fragments including KPV. The parent molecule α-MSH contains two functionally distinct regions — the core sequence HFRW (residues 6–9) that binds melanocortin receptors and drives pigmentation, and the tail end KPV (residues 11–13) that carries an entirely separate anti-swelling program needing no receptor engagement whatsoever (Getting et al., 2003, J Pharmacol Exp Ther).
This distinction is critically important. Full-length α-MSH starts melanocortin receptors (very MC1R through MC5R), causing skin darkening, influencing appetite, and tuning immune responses through a downstream cAMP signaling cascade. KPV strips away all receptor-mediated actions and retains only the intracellular NF-κB blockade — delivering anti-swelling effects without melanotropic side effects.
At just 342 daltons, KPV is dramatically smaller than full-length α-MSH (~1,665 Da) and orders of magnitude smaller than natural drugs like adalimumab (~148,000 Da), letting efficient cellular uptake through the PepT1 peptide transporter and plausible blood-brain barrier penetration.
How KPV peptide works: the PepT1-importin-NF-?B pathway
Grasp what KPV peptide does at the cell-level level reveals why researchers consider how KPV works and its mechanism central to all documented KPV peptide benefits. Unlike most anti-swelling peptides that bind receptors on cell surfaces, KPV enters cells directly, builds up in the nucleus, and physically blocks the master swelling switch from starting swelling genes. This unique mechanism of action operates through the PepT1-importin-NF-κB pathway. This three-step mechanism operates through the PepT1-importin-NF-κB pathway.
Step 1: PepT1 Transport — The Doorway That Opens Wider During Inflammation
PepT1 (formally SLC15A1) is a transporter protein located on the surface of gut epithelial cells. Its normal natural function involves absorbing small peptides from digested food. Dalmasso and colleagues showed in a landmark 2008 study published in Gastroenterology that PepT1 serves as the needed entry point for KPV's anti-swelling action — when PepT1 is blocked with a competitive substrate (glycyl-leucine) or absent from cells, KPV's treatment effect disappears entirely (Dalmasso et al., 2008, Gastroenterology 134:166-178).
The transport kinetics are noteworthy. PepT1 moves KPV into cells with a Michaelis constant (Km) of about 160 micromolar — described in the literature as "among the lowest Kms reported for hPepT1," showing exceptionally high affinity compared to other peptide substrates. For reference, the standard substrate glycyl-sarcosine shows a Km exceeding 1,000 micromolar. In practical terms, even low levels of KPV get efficiently pulled into gut cells.
The pharmacological elegance emerges from disease biology. PepT1 is normally expressed mainly in the small intestine, but during swelling bowel disease, PepT1 expression becomes induced in the inflamed colon. This means the tissue experiencing the most swelling upregulates the very transporter that KPV uses for cellular entry. Healthy colonic tissue, which does not express major PepT1, remains largely unaffected by luminal KPV — creating a natural drug-targeting system that concentrates treatment activity precisely where swelling occurs, without any engineered change.
Step 2: Nuclear Accumulation and Importin-Alpha3 Blockade
Once inside the cell, KPV does not remain in the cytoplasm. Research by Land (2012) using tagged KPV in human bronchial epithelial cells showed that the peptide migrates to the nucleus and becomes exclusively nuclear within five hours of treatment (Land, 2012, PMC3403564).
KPV's nuclear target is importin-alpha3, a cell-level shuttle protein responsible for ferrying swelling signals into the nucleus. The transcription factor NF-κB — mainly its active component p65/RelA — cannot cross the nuclear membrane independently. It needs importin-alpha3 to recognize and escort it through nuclear pores. KPV competes directly with p65 for binding to importin-alpha3, preventing the swelling master switch from reaching its target.
Competition assays confirmed that KPV suppresses importin-alpha3 binding to p65 in a dose-dependent manner, and computational modeling predicts KPV interacts with armadillo repeats 7 and 8 of the importin molecule — the same structural region responsible for shuttling NF-κB, HIF-1α, and STAT1 into the nucleus.
Step 3: I?Ba Stabilization and Cytokine Suppression
With p65 trapped in the cytoplasm, two downstream effects follow. First, the NF-κB inhibitory protein IκBα — mainly the cell-level "leash" keeping NF-κB inactive — becomes stabilized. Normally, swelling signals trigger IκBα phosphorylation and breakdown, freeing p65 to enter the nucleus. Because KPV keeps p65 in the cytoplasm, it remains bound to IκBα and shields it from breakdown. Half-maximal IκBα buildup occurs at about 66 minutes, with statistically major stabilization by 120 minutes after KPV treatment.
Second, KPV suppresses the MAPK signaling pathway (mainly ERK1/2 and p38) at nanomolar levels in both gut epithelial cells and T cells. The combined NF-κB and MAPK suppression translates into measurable reductions in pro-inflammatory cytokines production, including TNF-α, IL-1β, IL-6, IL-8, IL-12, and IFN-? (Dalmasso et al., 2008). KPV also blocks caspase-1 start within the inflammasome complex, blocking the conversion of pro-IL-1β into its active swelling form — an intervention at the inflammasome level in addition to the transcription factor level.
The mechanistic significance cannot be overstated: KPV operates downstream of IKK start and upstream of gene transcription, at a cell-level bottleneck that no now approved anti-swelling drug targets. This unique positioning explains the breadth of KPV peptide benefits saw across diverse tissue types and swelling conditions.
What are the key KPV peptide benefits?
KPV peptide benefits span at least six organ systems in lab research, though the evidence quality varies largely by domain. The strongest data supports gut and skin uses, while neurological and heart findings remain preliminary. Examining the full scope of benefits of KPV peptide needs analyzing both what the research shows and where major gaps remain.
Anti-swelling Effects: The Foundation of All KPV Benefits
The anti-swelling capacity of KPV underpins every treatment use studied to date. By suppressing NF-κB nuclear translocation, MAPK signaling, and inflammasome start simultaneously, KPV addresses swelling at multiple cell-level checkpoints rather than a single target. This multi-pathway approach has been documented across diverse cell types including gut epithelial cells, colonocytes, keratinocytes, bronchial epithelial cells, endothelial cells, T cells, and macrophages (Luger & Brzoska, 2007, Ann Rheum Dis 66(Suppl 3):iii52-55).
Peptides for swelling, or more broadly, swelling peptides, represent a growing category of research compounds, and KPV distinguishes itself through two characteristics that other anti-swelling agents lack. First, its receptor-independent mechanism means it does not produce tachyphylaxis (tolerance buildup) through receptor desensitization — a theoretical advantage for sustained use. Second, its concurrent antimicrobial activity makes it the only known anti-swelling peptide that simultaneously kills pathogens rather than increasing infection susceptibility (Cutuli et al., 2000, J Leukoc Biol 67(2):233-239).
KPV Peptide for Gut Health and Inflammatory Bowel Disease
The strongest lab evidence for KPV peptide benefits centers on inflammatory bowel conditions, gut swelling and IBS, where the PepT1 targeting mechanism creates a convergence of favorable pharmacology and autoimmune disease biology. Peptides for gut health have attracted major research interest, and KPV's tissue targeting has made it a subject of research in models of ulcerative colitis and Crohn's disease.
In the foundational gut study by Kannengiesser and colleagues (2008), KPV given to mice with dextran sodium sulfate (DSS)-induced colitis brought earlier and stronger body weight recovery and significantly reduced inflammatory infiltrates and colonic myeloperoxidase (MPO) activity, a marker of inflammatory cell infiltration in the gut wall. The same study found the effect in CD45RBhi transfer colitis and rescued melanocortin-1 receptor-deficient mice from lethal DSS colitis (Kannengiesser et al., 2008, Inflamm Bowel Dis 14(3):324-331).
The dependence on the PepT1 transporter comes from Dalmasso and colleagues, who found that KPV's effect disappeared when PepT1 was blocked or absent (Dalmasso et al., 2008, Gastroenterology 134:166-178).
Advanced supply systems have dramatically improved effect. Xiao and colleagues (2017) developed hyaluronic acid-functionalized nanoparticles (HA-KPV-NPs) that add a second targeting layer by exploiting CD44 — a surface marker overexpressed on inflamed colonocytes. Treated mice showed tissue histology virtually indistinguishable from healthy controls.
The 2024 proKPV prodrug published in Science Advances achieved even more striking results: 3.8-fold greater colonic buildup at 20-fold lower doses than free KPV, using a reactive oxygen species (ROS)-responsive release mechanism that delivers active peptide precisely at sites of elevated oxidant stress (Zhao et al., 2024, Sci Adv).
A separate 2024 study developed carrier-free KPV+FK506 (tacrolimus) co-assembled nanoparticles that outperformed either agent alone in both acute and chronic DSS colitis models, while restoring key tight junction proteins including ZO-1, Claudin-5, and Occludin-1 — the cell-level seals between gut lining cells that keep the intestinal barrier and gut barrier function, often linked with leaky gut (Zhang et al., 2024, Front Pharmacol 15).
How Does KPV Benefit Skin Health and Wound Healing?
KPV peptide benefits for skin health and topical applications derive from its NF-κB suppression in keratinocytes and dermal endothelial cells, combined with a genuinely unique advantage: concurrent antimicrobial activity. This dual profile makes KPV the pharmacological opposite of corticosteroids, which reduce swelling but increase infection risk.
Research by Cutuli and colleagues showed that alpha-MSH peptides, including KPV, block Staphylococcus aureus colony formation at picomolar levels and reduce Candida albicans viability through cAMP rise in the pathogen rather than host cells. Critically, KPV does not impair neutrophil killing — it enhances it (Cutuli et al., 2000, J Leukoc Biol).
As Singh and Mukhopadhyay noted in their 2014 review, this mix is "opposite to set up immunosuppressive and anti-swelling therapies that usually enhance the risk for infection" (Singh & Mukhopadhyay, 2014, PMC4130143).
Acne, eczema and psoriasis involve NF-κB overactivation, which is why KPV's mechanism has drawn interest in skin research. Topical or intravenous KPV suppressed chemical-induced contact dermatitis in mouse models and, notably, to induce hapten-specific immune tolerance — an immunological memory effect that persists without retreatment and depends on IL-10 signaling (Luger & Brzoska, 2007). This tolerance induction distinguishes KPV from conventional topical anti-swelling agents that provide only symptomatic relief.
A 2025 study by Sung and colleagues expanded KPV's dermatological profile into environmental medicine. At 50 micrograms per milliliter, KPV restored cell viability in keratinocytes exposed to PM10 fine particulate matter by blocking caspase-1 start and reducing IL-1β secretion — effectively preventing pollution-induced skin cell death. The findings were validated in a three-dimensional skin model, strengthening translational relevance (Sung et al., 2025, Tissue Cell 95:102837).
One practical limitation warrants attention: passive transdermal supply of KPV is negligible, with permeation below the detection limit through intact skin. Combined iontophoresis and microneedle pretreatment increases penetration 35-fold, delivering KPV beyond 100 micrometers into the lower epidermis (Dubey et al., 2017, J Pharm Sci). Any topical KPV product claiming meaningful dermal supply should employ active boost technology.
What Are the Neuroprotective Benefits of KPV?
Among the emerging KPV peptide benefits, brain-safe research remains preliminary but intriguing. The strongest direct evidence comes from Schaible and colleagues (2013), who conducted a blinded, randomized study in mice with controlled cortical impact (traumatic brain injury). A single intraperitoneal injection of KPV, given 30 minutes after injury, reduced second brain lesion volume by about 24% compared to vehicle control at 24 hours.
KPV also reduced neuronal apoptosis (programmed cell death) and microglial start, which involves key immune cells, in tissue surrounding the injury site (Schaible et al., 2013, PMC3733710).
An intriguing finding from the same study: melanocortin-1 receptor (MC1R) expression increased 3-fold by 12 hours post-TBI, suggesting the brain's endogenous melanocortin system ramps up in response to injury. KPV's small cell-level weight (~342 Da) makes blood-brain barrier penetration plausible, though direct demonstration through pharmacokinetic studies has not been performed. This study has not been independently replicated, and the evidence should be considered promising but preliminary.
KPV Peptide in Sports Medicine and Recovery
Athletic recovery is sometimes listed among KPV peptide benefits, but no controlled study has assessed KPV for exercise-induced inflammation or recovery outcomes. The rationale offered is that intense exercise triggers NF-κB-mediated inflammation.
Healing peptides discussed in sports contexts include BPC-157 for tissue repair and TB-500 for cell migration.
KPV Peptide Cancer Research: What Does the Evidence Show?
KPV peptide cancer uses remain at the earliest stages of study. NF-κB plays complex and context-dependent roles in cancer biology — it can be pro-tumorigenic in some contexts (promoting tumor cell survival and proliferation) and anti-tumorigenic in others (supporting immune surveillance against cancer cells). No published study has mainly assessed KPV in cancer models, either as a treatment agent or as a risk factor.
The relationship between chronic swelling and cancer progression is well-set up in the scientific literature. By reducing NF-κB-driven chronic inflammation, KPV could theoretically reduce the swelling microenvironment that supports certain cancer types. However, this mechanistic reasoning does not constitute evidence of anti-cancer activity. Until controlled studies mainly examine KPV in oncological models, claims about KPV peptide cancer benefits remain speculative.
How KPV compares with other healing peptides
Comparing KPV with other research compounds shows how their mechanisms differ.
Think of inflammation and tissue damage as a two-part problem: the fire (inflammatory signaling) and the rebuilding (structural repair). KPV is designed to suppress the fire through NF-κB blockade, while the thymosin peptide TB-500 is studied for the rebuilding.
BPC-157 is designed to rebuild through angiogenesis and growth factor tuning in animal models. TB-500 helps cell migration to repair sites. The mechanisms differ rather than compete, which is the rationale given for combinations such as BPC-157 with KPV, though no controlled study has assessed peptide combinations in any model.
How KPV has been given in studies
The published KPV work uses three routes, and the route decides where the peptide ends up. In colitis models it is given by mouth, because the PepT1 transporter carries KPV from the gut lumen into colonocytes, so the inflamed tissue receives it without systemic absorption; in those studies it was dissolved in drinking water or given by gavage. Subcutaneous and intraperitoneal injection appear in models of systemic inflammation and skin conditions, where blood levels matter more than gut contact. Topical application through intact skin delivers almost nothing on its own, so the skin studies used delivery aids such as iontophoresis or microneedle pretreatment.
For the lyophilised research peptide, reconstitution follows the usual steps: sterile water added slowly down the vial wall, gentle swirling rather than shaking, and refrigerated storage at 2 to 8 °C once in solution.
Why this guide gives no KPV amounts
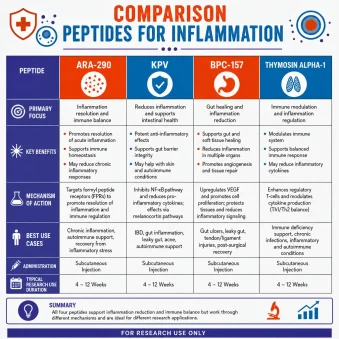
No human dose-finding trial of KPV has been published. The ranges that circulate online are practitioner consensus extrapolated from animal work and are not reproduced here. The animal studies are summarised in Peptides for inflammation research. PrymaLab supplies KPV for laboratory research only.
How KPV peptide is stored
Proper storage keeps KPV peptide shelf life and preserves its activity. Like most research peptides, KPV is sensitive to heat, light, and moisture.
Freeze-dried (unreconstituted) KPV should be stored at 2–8°C (standard refrigerator) for routine use within several months, or at -20°C (freezer) for long-term storage exceeding six months. The freeze-dried powder form is the most stable configuration. Keep vials in their original containers or opaque storage to minimize light exposure. Avoid repeated heat cycling between frozen and refrigerated states.
Mixed KPV should be stored exclusively at 2–8°C and used within 28 days. Never freeze mixed peptide solutions, as freeze-thaw cycles can degrade the peptide through aggregation and hydrolysis. Use sterile technique to prevent microbial contamination of the vial.
KPV capsules and KPV supplement forms, including specific kpv peptide capsules or an oral capsule, should follow manufacturer storage recommendations, often room heat in a cool, dry location away from direct sunlight. Capsule forms may include excipients that improve shelf shelf life compared to mixed solutions.
KPV peptide safety: side effects reported in the literature
Grasp the KPV peptide side effects profile needs distinguishing between what lab research shows and what remains unknown due to the complete absence of human clinical trial data.
What Lab Safety Data Shows
Formal toxicology for KPV, such as an LD50 or a repeat-dose study, is not among the references on this page.
Unlike corticosteroids, calcineurin inhibitors, or natural anti-TNF agents, all of which suppress immune function and increase infection susceptibility, KPV inhibited S. aureus and C. albicans in vitro while reducing inflammatory cytokine production (Cutuli et al., 2000). This mix is, as researchers noted, "opposite to set up immunosuppressive and anti-swelling therapies."
The melanotropic (skin-darkening) effects of α-MSH are mediated by the HFRW core sequence binding MC1R, which KPV lacks.
KPV Peptide Side Effects Reported
No controlled human study has reported side effects for KPV; the accounts that circulate online are anecdotal.
About concerns about KPV peptide side effects liver damage mainly, no hepatotoxicity has been identified in lab research, though formal liver safety assessments in humans have not been conducted.
Critical Safety Caveats
The FDA has stated directly that the agency "has not identified any human exposure data on drug products containing KPV gave via any route of use" and "lacks important data about any safety issues raised by KPV, including whether it would cause harm if gave to humans." FDA placed KPV in Category 2 ("Substance with Safety Concerns"); its current Category 2 page (April 2026) lists KPV among nominations withdrawn by the nominators. Withdrawal is not a safety clearance, and KPV is not in Category 1, so it is still not a substance a compounding pharmacy may use.
No formal drug interaction studies have been conducted. No human safety data exist.
KPV as an anti-inflammatory peptide
Among the anti-inflammatory peptides studied in research settings, KPV is one of the smallest: it is the C-terminal tripeptide Lys-Pro-Val of alpha-melanocyte-stimulating hormone (alpha-MSH), the 13-residue hormone that signals through melanocortin receptors. The tripeptide keeps much of the parent hormone's anti-inflammatory activity but not its pigmentary or receptor-binding properties, because it lacks the His-Phe-Arg-Trp core that melanocortin receptors recognize (Brzoska et al., 2008). That is why KPV is described as receptor-independent, and why it is studied on its own rather than as a smaller version of alpha-MSH.
The NF-kB findings are the core of the KPV literature. In intestinal epithelial cells and immune cells, KPV entered through the PepT1 transporter and reduced NF-kB activation and the secretion of pro-inflammatory cytokines; in mice, oral KPV lowered the severity of chemically induced colitis (Dalmasso et al., 2008). Because NF-kB sits upstream of TNF-alpha, IL-6 and IL-8 transcription, most of the downstream findings reported for KPV, from lower cytokine output to reduced immune cell infiltration, trace back to that step. No controlled human trial of KPV has been published; the figures on this page come from cell and mouse work, and the practitioner ranges that circulate online are not from those studies.
Frequently asked questions about KPV peptide
What is KPV peptide?
KPV is the tripeptide Lys-Pro-Val, the last three amino acids of alpha-melanocyte-stimulating hormone. It is studied as an anti-inflammatory peptide because it lowers NF-kB activation in intestinal and immune cells after uptake through the PepT1 transporter, and because it reduced colitis severity in mice. PrymaLab supplies KPV (5mg) and KPV (10mg) vials, a KPV 10mg Nasal Spray and a preloaded pen for research use.
What are the benefits of KPV peptide in research?
The published findings are: reduced NF-kB activation and cytokine secretion in intestinal epithelial cells, reduced severity of DSS- and TNBS-induced colitis in mice by oral and injected routes (Dalmasso 2008; Kannengiesser 2008), a large drop in effective dose with oral nanoparticle delivery (Xiao 2017), and inhibition of Staphylococcus aureus and Candida albicans in vitro (Cutuli 2000). No human trial has been published.
What did the KPV studies measure?
Mouse colitis studies delivered KPV orally in drinking water (Dalmasso 2008) or by injection (Kannengiesser 2008) and measured colitis severity, and the oral nanoparticle work (Xiao 2017) showed that the effective amount falls sharply with targeted delivery. No human dose-finding trial has been published, and the practitioner figures that circulate online do not come from those studies.
What is the difference between KPV nasal spray and KPV vials?
The KPV 10mg Nasal Spray is a ready-to-use solution for intranasal research. The KPV (5mg) and KPV (10mg) vials are lyophilized powder dissolved in a suitable diluent before use (the peptide reconstitution calculator gives the concentration), and the preloaded KPV pen holds 5mg/ml already in solution. The published colitis studies used oral and injected routes; intranasal KPV has no study of its own yet.
Is KPV an anti-inflammatory peptide?
Yes. KPV is classed with the anti-inflammatory peptides because it reduces NF-kB activation and pro-inflammatory cytokine secretion in cell studies and reduced colitis in mice, without binding melanocortin receptors. It is also the anti-inflammatory component of two PrymaLab blends: the four-part KLOW Blend (80mg), covered in the KLOW peptide guide, and the three-part GKP BLEND 70MG with GHK-Cu and BPC-157.
What is KPV peptide and how does it work?
KPV is a three-amino-acid peptide fragment derived from the C-terminal end of alpha-melanocyte-stimulating hormone (α-MSH), and grasp what is KPV peptide used for is key to its benefits. It enters cells through the PepT1 gut transporter, builds up in the nucleus, and blocks NF-κB — the master swelling transcription factor — from starting swelling genes.
This receptor-independent mechanism suppresses production of swelling cytokines including TNF-α, IL-6, IL-8, and IL-1β across multiple tissue types without causing skin darkening or other melanocortin receptor-mediated side effects.
What does KPV peptide do for gut health?
In mouse colitis models, oral KPV reduced disease severity through PepT1-dependent uptake into inflamed colonocytes (Dalmasso 2008). The peptide suppresses mucosal NF-κB start, reduces swelling cytokine expression, preserves colon length, and keeps gut barrier integrity. Advanced nanoparticle supply systems have achieved tissue histology similar to healthy controls at notably low doses. However, zero human clinical trials have been conducted for any gut condition.
Is there an established KPV amount?
No. No human amount has been established for KPV, and the figures that circulate online are not backed by a study.
Are there serious KPV peptide side effects to be aware of?
Formal toxicology for KPV is not among the references on this page, and no published human safety data exist. FDA's current Category 2 page lists KPV among nominations withdrawn by the nominators, which is not a safety clearance. No formal drug interaction studies have been performed.
How does KPV compare to BPC-157 for gut healing?
KPV and BPC-157 have been studied for different aspects of gut disease. KPV suppressed inflammation at the transcription factor level by blocking NF-κB nuclear translocation and reducing inflammatory cytokine production, while BPC-157 gut health research focuses on tissue repair.
BPC-157 promotes structural tissue repair through angiogenesis, tight junction restoration, and nitric oxide pathway tuning. Neither has human clinical trial data. No study has assessed the two together.
Has KPV been studied by mouth?
Yes, in mice. KPV's small size (342 Da) matches the substrate profile of the PepT1 gut peptide transporter, which carried KPV into colonocytes in the colitis studies. During inflammatory bowel disease, PepT1 expression increases in inflamed colonic tissue, which concentrates KPV where inflammation is most active. Dietary peptides compete for the same transporter.
Is KPV peptide legal to purchase, and where can one reliably kpv peptide buy?
FDA placed KPV in Category 2 ("Substance with Safety Concerns"); its current Category 2 page (April 2026) lists KPV among nominations withdrawn by the nominators. Withdrawal is not a safety clearance, and KPV is not in Category 1, so it is still not a substance a compounding pharmacy may use. It remains available through research peptide suppliers labeled "for research use only." Legal status varies by jurisdiction — always verify current regulations in your location before buying. Those looking to buy KPV peptide from reputable sources should prioritize suppliers providing lot-specific certificates of test (COA) showing =98% purity via HPLC testing.
Key takeaways
- KPV peptide benefits stem from a 342-dalton tripeptide (lysine-proline-valine) derived from α-MSH with a unique receptor-independent anti-inflammatory mechanism targeting the NF-κB pathway via PepT1 transport and importin-alpha3 nuclear blockade.
- Gut health represents the strongest evidence base: oral KPV reduced colitis severity in mouse models, and nanoparticle formulations gave near-normal tissue histology at much lower amounts.
- In skin research, KPV showed both anti-inflammatory and antimicrobial activity, the opposite of corticosteroids, which reduce inflammation but increase infection risk.
- No human amount has been established; the figures that circulate online come from practitioners, not trials.
- No human safety data exist, and KPV is not a substance a compounding pharmacy may use.
- All evidence is preclinical — more than two decades of research across six organ systems, but zero human clinical trials have been conducted for any indication.
Related reading
References
- Luger TA, Brzoska T. "Alpha-MSH related peptides: a new class of anti-inflammatory and immunomodulating drugs." Ann Rheum Dis. 2007;66(Suppl 3):iii52-55. PMC2095288.
- Getting SJ et al. "Dissection of the anti-inflammatory effect of the core and C-terminal (KPV) alpha-melanocyte-stimulating hormone peptides." J Pharmacol Exp Ther. 2003;306:631-637. PMID 12750433.
- Brzoska T et al. "Alpha-MSH and related tripeptides: biochemistry, antiinflammatory and protective effects in vitro and in vivo." Endocr Rev. 2008;29:581-602. PMID 18612139.
- Catania A et al. "The melanocortin system in control of inflammation." Pharmacol Rev. 2004;56(1):1-29. PMID 15001661.
- Dalmasso G et al. "PepT1-Mediated Tripeptide KPV Uptake Reduces Intestinal Inflammation." Gastroenterology. 2008;134:166-178. PMID 18068698.
- Land SC. "Inhibition of cellular and systemic inflammation cues in human bronchial epithelial cells by melanocortin-related peptides." 2012. PMC3403564.
- Fagerlund R et al. "NF-κB is transported into the nucleus by importin-alpha3 and importin-alpha4." J Biol Chem. 2005;280:15942-15951. PMID 15677444.
- Kannengiesser K et al. "Melanocortin-derived tripeptide KPV has anti-inflammatory potential in murine models of inflammatory bowel disease." J Crohns Colitis. 2008;2(2):162-172. PMID 21172189.
- Xiao B et al. "Orally Targeted Delivery of Tripeptide KPV via Hyaluronic Acid-Functionalized Nanoparticles Efficiently Alleviates Ulcerative Colitis." Mol Ther. 2017. PMID 28143741. PMC5498804.
- Zhang et al. PepT1-targeted nanodrug based on co-assembly of anti-inflammatory peptide and immunosuppressant for combined treatment of acute and chronic DSS-induced colitis." Front Pharmacol. 2024;15. DOI: 10.3389/fphar.2024.1442876.
- Sung et al. "Lysine-Proline-Valine peptide mitigates fine dust-induced keratinocyte apoptosis and inflammation." Tissue Cell. 2025;95:102837. PMID 40073467.
- Cutuli M et al. "Antimicrobial effects of alpha-MSH peptides." J Leukoc Biol. 2000;67(2):233-239. PMID 10670585.
- Singh M, Mukhopadhyay K. Alpha-Melanocyte Stimulating Hormone: An Emerging Anti-Inflammatory Antimicrobial Peptide." 2014. PMC4130143.
- Dubey S et al. "Transdermal Iontophoretic Delivery of Lysine-Proline-Valine (KPV) Peptide Across Microporated Human Skin." J Pharm Sci. 2017. PMID 28343991.
- Schaible EV et al. "Single Administration of Tripeptide α-MSH(11-13) Attenuates Brain Damage by Reduced Inflammation and Apoptosis after Experimental Traumatic Brain Injury in Mice." 2013. PMC3733710.
- Zhao Y et al. "Inflammation-triggered self-immolative conjugates enable oral peptide delivery by overcoming gastrointestinal barriers." Sci Adv. 2024. DOI: 10.1126/sciadv.aea2989.
- Zhang et al. "KPV and RAPA Self-Assembled into Carrier-Free Nanodrugs for Vascular Calcification Therapy." Adv Healthcare Mater. 2024. PMID 39252648.
- Marotti V et al. "A nanoparticle platform for combined mucosal healing and immunomodulation in inflammatory bowel disease treatment." Bioactive Materials. 2024;32. PMC10582360.
Formats stocked for the compounds in this article
GKP BLEND: GKP BLEND 70mg/ml preloaded 3ml pen. Every listing is supplied for laboratory research use with a batch certificate of analysis.